

Why Long-Term Pancreas Injury Effects Need Ongoing Attention
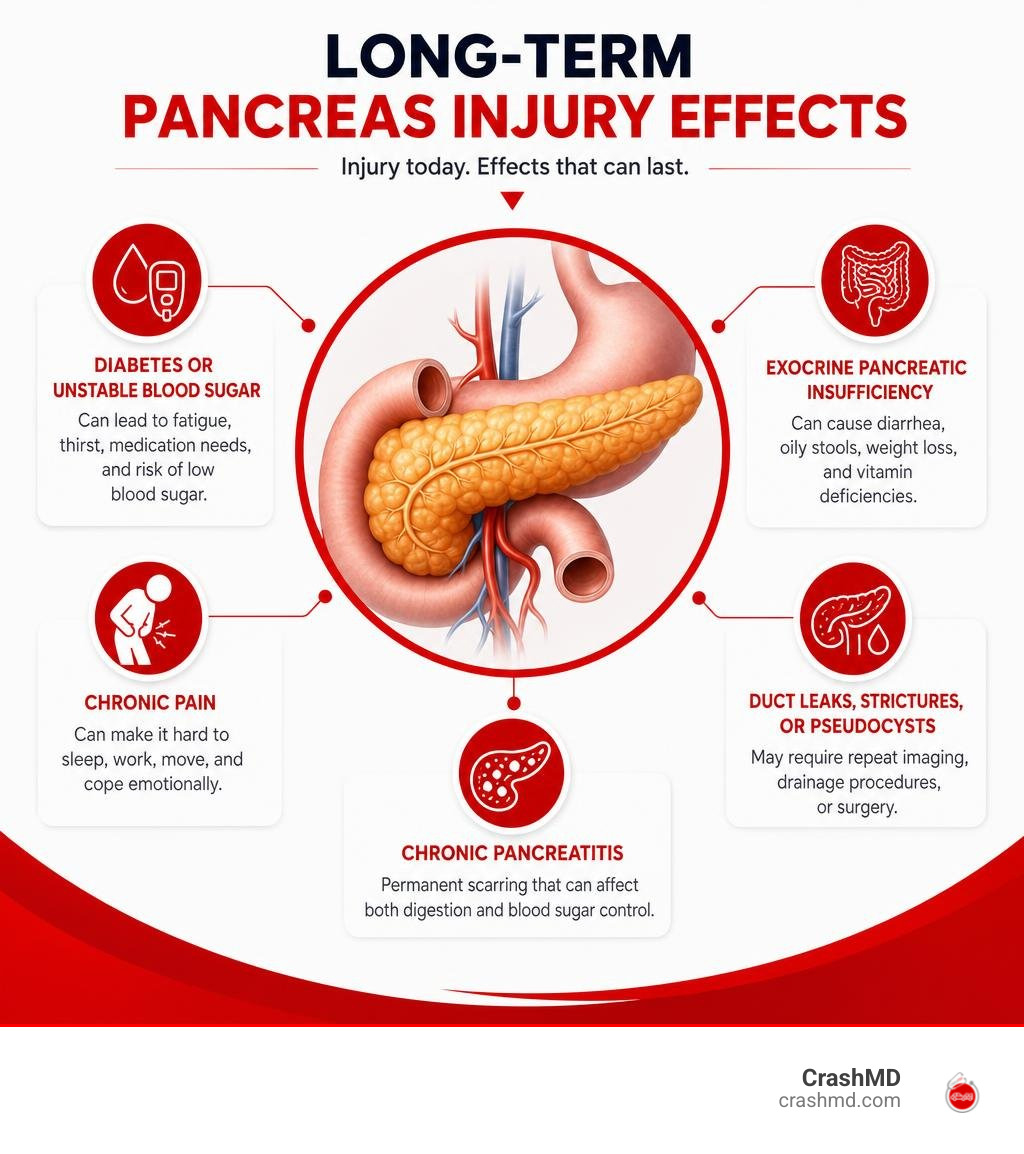
Long-term pancreas injury effects can include ongoing abdominal pain, digestive problems, poor nutrient absorption, diabetes, and delayed complications such as fluid collections or narrowing of the pancreatic duct.
| Possible long-term effect | What it can mean day to day |
|---|---|
| Diabetes or unstable blood sugar | Fatigue, thirst, medication needs, and risk of low blood sugar |
| Exocrine pancreatic insufficiency | Diarrhea, oily stools, weight loss, and vitamin deficiencies |
| Chronic pain | Trouble sleeping, working, moving, and coping emotionally |
| Duct leaks, strictures, or pseudocysts | Repeat imaging, drainage procedures, or surgery may be needed |
| Chronic pancreatitis | Permanent scarring that can affect both digestion and blood sugar control |
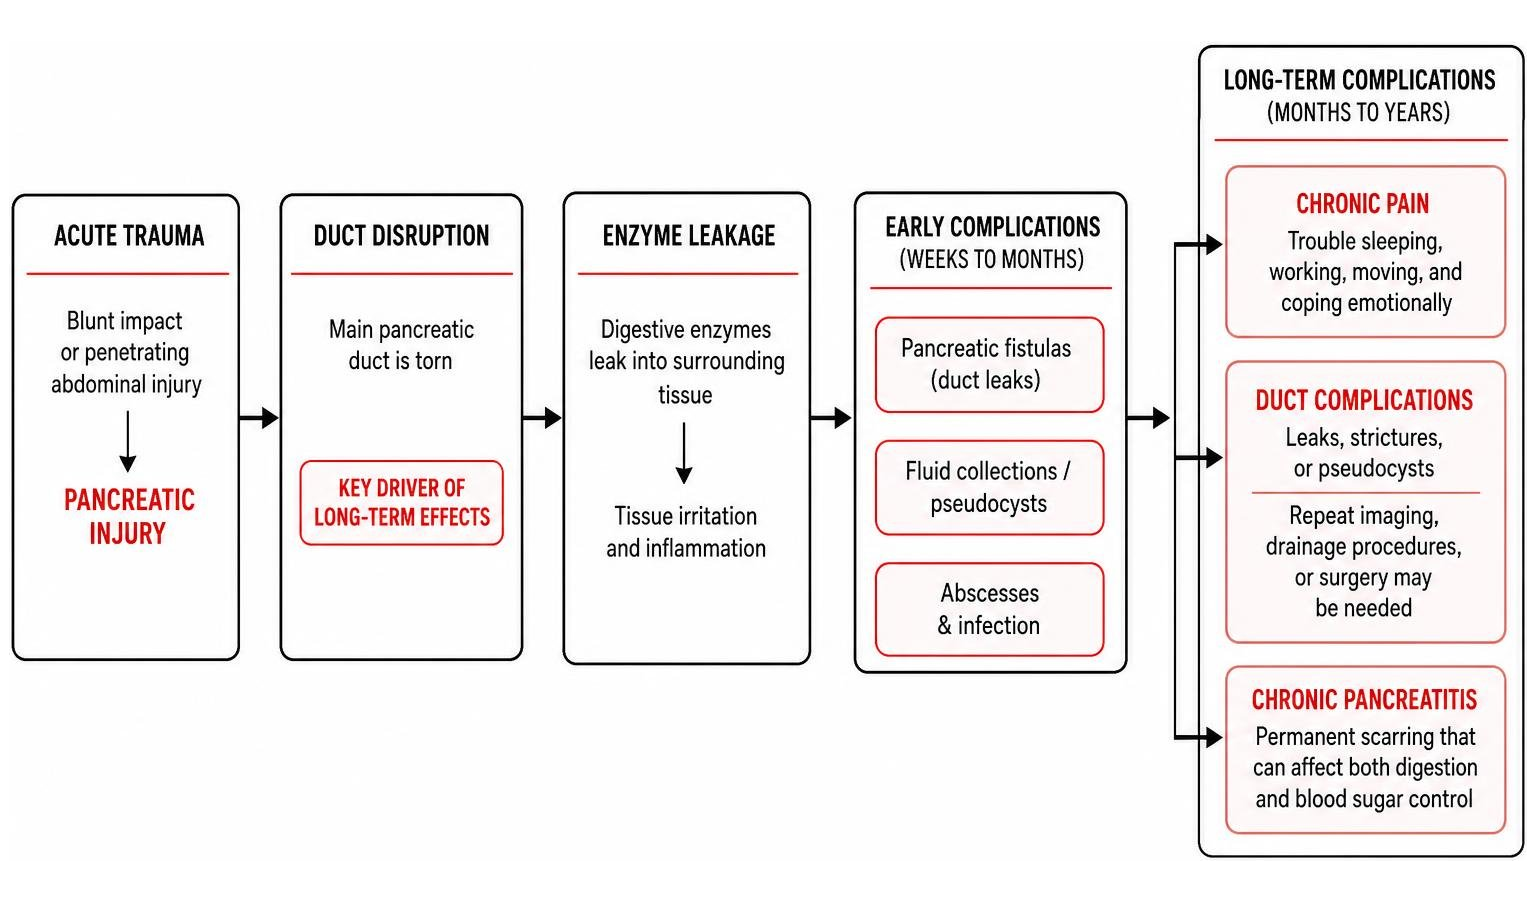
A pancreas injury after a car crash, hard blow to the abdomen, or penetrating wound may not end when the first hospital stay ends. The pancreas sits deep behind the stomach, so damage can be missed early. When its main duct is injured, digestive enzymes can leak into nearby tissue and trigger problems weeks, months, or sometimes years later.
Risk is not the same for everyone. More severe injuries, especially those involving duct disruption, tissue loss, or other abdominal organs, carry a greater chance of lasting complications. Even so, people with less severe injuries should not ignore new pain, unexplained weight loss, greasy stools, or changes in blood sugar after recovery.
I’m Dr. Adam Savage, and this guide explains what to watch for after pancreatic trauma and why long-term follow-up matters.
Basic long-term pancreas injury effects glossary:
Understanding the Primary Long-Term Pancreas Injury Effects
Pancreatic trauma is relatively rare, accounting for 0.2% to 1.1% of all abdominal trauma presentations. However, overall mortality remains high—ranging between 9% and 34%. Because the pancreas rests tucked away against the spine in the retroperitoneum, diagnosing early damage is notoriously difficult. Initial CT scans fail to identify pancreatic tears or duct disruptions in 20% to 40% of patients scanned within 12 hours of trauma.
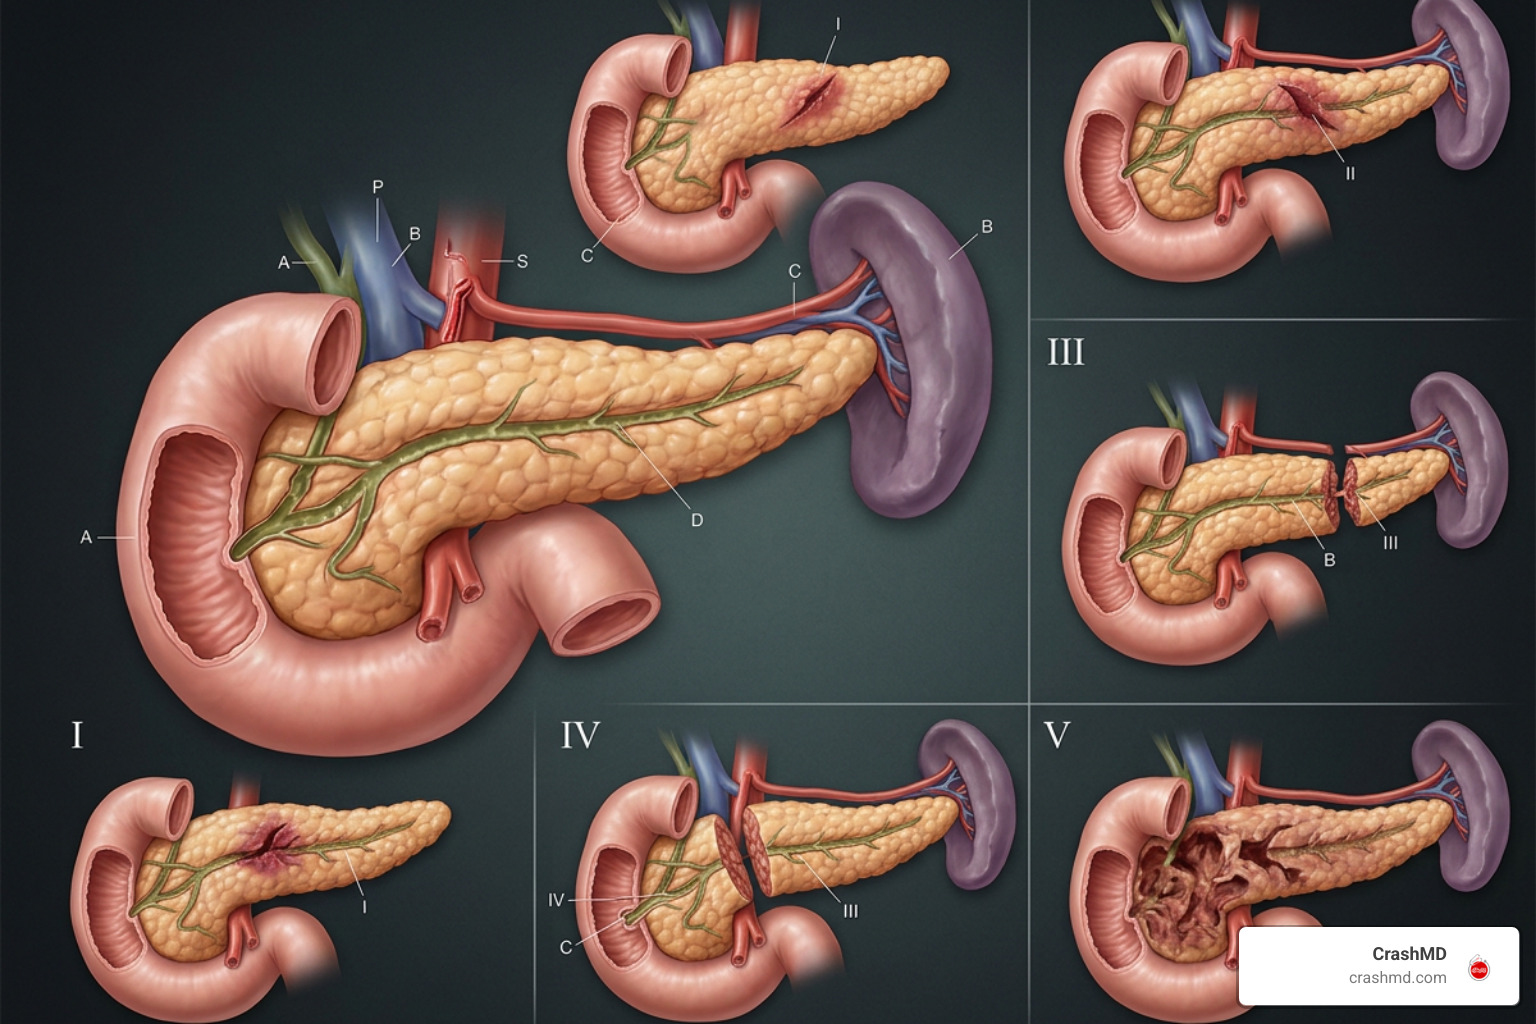
To categorize damage, trauma surgeons rely on the American Association for the Surgery of Trauma (AAST) Organ Injury Scale:
- Grade I & II: Low-grade contusions or superficial lacerations without main duct disruption.
- Grade III: Distal parenchymal transection or duct disruption to the left of the superior mesenteric vein.
- Grade IV & V: Severe proximal transection, head injuries, or massive duodenal-pancreatic disruption.
The single greatest driver of long-term pancreas injury effects is main pancreatic duct disruption. When the duct tears, digestive enzymes leak into surrounding abdominal space. These active enzymes erode adjacent blood vessels and tissues, frequently producing pancreatic fistulas in up to 50% of duct leaks and intra-abdominal abscesses in roughly 25% of cases.
| Trauma Mechanism | Common Injury Patterns | Complication Risks |
|---|---|---|
| Blunt Trauma (e.g., steering wheel, bicycle handlebar impact) | Direct compression against spine; transection of mid-body or tail | Delayed duct strictures, fluid collections, pancreatic pseudocysts |
| Penetrating Trauma (e.g., gunshot, stab wound) | Multi-organ destruction; high vascular and bowel co-injury | High initial infection, intra-abdominal abscesses, complex fistulas |
While penetrating trauma carries higher immediate morbidity, blunt abdominal trauma often leads to subtle, unrecognized duct tears that present months later as expanding pseudocysts or chronic strictures. For more details, review Scientific research on blunt pancreatic injury patterns and our Comprehensive guide to how pancreatic injury impacts the body.
Endocrine and Exocrine Consequences of Pancreatic Trauma
Post-Traumatic Diabetes Mellitus and Endocrine Dysfunction
When physical trauma damages the endocrine cells located inside the islets of Langerhans, blood sugar control collapses. This condition is categorized as Post-Pancreatitis Diabetes Mellitus (PPDM-A) or Type 3c Diabetes Mellitus. Research shows that up to 34% of pancreatic trauma survivors develop endocrine insufficiency over time.
Clinical guidelines emphasize waiting at least 90 days following initial injury before finalizing a permanent diabetes diagnosis. This 90-day window prevents misclassifying temporary stress-induced hyperglycemia as chronic islet cell destruction.
Patients with severe walled-off necrosis (WON) or extensive glandular damage exceeding 50% face the highest risk of long-term beta-cell loss. PPDM-A requires careful management because loss of pancreatic glucagon makes patients prone to sudden, severe low blood sugar episodes alongside persistent high blood sugar. You can explore Scientific research on post-pancreatitis diabetes mellitus for further clinical details.
Managing Long-Term Pancreas Injury Effects on Exocrine Function
Beyond regulating blood sugar, the pancreas produces essential digestive enzymes. Exocrine Pancreatic Insufficiency (EPI) occurs when injury or tissue scarring destroys more than 90% of the functional acinar cells. Without sufficient lipase, amylase, and protease, food passes through the digestive system unabsorbed.
Common symptoms of post-traumatic EPI include:
- Frequent, loose, pale, or oily stools (steatorrhea)
- Unintentional weight loss despite maintaining a normal diet
- Persistent abdominal bloating, gas, and cramping after meals
- Deficiencies in fat-soluble vitamins (A, D, E, and K), leading to bone density loss (osteoporosis)
Physicians evaluate exocrine function primarily using the Fecal Elastase-1 (FE-1) stool test. A level below 200 µg/g indicates mild-to-moderate insufficiency, while levels under 100 µg/g signify severe EPI. Managing this condition requires daily Pancreatic Enzyme Replacement Therapy (PERT) taken at every meal, alongside fat-soluble vitamin supplements. Read more in Scientific research on long-term pancreatic insufficiency.
Surgical Intervention vs. Non-Operative Management
Long-Term Pancreas Injury Effects Following Pancreatic Resection
Choosing between non-operative management and surgical resection depends heavily on main duct integrity. Grade I and II blunt injuries are managed conservatively with bowel rest, IV fluids, and strict observation. However, when the main duct is severed, surgery becomes mandatory to prevent catastrophic enzyme leakage.
Surgical resections come with long-term trade-offs:
- Distal Pancreatectomy: Removes the body and tail of the organ. While it eliminates the leak source, losing significant endocrine tissue increases the risk of late-onset diabetes.
- Pancreaticoduodenectomy (Whipple Procedure): Required for severe Grade IV/V trauma involving the pancreatic head and duodenum. It carries substantial long-term digestive adjustments, altered gastric emptying, and higher rates of EPI.
Patients who undergo conservative care for subtle injuries face alternative risks, such as delayed duct strictures, chronic parenchymal scarring, or recurrent fluid collections. Findings detailed in Scientific research on outcomes after severe pancreatitis reveal that long-term functional monitoring is critical regardless of whether initial treatment was surgical or conservative.
Chronic Pain, Mental Health, and Concomitant Injuries
Chronic neuropathic pain is one of the most debilitating long-term pancreas injury effects. Chronic inflammation stretches the pancreatic capsule and sensitizes nearby neural structures, particularly the celiac plexus. Patients often describe a deep, burning upper abdominal pain that radiates straight through to the back.
This persistent physical discomfort severely impacts mental health, frequently causing sleep disturbance, anxiety, and major depression. Managing chronic pancreatic pain requires a step-wise approach, starting with non-opioid analgesics and pregabalin before considering nerve blocks or endoscopic decompression.
Furthermore, isolated pancreatic trauma occurs in less than 4% to 10% of cases. Over 90% of patients sustain co-injuries:
- Splenic Injuries (74.2% co-occurrence in penetrating trauma)
- Duodenal Trauma (frequently causing complex biliary-pancreatic fistulas)
- Major Vascular Damage (superior mesenteric vessels or inferior vena cava)
These combined injuries compound overall recovery times, extend hospital stays, and increase total disability rates. Check out Scientific research on chronic pancreatitis clinical features and our Survival guide for pancreatic injury severity.
Pediatric Considerations, Cancer Risk, and Surveillance
Pediatric Growth and Development Impact
Children are particularly vulnerable to blunt abdominal injuries, such as landing forcefully on bicycle handlebars or suffering seatbelt compression during car crashes. Children have thinner abdominal walls and less retroperitoneal fat, leaving the pancreas exposed to direct compression against the lumbar spine.

Fortunately, pediatric patients possess strong healing potential. Non-operative management is successfully utilized in many pediatric Grade I-III injuries. However, long-term monitoring remains essential:
- Nutritional Tracking: Malabsorption from post-traumatic EPI can stunt childhood growth velocity and delay developmental milestones.
- Bone Density Support: Reduced absorption of Vitamin D and calcium requires proactive dietary support to protect developing bones.
- Pseudocyst Surveillance: Children frequently develop post-traumatic pseudocysts weeks after minor impacts, requiring ultrasound follow-ups.
Learn more through Scientific research on long-term outcomes in pancreatic trauma survivors.
Long-Term Pancreatic Cancer Risk and Monitoring Protocols
A lesser-known consequence of severe pancreatic injury is an elevated risk of pancreatic ductal adenocarcinoma (PDAC). Chronic, ongoing inflammation causes cellular damage and fibrous tissue remodeling. Research indicates that patients who develop post-traumatic chronic pancreatitis face a 1% to 2% lifelong risk of developing pancreatic cancer.
To manage these long-term risks, specialists recommend structured surveillance protocols:
- Annual Blood Chemistry: Monitoring fasting blood glucose, HbA1c, and serum fat-soluble vitamin panels.
- Non-Invasive Stool Tests: Checking Fecal Elastase-1 annually or whenever bowel habits change.
- Advanced Cross-Sectional Imaging: Utilizing Magnetic Resonance Cholangiopancreatography (MRCP) or Endoscopic Ultrasound (EUS) every 2 to 3 years if chronic pancreatitis, duct strictures, or persistent mass lesions develop.
Frequently Asked Questions about Long-Term Pancreas Injury Effects
How long after a pancreatic injury can post-traumatic diabetes develop?
Post-traumatic diabetes (PPDM-A) can manifest anywhere from 3 months to several years after the initial injury. While early blood sugar spikes often stem from hospital stress, permanent islet cell loss typically causes glycemic deterioration between 1 and 3 years post-injury.
What digestive problems occur after long-term damage to the pancreas?
Long-term exocrine damage leads to fat malabsorption. Typical symptoms include persistent pale, greasy, or floating stools, urgent diarrhea after high-fat meals, severe abdominal gas, and unintentional weight loss due to unabsorbed nutrients.
Can non-operative management lead to strictures or pseudocysts later in life?
Yes. Patients managed non-operatively—especially those with unrecognized low-grade duct injuries—can develop delayed duct strictures due to scar tissue formation. This blockage can cause recurrent acute pancreatitis or fluid collections known as pancreatic pseudocysts months or years later.
Conclusion
Navigating the long-term effects of a pancreas injury requires comprehensive medical care and meticulous personal advocacy. Because complications like post-traumatic diabetes, digestive failure, and chronic duct strictures often develop months or years after an accident, securing clear medical documentation is vital for both your healthcare recovery and any personal injury claim.
At CrashMD, we guide accident victims through every stage of physical recovery across Arizona, Nevada, Texas, Oklahoma, and California. We specialize in post-accident medical care, connecting patients with expert pain management specialists, gastroenterologists, and tailored treatment programs. Equally important, we advocate for you by thoroughly documenting your organ damage and long-term prognosis to support your legal claim before case settlement.
If you or a loved one are coping with the physical aftershocks of abdominal trauma, explore our Guide to pancreas injury legal documentation and access our Complete post-accident car crash recovery services. Together, we can build a clear roadmap toward healing and long-term health.