

When a Pancreas Injury Happens: What You Need to Know Right Away
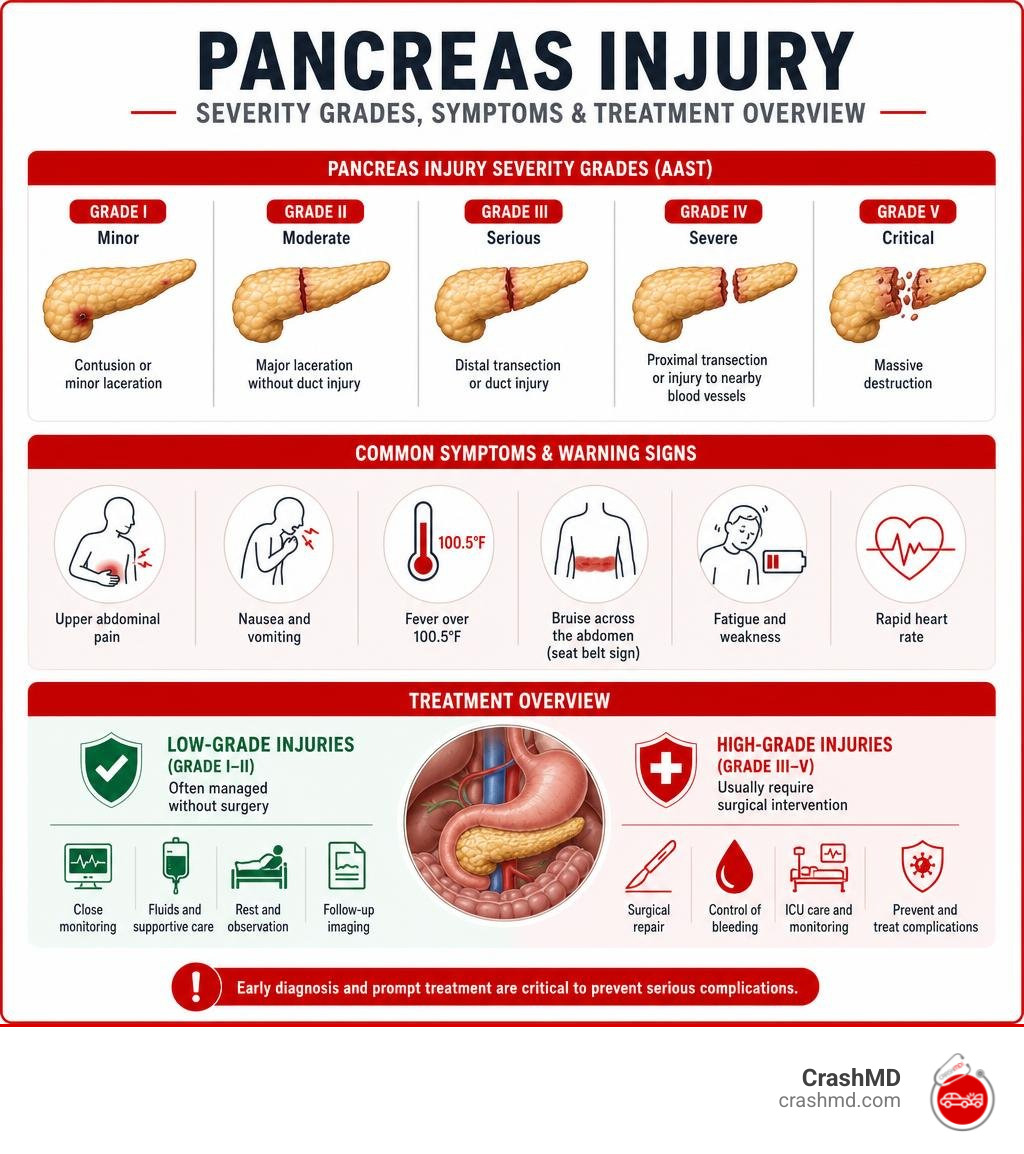
A pancreas injury is a rare but life-threatening condition that can happen after a car accident, a hard fall, or a blow to the abdomen — and it is often missed in the first hours after trauma.
Quick facts about pancreatic injury:
- What it is: Damage to the pancreas — the organ behind your stomach that controls digestion and blood sugar
- Most common cause: Blunt abdominal trauma, especially motor vehicle collisions (82% of blunt cases)
- How serious is it? Overall in-hospital mortality ranges from 9% to 34%
- Key warning signs: Upper belly pain, nausea, vomiting, fever over 100.5°F, and a bruise across the abdomen (called a “seat belt sign”)
- How it’s graded: The AAST scale rates injuries from Grade I (minor) to Grade V (massive destruction)
- Treatment depends on grade: Low-grade injuries are often managed without surgery; high-grade injuries usually require surgical intervention
I’m Dr. Adam Savage, and what makes pancreatic injuries so dangerous is how easily they hide. The pancreas sits deep in the abdomen behind the stomach, tucked against the spine. There are no obvious external wounds. Early CT scans miss the injury up to 53% of the time. And by the time symptoms become severe, serious complications may already be forming.
If you or someone you love was recently in an accident and is experiencing persistent upper abdominal pain, this guide will walk you through everything — from how these injuries are diagnosed and graded, to treatment options and recovery.
Understanding Pancreas Injury: Causes and Anatomical Vulnerability
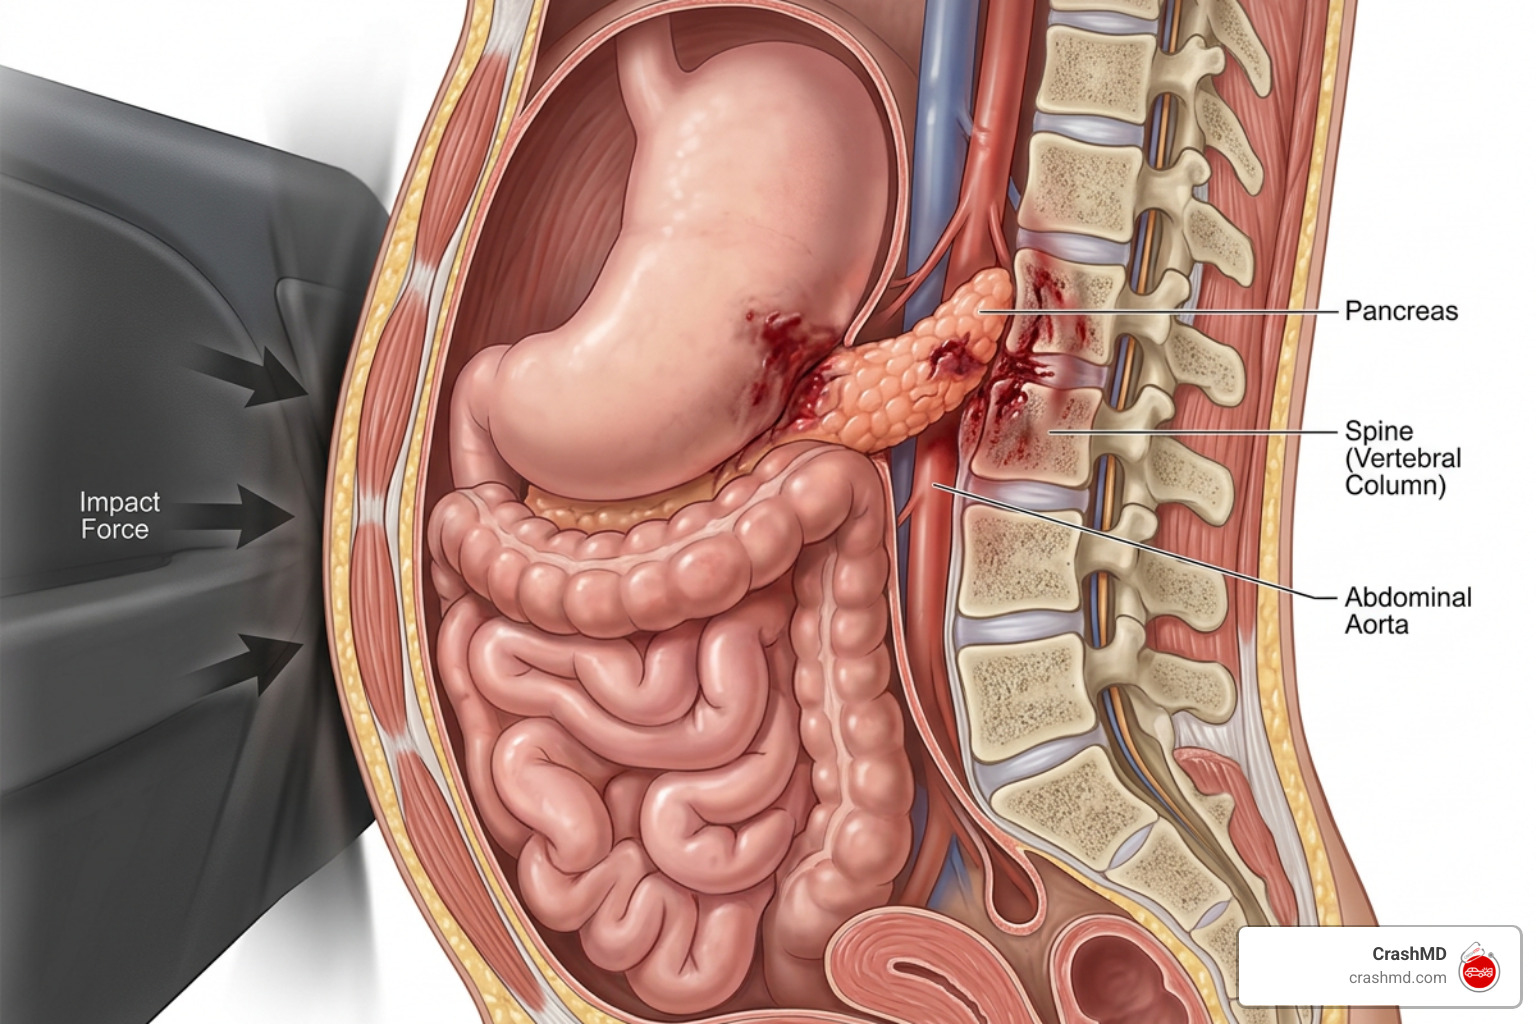
To understand why a pancreas injury is so dangerous, we have to look at where this organ lives. The pancreas is entirely retroperitoneal, meaning it sits deep in the back of your abdominal cavity, behind your stomach and in front of your spine.
Because of this hidden location, the pancreas is highly protected from minor bumps. However, during high-impact accidents, its position becomes its greatest vulnerability. When a sudden, crushing force is applied to your upper abdomen, the soft tissue of the pancreas is compressed directly against your hard vertebral column (spine). This “anvil effect” can easily bruise, tear, or completely transect (cut in half) the organ.
Blunt Trauma and Motor Vehicle Accidents
In the United States, blunt abdominal trauma is the primary driver of pancreatic damage, accounting for 37% to over 60% of cases depending on the region. According to a landmark Research on US adult pancreatic injuries, motor vehicle collisions (MVCs) cause a staggering 82.3% of all blunt pancreatic injuries.
When a car crashes, the steering wheel or a tightly locked seat belt can slam directly into the driver’s or passenger’s upper abdomen. This often leaves a telltale diagonal bruise known as a “seat belt sign.”
While penetrating trauma—such as gunshot or stab wounds—accounts for about 63% of pancreatic injuries globally, blunt trauma is much more common in everyday personal injury cases. If you want to dive deeper into how these forces damage internal organs during a crash, read our article on Pancreas Injury After Car Accident: Symptoms, Treatment, and Recovery.
Pediatric Vulnerability to Pancreas Injury
Children are uniquely vulnerable to a pancreas injury. Unlike adults, pediatric patients have very thin abdominal walls, underdeveloped abdominal muscles, and less visceral fat to insulate their internal organs.
A classic pediatric mechanism of injury is a bicycle accident where the child falls forward over the handlebars, causing the metal tip to strike the upper abdomen. This concentrated, blunt force compresses the child’s pancreas directly against their spine, often resulting in severe lacerations. To learn more about how pediatric trauma teams identify and manage these cases, check out the Pediatric pancreas injury guidelines.
Diagnostic Protocols and the AAST Grading System
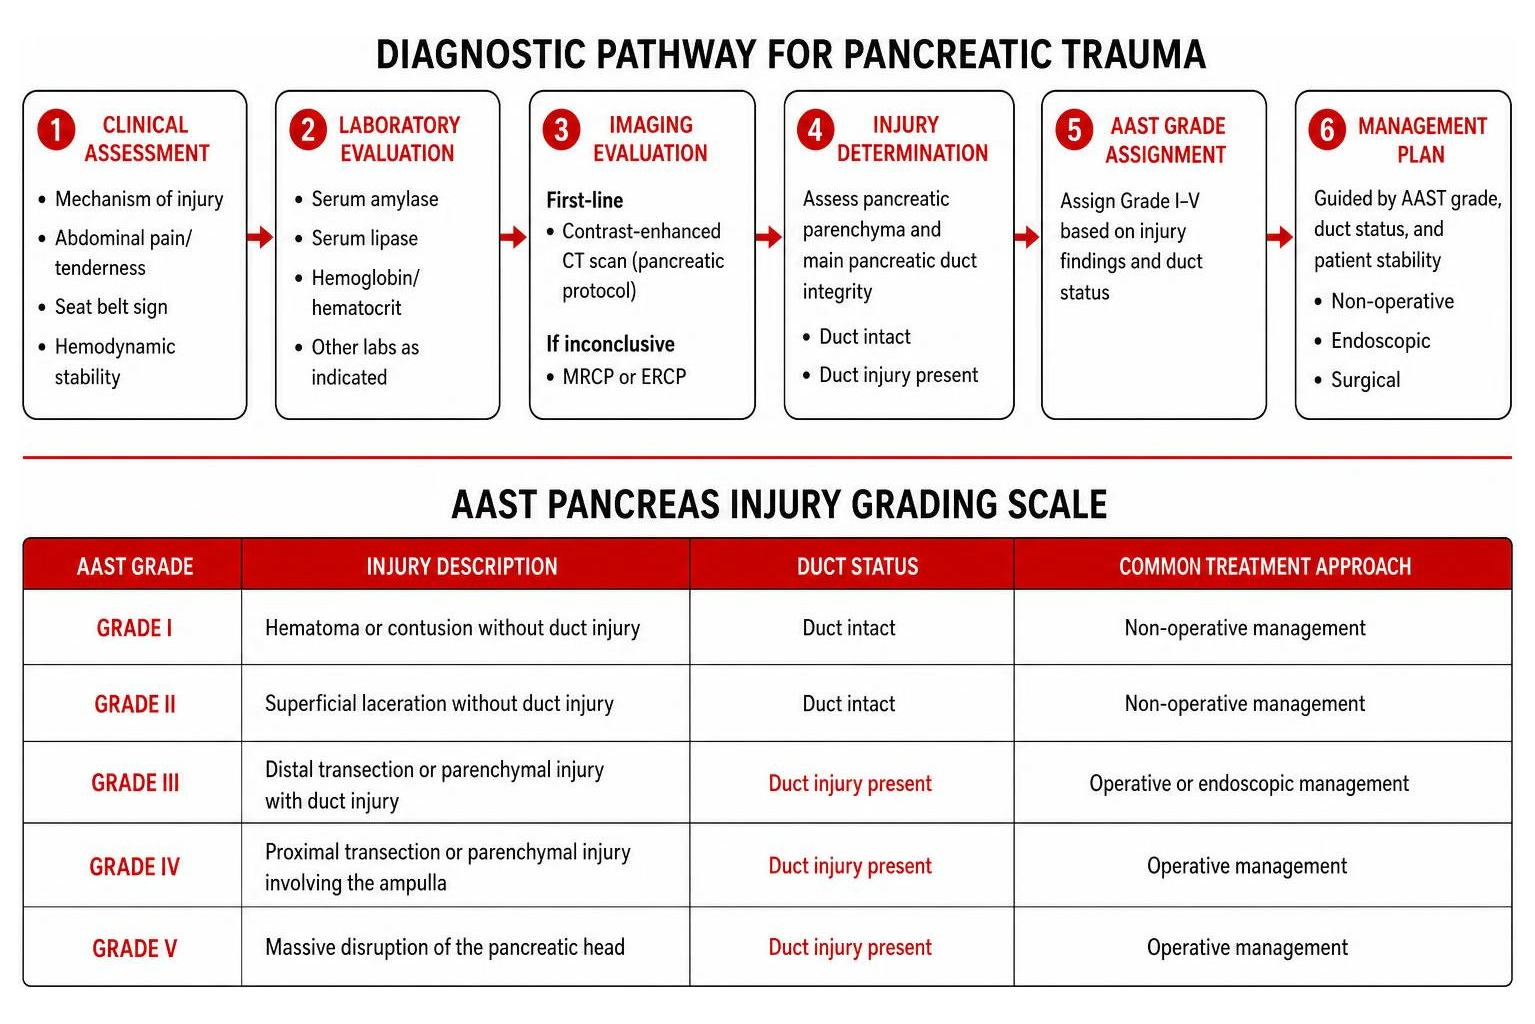
When a patient arrives at the emergency department after an accident, diagnosing a pancreas injury requires a highly systematic approach. Because the organ sits so deep, doctors rely on a combination of blood work, advanced imaging, and the American Association for the Surgery of Trauma (AAST) grading scale.
The AAST Pancreas Injury Grading Scale
The AAST scale is the universal language trauma surgeons use to describe the severity of a pancreas injury. This scale ranges from Grade I (least severe) to Grade V (most severe). The critical dividing line on this scale is the integrity of the main pancreatic duct. If the duct is torn, digestive enzymes will leak into the abdomen, requiring aggressive intervention.
| AAST Grade | Injury Description | Duct Status | Common Treatment Approach |
|---|---|---|---|
| Grade I | Minor contusion (bruising) or superficial laceration | Intact | Nonoperative observation |
| Grade II | Major contusion or laceration without tissue loss | Intact | Nonoperative observation / Drainage if needed |
| Grade III | Distal transection (tear in the body or tail) | Disrupted | Surgical resection (Distal Pancreatectomy) |
| Grade IV | Proximal transection (tear in the head) | Disrupted | Surgical resection or wide drainage |
| Grade V | Massive destruction of the pancreatic head | Disrupted | Complex surgical reconstruction (Whipple) |
Laboratory and Imaging Tests
To pinpoint the grade and plan treatment, we use several diagnostic tools:
- Amylase and Lipase Levels: These digestive enzymes spike when the pancreas is damaged. If blood tests taken more than 3 hours post-injury show completely normal amylase and lipase levels, there is a 95% negative predictive value—meaning we can be highly confident the pancreas is safe.
- CT Scans: A contrast-enhanced CT scan is the initial imaging test of choice. However, older scanners have variable sensitivities (47% to 79%), and early scans (within 2 hours of injury) often miss ductal damage because inflammation hasn’t fully set in yet.
- MRCP and ERCP: If we suspect a duct injury that isn’t clear on a CT scan, magnetic resonance cholangiopancreatography (MRCP) or endoscopic retrograde cholangiopancreatography (ERCP) are the gold standards, boasting diagnostic accuracies close to 90% to 100%.
For a complete breakdown of these guidelines, you can review the EAST Practice Management Guidelines.
Key Symptoms of a Pancreas Injury
Because a pancreas injury is so easily missed early on, patients and caregivers must watch for evolving clinical signs. Symptoms can take hours or even days to fully manifest as digestive enzymes slowly leak into the abdominal cavity. Key symptoms include:
- Severe, persistent pain in the upper abdomen (epigastric region) that may radiate straight through to the back
- Intractable nausea and vomiting
- A fever rising above 100.5°F (a sign of developing inflammation or infection)
- A “seat belt sign” or flank bruising (Grey Turner’s sign), which indicates severe internal bleeding. If you suspect internal bleeding, read our guide on Internal Hemorrhage After Trauma.
Treatment Pathways: Nonoperative vs. Surgical Management
Once we know the grade of the pancreas injury, we can establish a treatment pathway.
Nonoperative Management (Grades I-II)
For low-grade injuries where the main pancreatic duct remains completely intact, nonoperative management is the preferred path. This conservative approach includes:
- Bowel Rest: The patient is kept “NPO” (nothing by mouth) to stop the pancreas from producing digestive enzymes.
- Intravenous Fluids and Nutrition: Total parenteral nutrition (TPN) may be used to deliver nutrients directly into the bloodstream.
- Close Monitoring: Continuous clinical exams and repeat imaging ensure no delayed leaks develop.
In some stable cases with minor duct involvement, doctors may use endoscopic stenting (placing a small tube via ERCP) to bridge a minor tear and allow the duct to heal without surgery.
Surgical Intervention (Grades III-V)
When the main pancreatic duct is disrupted, or if the patient is hemodynamically unstable (experiencing severe internal bleeding or shock), immediate surgery is required.
- Grade III Injuries (Tail/Body): A distal pancreatectomy is performed, where the damaged tail and body of the pancreas are removed. If the spleen’s blood supply is compromised, the spleen may be removed as well.
- Grade IV Injuries (Head): These are highly complex. Simple drainage alone has a 92% failure rate, so surgeons often perform a resection or wide, closed-suction drainage to safely divert leaking enzymes.
- Grade V Injuries (Massive Head Destruction): This life-threatening scenario often requires a pancreaticoduodenectomy (Whipple procedure) to reconstruct the pathways between the pancreas, bile ducts, and small intestine.
For highly unstable patients, surgeons utilize “damage control surgery” to stop bleeding and contain leaks, delaying final reconstruction until the patient stabilizes. To learn more about how surgeons explore the abdomen during these emergencies, read our article on Abdominal Exploratory Laparotomy. You can also read the latest clinical updates on these operations in the Surgical management of pancreatic trauma review.
Complications and the Road to Recovery
The pancreas is filled with highly corrosive digestive enzymes. When damaged, these enzymes can literally begin to digest surrounding tissues, leading to a high rate of post-traumatic complications (occurring in up to 20% of patients).
Common Complications
- Pancreatic Fistula: An abnormal tunnel that forms when pancreatic fluid leaks out of the damaged duct and pools in the abdomen. We often treat persistent fistulas with somatostatin (or octreotide), a medication that temporarily shuts down pancreatic secretions.
- Pseudocyst: A localized collection of pancreatic fluid, blood, and debris that forms a wall around itself. While some resolve on their own, others require drainage.
- Post-Traumatic Pancreatitis: Severe, painful inflammation of the pancreas that occurs in about 7.5% of trauma cases.
- Intra-abdominal Abscess: A localized infection that can cause severe sepsis if not drained and treated with antibiotics.
The Road to Recovery: Diet and Activity
Recovering from a pancreas injury requires strict adherence to lifestyle modifications to avoid overworking the healing organ:
- Strict Low-Fat Diet: Because the pancreas produces the enzymes needed to digest fat, patients must consume a low-fat diet (often restricted to under 25 grams of fat per day) to let the organ rest.
- Hydration: Staying aggressively hydrated is crucial for healing.
- Activity Restrictions: No rough play, running, jumping, or contact sports are allowed for several weeks. Pediatric patients returning to school should carry lightweight backpacks (limiting weight to one or two textbooks) and leave classrooms five minutes early to avoid being bumped in crowded hallways.
- Medication Warnings: Avoid giving ibuprofen (Advil, Motrin) or other NSAIDs unless explicitly cleared by your trauma doctor, as they can increase bleeding risks. Acetaminophen (Tylenol) is generally preferred for mild pain.
For detailed home care instructions, parents and caregivers can refer to the UCSF home care guidelines.
Frequently Asked Questions about Pancreatic Trauma
Can a pancreas injury cause chronic pancreatitis?
Yes. Severe blunt force abdominal trauma can cause permanent scarring or a stricture (narrowing) in the pancreatic duct. This physical blockage prevents digestive enzymes from flowing properly, which can trigger recurrent bouts of acute pancreatitis and eventually lead to permanent, painful chronic pancreatitis years down the road.
Why are pancreas injuries frequently missed on initial CT scans?
Because the pancreas sits deep within the retroperitoneum, early trauma-related swelling, fluid accumulation, or minor tears may not show up on a CT scan performed within the first two hours of an accident. It often takes several hours for the inflammatory process to progress enough to be visible on standard imaging.
What is the survival rate for a pancreas injury?
The overall survival rate is highly favorable if the injury is diagnosed quickly, with mortality ranging from 9% to 34%. Most deaths associated with pancreatic trauma are actually caused by severe bleeding from co-existing injuries to nearby major blood vessels, the liver, or the spleen, rather than the pancreas itself.
Conclusion
A pancreas injury is a complex, hidden threat that requires expert medical evaluation and a meticulous recovery plan. Because these injuries are easily missed in the chaotic hours following an accident, having a dedicated medical advocate on your side is critical.
At CrashMD, we specialize in guiding accident victims through the entire post-trauma healing process. We operate across Arizona, Nevada, Texas, Oklahoma, Southern California, and Northern California, offering expert pain management, tailored treatment plans, and comprehensive patient advocacy.
Beyond helping you heal, we ensure that every aspect of your internal injuries is thoroughly documented. This meticulous medical-legal documentation is vital for protecting your rights and securing the resources you need for long-term recovery before taking any legal action. If you or a loved one has suffered abdominal trauma, read our A Comprehensive Guide to Pancreas Injury Legal Documentation and contact us today to secure the expert care you deserve.