

Causes, Mechanisms, and Risk Factors of a Rupture Pancreas
The pancreas is an elongated organ located in the retroperitoneum, positioned transversely across the upper posterior abdominal wall. Because of this anatomical position, a rupture pancreas typically requires high-energy impact.
Pancreatic trauma occurs in approximately 3% to 15% of all abdominal trauma cases, with blunt force impacts accounting for the majority of these injuries compared to penetrating wounds (at a ratio of about 3:1).
Because high-energy impacts affect the entire torso, isolated traumatic injuries to the pancreas are rare. Between 50% and 98% of cases involve concomitant injuries to surrounding intra-abdominal organs, including the liver, spleen, duodenum, major vascular structures, or kidneys.
Blunt Force Impacts and Spinal Compression
The primary mechanism driving a traumatic rupture pancreas during blunt force trauma is direct force compressing the organ against the rigid lumbar vertebral column (specifically the L1 and L2 vertebrae).
Common scenarios include:
- Motor vehicle accidents: The abdominal steering wheel impact or rapid restraint from a seatbelt creates sudden deceleration force.
- Handlebar impact: Bicycle or motorcycle collisions where the end of a handlebar strikes the epigastrium directly.
- Direct crush or heavy fall: High-impact domestic or occupational falls, such as striking the upper abdomen against a hard object.
Because two-thirds of all pancreatic injuries occur across the body of the pancreas, this force frequently results in a transection or fracture where the organ bridges the spine. The remaining 20–30% of injuries are split between the pancreatic head, neck, and tail.
Identifying Symptoms of Rupture Pancreas Injuries
Recognizing a rupture pancreas early is notoriously difficult because initial clinical presentation is often surprisingly mild. Patients may only complain of vague epigastric discomfort shortly after an accident.
Key symptoms and clinical signs to watch for include:
- Persistent Epigastric Pain: Deep, severe upper abdominal pain that frequently radiates directly to the back.
- The “Seatbelt Sign”: Bruising across the upper abdomen indicating significant blunt pressure.
- Peritoneal Irritation: Progressive abdominal rigidity, rebound tenderness, and guarding as digestive enzymes leak into the abdominal cavity.
- Elevated Enzyme Markers: Serum amylase or serum lipase levels elevate in approximately 80% of pancreatic trauma cases. However, initial levels taken immediately in the emergency room carry low sensitivity; persistently rising levels over time are far more diagnostic.
- Systemic Signs: Persistent leukocytosis (elevated white blood cell count), unexplained tachycardia (rapid heart rate), low-grade fever, or progressive abdominal distension.
To learn more about tracking symptoms and severity, review our Pancreas Injury Survival Guide Severity Symptoms.
Diagnostic Modalities and Main Pancreatic Duct Integrity Assessment
Accurate diagnosis depends on determining whether the main pancreatic duct (Wirsung’s duct) remains intact. A disrupted main duct allows active digestive juices to escape, causing severe tissue self-digestion and fluid collection.
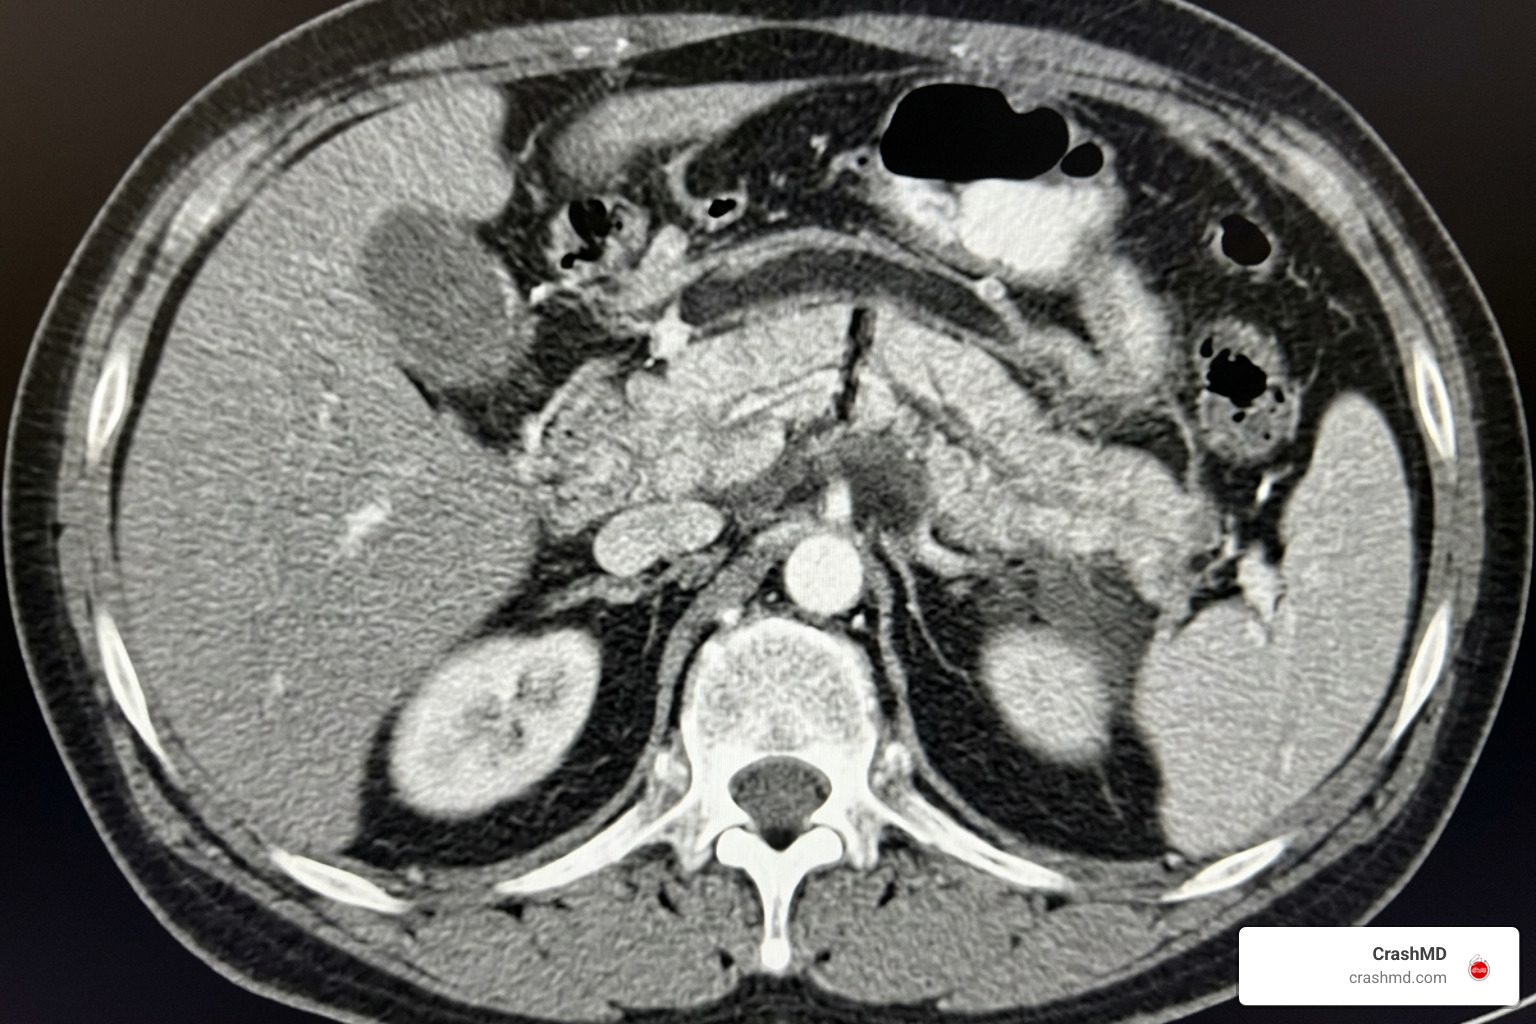
Initial evaluation typically starts with a Contrast-Enhanced Computed Tomography (CT) scan in the portal venous phase. CT scans identify pancreatic structural changes with a sensitivity of roughly 71.4% to 85%. Radiologists look for direct signs (hypodense laceration lines, complete transection) and indirect signs (peripancreatic fat stranding, fluid collections in the lesser sac).
To categorize the severity of damage, trauma surgeons utilize the American Association for the Surgery of Trauma (AAST) grading scale:
- Grade I: Minor contusion or superficial laceration without duct injury.
- Grade II: Major contusion or laceration without duct injury or tissue loss.
- Grade III: Distal transection or parenchymal injury with main pancreatic duct disruption.
- Grade IV: Proximal transection (to the right of the superior mesenteric vein) or parenchymal injury involving the ampulla.
- Grade V: Massive disruption of the pancreatic head.
When CT findings are inconclusive or suggest ductal involvement, secondary diagnostic modalities are required:
- Magnetic Resonance Cholangiopancreatography (MRCP): A non-invasive imaging method superior at visualizing ductal continuity without radiation or invasive entry.
- Endoscopic Retrograde Cholangiopancreatography (ERCP): An invasive endoscopic procedure that directly visualizes the duct via contrast injection, offering both diagnostic certainty and therapeutic stenting options.
For further clinical reading on diagnostic approaches, explore these articles on isolated traumatic rupture of the pancreas and clinical manifestations of acute pancreatitis.
Traumatic Rupture Pancreas vs Acute Pancreatitis
While both conditions involve inflammation and potential necrosis of pancreatic tissue, their underlying causes and treatment pathways differ significantly.
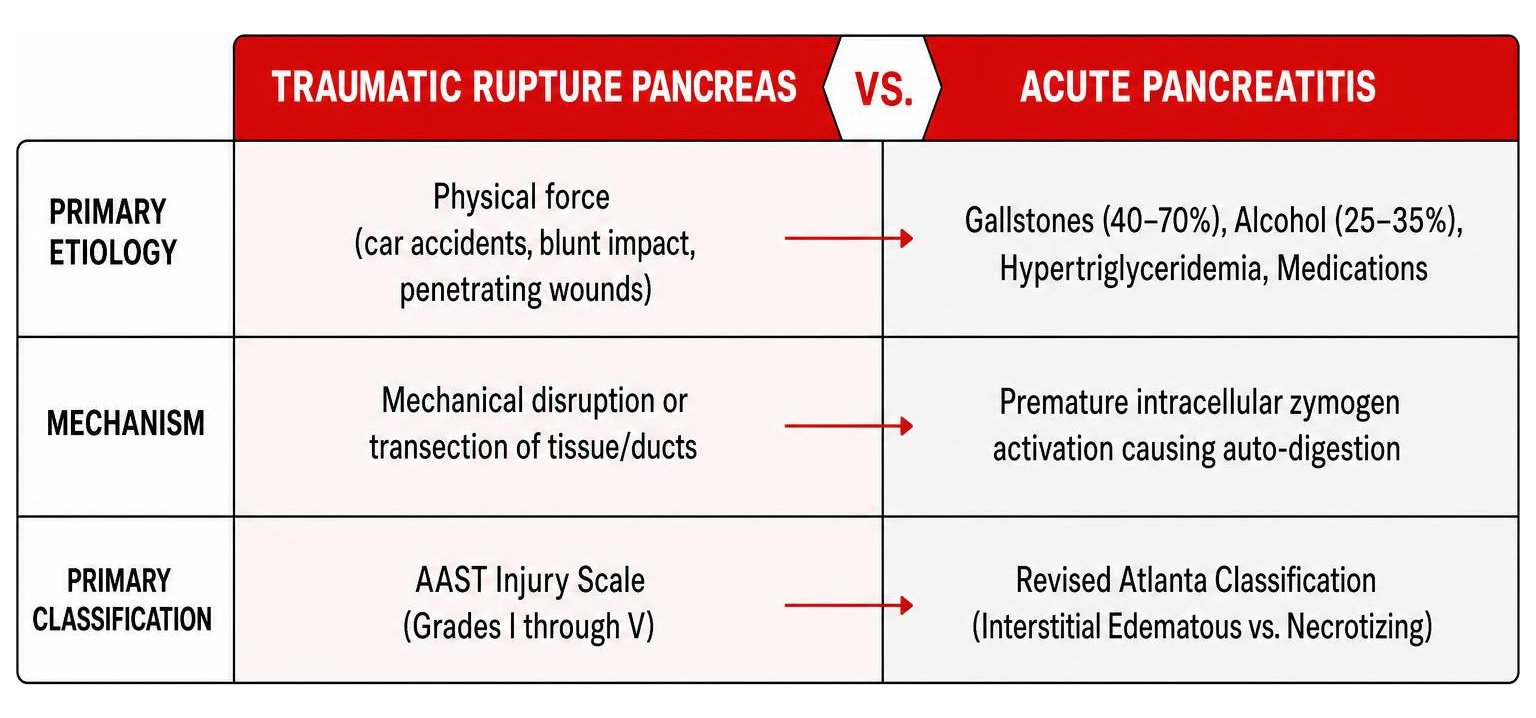
| Characteristic | Traumatic Rupture Pancreas | Acute Pancreatitis |
|---|---|---|
| Primary Etiology | Physical force (car accidents, blunt impact, penetrating wounds) | Gallstones (40–70%), Alcohol (25–35%), Hypertriglyceridemia, Medications |
| Mechanism | Mechanical disruption or transection of tissue/ducts | Premature intracellular zymogen activation causing auto-digestion |
| Primary Classification | AAST Injury Scale (Grades I through V) | Revised Atlanta Classification (Interstitial Edematous vs. Necrotizing) |
| Structural Integrity | Physical tearing/fracture of parenchymal tissue | Intact tissue framework initially; inflammatory swelling or localized necrosis |
| Treatment Focus | Surgical repair, debridement, stenting, or resection | Supportive care (IV fluid resuscitation, enteral nutrition, pain control) |
Treatment Strategies: Conservative Management vs Surgical Intervention
The choice between non-operative (conservative) management and surgical intervention depends on two factors: hemodynamic stability and main pancreatic duct integrity.
Non-Operative Conservative Management
Conservative management is appropriate for hemodynamically stable patients with Grade I or Grade II injuries where the main pancreatic duct remains intact. Treatment consists of:
- Intensive monitoring of vital signs and serial abdominal exams.
- Initial bowel rest paired with early enteral nutrition support.
- Goal-directed intravenous fluid resuscitation.
- Serial imaging (repeat CT or MRCP) to monitor for delayed fluid collections.
Surgical Interventions
When the main pancreatic duct is disrupted (Grades III, IV, and V), non-operative management carries a high failure rate. Surgical intervention or advanced endoscopic repair becomes necessary:
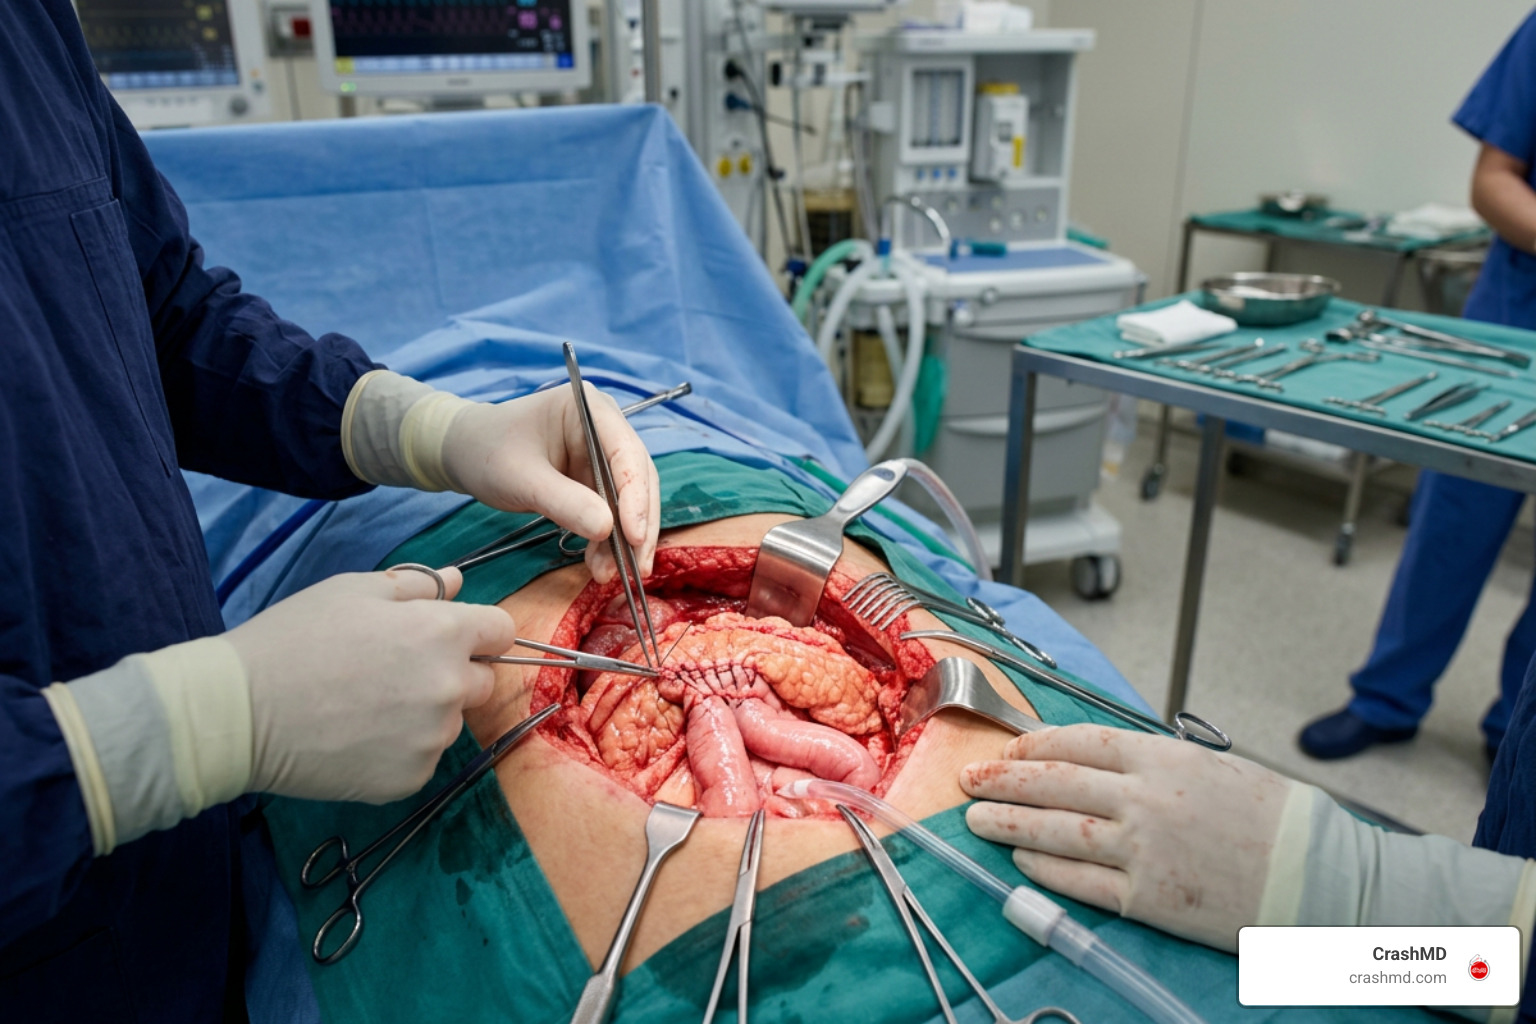
- Distal Pancreatectomy: For Grade III injuries located in the body or tail (to the left of the superior mesenteric vessels), surgeons typically perform a distal pancreatectomy (removing the damaged distal tissue), often preserving the spleen when stable.
- Roux-en-Y Pancreatojejunostomy: For complete transections where preserving pancreatic parenchyma is vital, surgeons debride necrotic tissue and attach a Roux-en-Y limb of the small intestine to the proximal or distal pancreatic stump to establish drainage.
- Wide Suction Drainage: Placed near repair or suture lines to evacuate escaping pancreatic juice before it damages adjacent structures.
- Endoscopic Duct Stenting: In select hemodynamically stable patients with partial main duct disruption, transpapillary pancreatic duct stenting via ERCP can bridge the rupture, allowing the duct to heal without major open surgery.
Additional clinical context regarding pancreatic inflammation management can be found in the StatPearls Acute Pancreatitis reference.
Postoperative Complications and the Impact of Delayed Diagnosis
Time is the most critical variable when treating a rupture pancreas. When surgical or endoscopic repair is performed within the first 24 hours, patient outcomes improve dramatically.
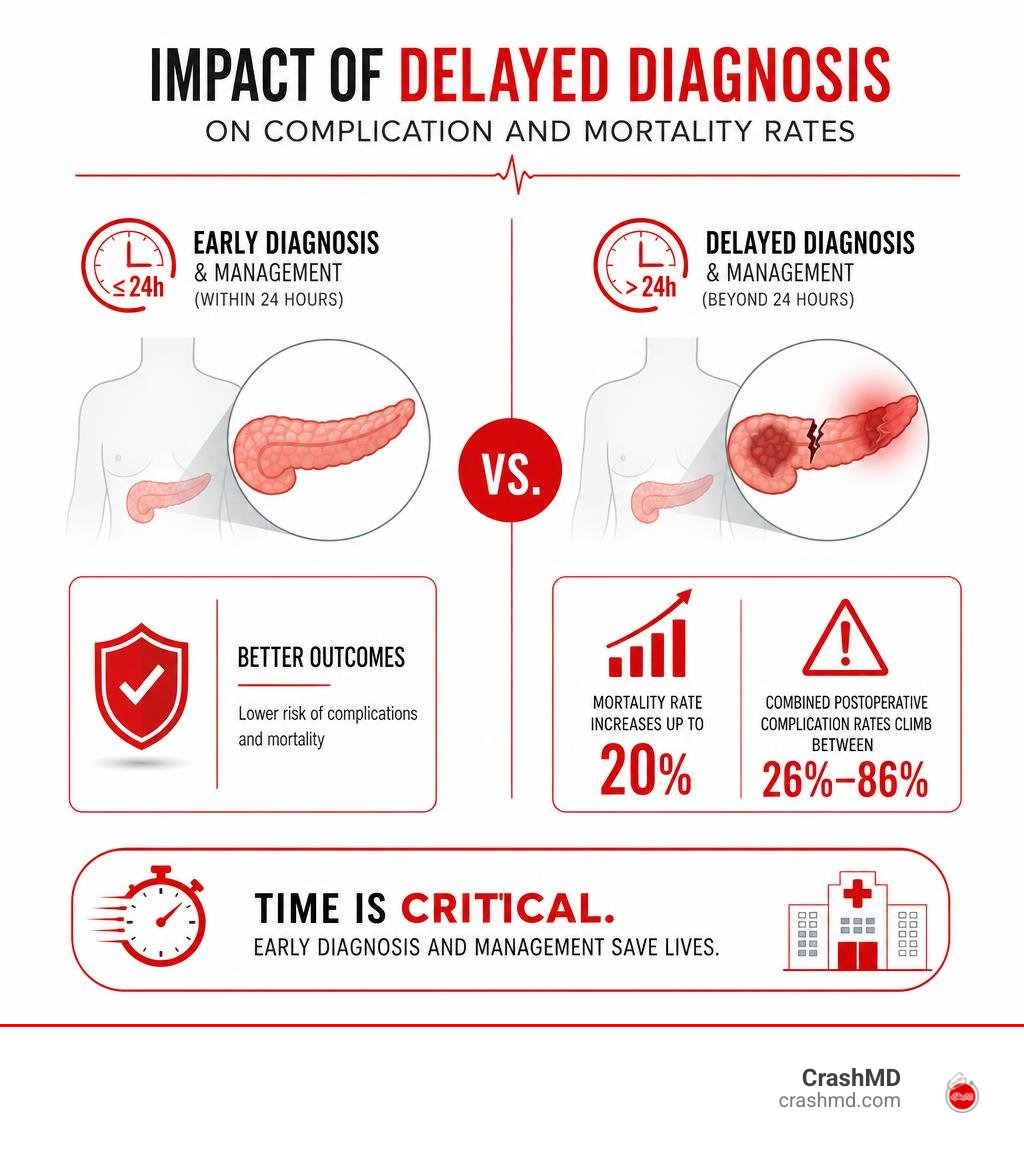
If diagnosis and management are delayed beyond 24 hours:
- Mortality rates increase up to 20%.
- Combined postoperative complication rates climb between 26% and 86%.
Common Postoperative Complications
Complications occur in up to 20% of all pancreatic trauma patients, rising substantially with higher-grade injuries:
- Pancreatic Fistula (4% to 37%): Occurs when digestive enzymes leak through damaged tissue or suture lines into the peritoneal cavity. Managed by maintaining wide closed-suction drains and checking drain amylase levels. Low-output fistulas often heal with conservative drainage and nutritional support.
- Pancreatic Pseudocysts (9%): Collections of pancreatic juice, inflammatory fluid, and debris encased in a wall of fibrous tissue. Large or symptomatic pseudocysts require endoscopic catheter drainage or surgical cystogastrostomy to prevent rupture.
- Intra-Abdominal Abscesses (6% to 15%): Infected fluid collections that require targeted percutaneous drainage and tailored antibiotic therapy.
- Post-Traumatic Pancreatitis (7.5%): Widespread severe inflammation of remaining tissue triggered by traumatic damage and premature enzyme activation.
For more details on recognizing severe complications, refer to the Mayo Clinic guide on pancreatitis symptoms and causes.
Navigating the medical care for these severe, delayed complications requires complete documentation. For a step-by-step breakdown of managing medical records after an accident, see our Comprehensive Guide to Pancreas Injury Legal Documentation.

Frequently Asked Questions About Pancreatic Rupture
How common is an isolated traumatic pancreatic rupture?
Isolated traumatic pancreatic rupture is extremely uncommon, occurring in less than 5% of major abdominal trauma cases. Because the pancreas is surrounded by the liver, stomach, spleen, duodenum, and major blood vessels, high-energy abdominal impacts cause concomitant damage to other internal organs in 50% to 98% of cases.
What is the single most critical factor in determining recovery from a pancreatic rupture?
The structural integrity of the main pancreatic duct (Wirsung’s duct) is the most critical factor determining patient outcomes. If the main duct remains intact (Grades I and II), non-operative management yields strong recovery rates. If the main duct is disrupted (Grades III–V), prompt surgical or endoscopic intervention within 24 hours is required to prevent widespread tissue necrosis and severe complications.
When is endoscopic stenting preferred over open surgery for pancreatic duct damage?
Endoscopic transpapillary stenting via ERCP is preferred when a patient is hemodynamically stable and has a partial (rather than complete) duct disruption. Stenting bridges the lacerated segment of the duct, allowing pancreatic enzymes to flow safely into the duodenum while the duct tissue heals, avoiding open abdominal surgery.
Conclusion
A traumatic rupture pancreas is a serious medical emergency where early, accurate diagnosis saves lives. Because symptoms can be subtle and initial imaging may not capture duct disruption, maintaining a high index of suspicion after any high-energy blunt force trauma is essential.
Recovering from a severe accident involving internal organ damage requires a multidisciplinary medical approach. At CrashMD, we guide accident victims across Arizona, Nevada, Texas, Oklahoma, and California through every stage of post-accident medical care. We advocate for your health, match you with expert pain management and surgical specialists, and meticulously document your injuries to support your full recovery.
If you or a loved one has suffered a traumatic abdominal injury in an accident, explore our resources at CrashMD to get the expert care and legal injury documentation you deserve.