

Understanding Your Liver Laceration Treatment Options
Liver laceration treatment depends on two main factors: how stable your blood pressure and circulation are, and how severe the injury is. Here’s a quick overview of what treatment typically looks like:
- Mild injuries (Grade I–II): Rest, monitoring, and pain management — no surgery needed
- Moderate injuries (Grade III–IV): ICU observation, possible angiography and embolization to stop bleeding
- Severe injuries (Grade V+): Emergency surgery, including damage control procedures
- Key rule: If you are hemodynamically stable (blood pressure is holding), doctors will almost always try to avoid surgery first
The liver is the most commonly injured abdominal organ — and the good news is that over 86% of liver injuries are now treated without surgery. Most heal on their own with careful monitoring and supportive care.
That said, a liver laceration from a car accident can feel overwhelming. You may be dealing with serious pain, confusing medical decisions, and uncertainty about what comes next.
This guide breaks it all down in plain language — from injury grading and treatment options to healing timelines and when surgery becomes necessary. I’m Dr. Adam Savage, and I’ll walk you through everything you need to know to understand your diagnosis and your path to recovery.
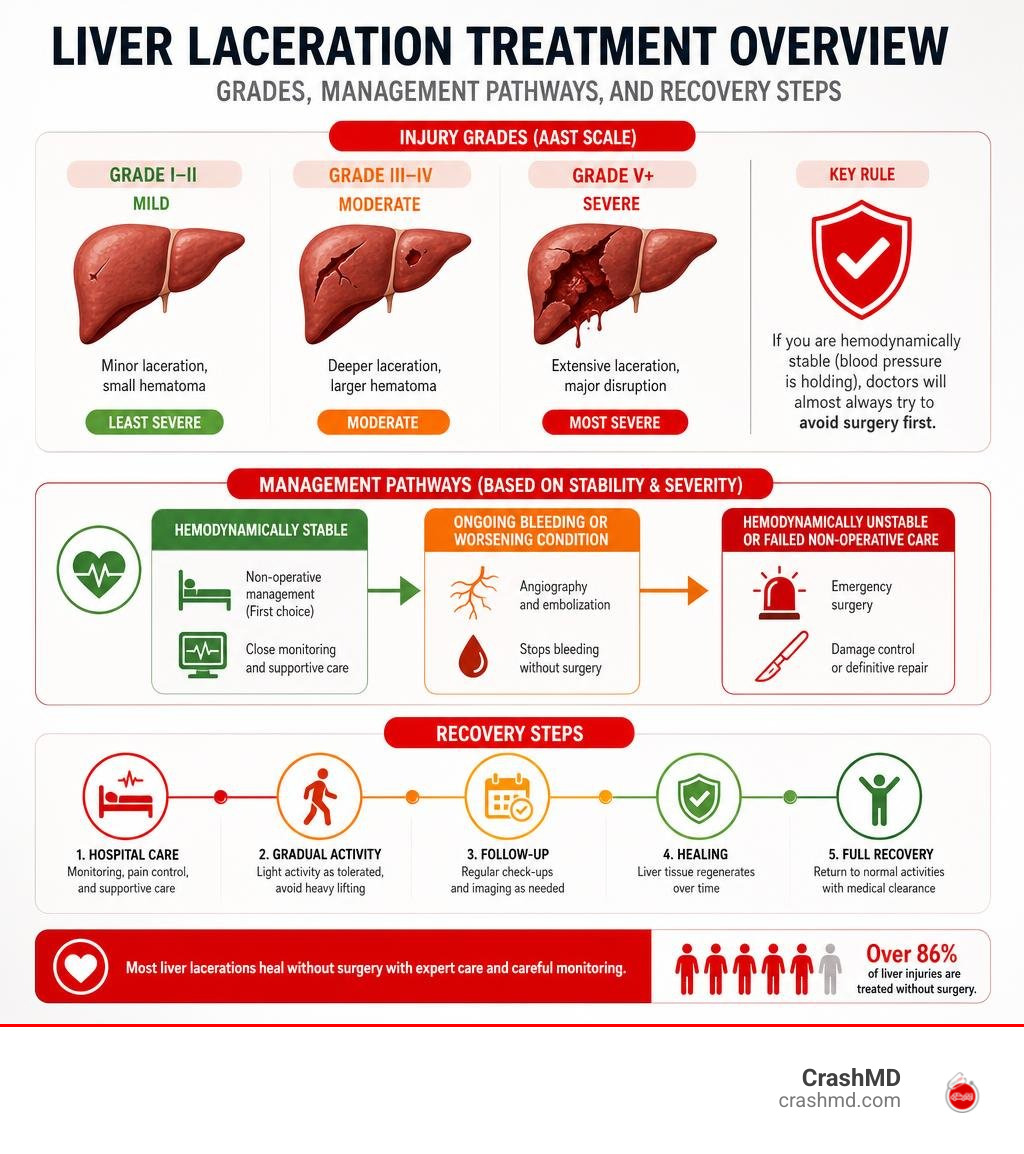
AAST Injury Scale and Diagnostic Evaluation
When a patient arrives at the emergency department after a motor vehicle collision, quick diagnostic imaging determines the presence and extent of internal organ damage. Doctors immediately perform a Focused Assessment with Sonography for Trauma (FAST) ultrasound at the bedside to check for free fluid or internal bleeding in the abdominal cavity. If the patient is hemodynamically stable, a contrast-enhanced computed tomography (CT) scan is conducted. CT scans offer 96% to 100% sensitivity and specificity, allowing trauma teams to precise-grade liver tears.
The American Association for the Surgery of Trauma (AAST) established a standardized organ injury scale from Grade I (least severe) to Grade VI (fatal hepatic avulsion). This system evaluates hematoma size, laceration depth, and parenchymal disruption.
| AAST Grade | Injury Description | Laceration Depth / Extent | Hematoma Extent |
|---|---|---|---|
| Grade I | Minor capsular tear / subcapsular hematoma | Laceration <1 cm deep | Subcapsular hematoma <10% surface area |
| Grade II | Moderate parenchymal tear / hematoma | Laceration 1–3 cm deep, <10 cm length | Subcapsular 10–50% surface area; intraparenchymal <10 cm |
| Grade III | Major tear / expanding hematoma | Laceration >3 cm deep | Subcapsular >50% surface area; expanding/ruptured hematoma |
| Grade IV | Major parenchymal disruption | Laceration involving 25–75% of a lobe or 1–3 Couinaud segments | Central intrahepatic hematoma |
| Grade V | Massive lobar disruption / vascular injury | Laceration >75% of a hepatic lobe or juxtahepatic venous injury | Massive vascular involvement (retrohepatic vena cava/portal vein) |
| Grade VI | Hepatic avulsion | Complete organ detachment / total vascular disruption | Total devascularization |
For a comprehensive medical reference, you can review the Scientific overview of hepatic injury classification.
Nonoperative vs. Operative Liver Laceration Treatment Pathways
In modern trauma care, the choice between nonoperative management and operative intervention rests primarily on hemodynamic status—meaning blood pressure, heart rate, and overall circulatory stability—rather than the numerical AAST injury grade alone. Stable patients with Grade III or Grade IV lacerations routinely undergo successful nonoperative observation in an intensive care unit (ICU) setting, involving serial physical exams and blood work every 4 to 6 hours. To learn more about navigating hospital protocols after an accident, read our detailed guide on the Post-Accident Protocol: Navigating Your Medical Journey.
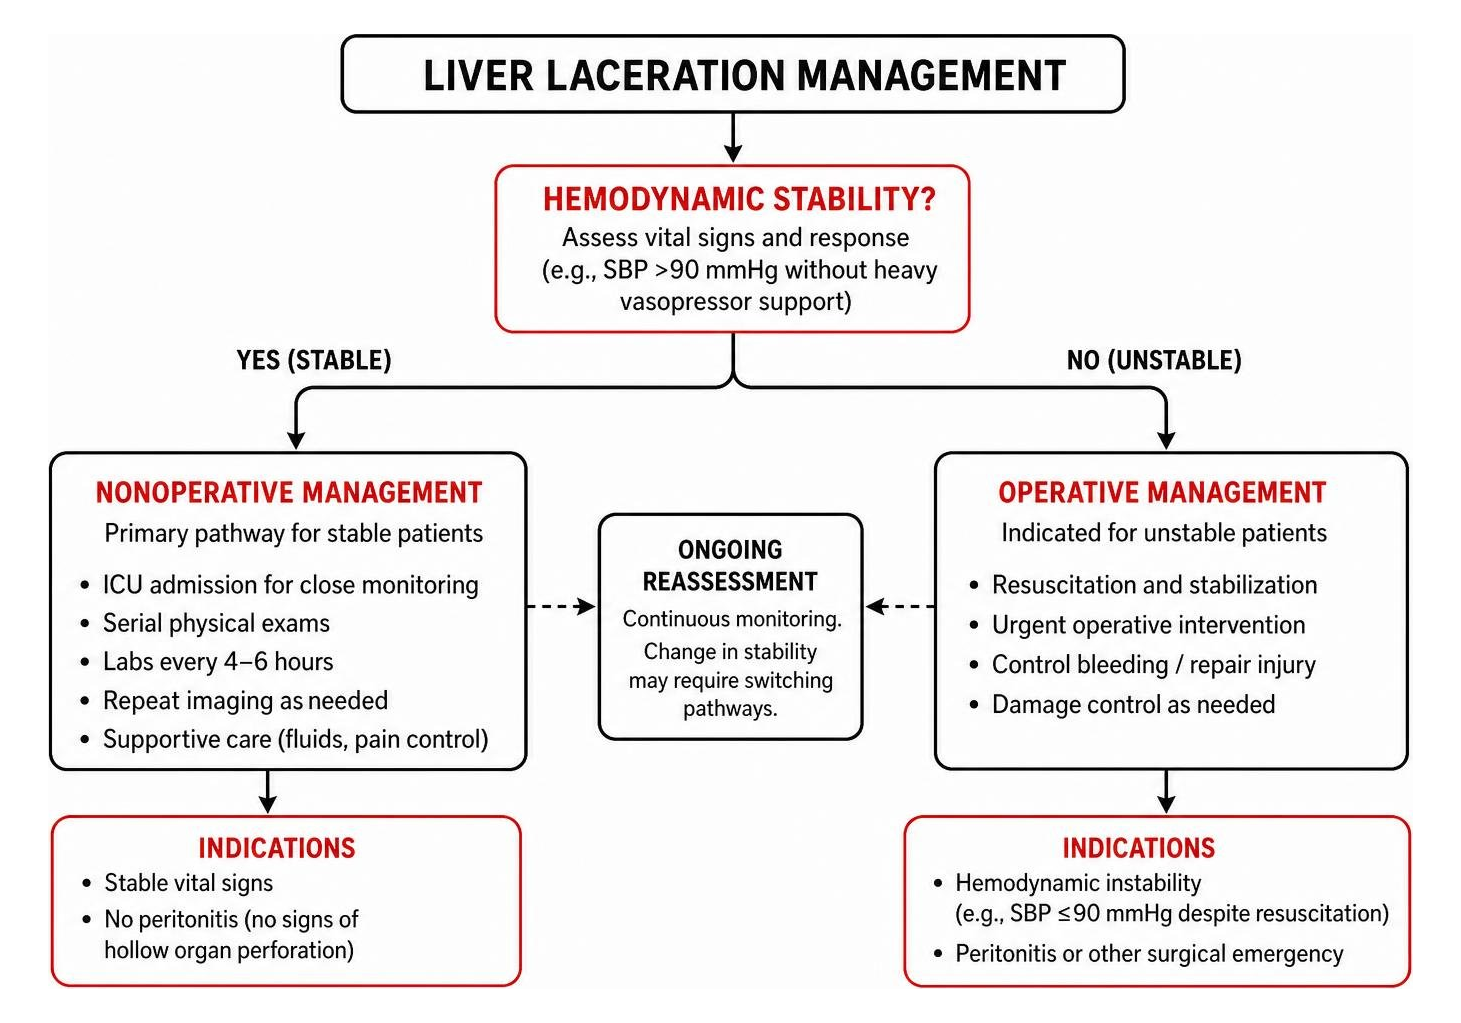
Indications for Nonoperative vs. Operative Care
Nonoperative management is the primary treatment pathway when:
- The patient maintains stable vital signs (systolic blood pressure >90 mmHg without heavy vasopressor support).
- There are no clinical signs of peritonitis (severe, rigid abdominal tenderness indicating hollow organ perforation).
- Diagnostic imaging shows no immediate requirement for open surgical intervention on other internal organs.
Operative management (exploratory laparotomy) is urgently indicated if the patient presents with hemodynamic collapse, active uncontained hemorrhage, or generalized peritonitis. Approximately 14% of hepatic trauma cases require operative intervention, either upon emergency room arrival or following a failure of conservative monitoring.
Angiography and Embolization in Liver Laceration Treatment
For nonoperative treatment, transcatheter arterial embolization (TAE)—performed by interventional radiologists—has transformed trauma care. When a CT scan shows active blood extravasation (frequently called a “contrast blush”) or a pseudoaneurysm, selective angiography is performed.
Interventionalists thread a catheter through the vascular system to the damaged hepatic artery branches, deploying small coils or embolic particles to achieve hemostasis without needing open surgery. Transcatheter embolization achieves up to an 83% success rate in halting arterial bleeding. For insights into endovascular techniques, see this Contemporary research on hepatic trauma management.
Pediatric vs. Adult Liver Laceration Treatment Protocols
Pediatric liver trauma protocols emphasize nonoperative care even more strongly than adult protocols. Because children’s blood vessels vasospasm effectively to self-contain bleeding, over 90% of pediatric liver injuries resolve without surgery or angioembolization.
In children, finding a contrast blush on a CT scan does not automatically trigger angiographic embolization if the child remains clinically and hemodynamically stable. Pediatric care relies heavily on ICU monitoring, absolute bed rest, fluid resuscitation, and strict physical activity restrictions upon discharge.
Complications, Blood Transfusions, and Medication Protocols
While conservative observation is effective, nonoperative management carries risks of secondary complications. The complication rate increases directly with the AAST injury grade: Grade III injuries carry a 1% complication rate, Grade IV reaches 21%, and Grade V rises to 63%.
Key potential complications include:
- Delayed Hemorrhage: Occurs in 2.8% to 3.5% of nonoperatively managed patients, usually within the first two weeks post-injury.
- Biliary Complications (Bilomas & Bile Leaks): Disruption of intrahepatic bile ducts occurs in about 3.2% of all liver trauma patients. Symptomatic fluid collections (bilomas) are routinely treated with image-guided percutaneous drainage or Endoscopic Retrograde Cholangiopancreatography (ERCP) with biliary stenting.
- Intrahepatic Abscesses: Developing in up to 4% of nonoperated liver trauma patients (and 5% of overall liver injuries due to devitalized tissue), liver abscesses are managed via percutaneous catheter drainage and targeted antibiotics.
When severe bleeding occurs, trauma units initiate a Massive Transfusion Protocol (MTP), delivering packed red blood cells, fresh frozen plasma, and platelets in a balanced 1:1:1 ratio.
Once active bleeding has safely stopped, chemical deep vein thrombosis (DVT) prophylaxis (such as low-molecular-weight heparin) is safely initiated to prevent blood clots without increasing nonoperative failure rates. To understand medical standards during recovery, review the WSES guidelines on liver trauma management and explore The Road to Recovery: What to Expect from Medical Care After a Car Accident.
Healing Timelines, Activity Restrictions, and Follow-Up Care

Healing times for liver trauma depend on the depth of the laceration and the presence of internal hematomas. Data reveals distinct median healing times across injury grades:
- Grade I Hematoma: Median 6 days
- Grade II Hematoma: Median 16 days; Grade II Laceration: Median 29 days
- Grade III Hematoma: Median 108 days; Grade III Laceration: Median 34 days
- Grade IV Laceration: Median 78 days
During the healing phase, strict physical activity restrictions are vital to prevent re-bleeding or delayed organ rupture. Patients must avoid contact sports, heavy lifting (>10–15 lbs), rigorous exercise, and high-impact activities for 6 to 12 weeks, depending on injury severity. Nonsteroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen, naproxen, or aspirin must be strictly avoided during acute recovery because they impair platelet aggregation and heighten bleeding risks; acetaminophen and prescribed non-blood-thinning pain medications are preferred.
For additional practical guidance on physical rehabilitation after traumatic impacts, read The Ultimate Guide to Post-Crash Physical Repair.
Criteria for Nonoperative Failure and Emergency Surgery
Nonoperative management is not guaranteed, and continuous clinical monitoring is essential. The primary criteria for nonoperative failure include persistent hemodynamic instability, dropping hemoglobin levels despite blood transfusions (>4 units within 8 hours), new peritonitis, or abdominal compartment syndrome.
When nonoperative care fails or an unstable patient presents immediately, surgeons perform damage control surgery (DCS). Rather than performing complex organ resections during acute crisis, the surgical team focuses on controlling hemorrhage and contamination:
- Perihepatic Packing: Placing surgical lap pads around the liver (“hepatic sandwich”) to compress bleeding parenchymal surfaces.
- Pringle Maneuver: Temporary clamping of the hepatoduodenal ligament to block hepatic arterial and portal venous inflow (safe for up to 60 minutes continuously in trauma settings).
- Resuscitation: Temporarily closing the abdomen and moving the patient to the ICU to correct the “lethal triad”—hypothermia (<34°C), metabolic acidosis (pH <7.2), and coagulopathy.
- Planned Re-exploration: Removing perihepatic packs in the operating room between 36 and 72 hours later once physiological stability is restored.
Frequently Asked Questions About Liver Lacerations
What is the most common cause of a liver laceration?
Blunt force abdominal trauma sustained in high-impact motor vehicle collisions is the single most common cause of liver lacerations. The large size and fixed position of the liver in the right upper quadrant make it particularly vulnerable to sudden deceleration impacts against seatbelts or steering wheels.
How long does it take for a liver laceration to heal?
Healing duration varies by severity. Minor Grade I and II tears typically resolve within 3 to 4 weeks. Moderate to severe Grade III and IV lacerations take between 5 weeks and 3 months to structurally heal. Full physical tissue remodelling for severe injuries can take several months.
When is surgery required for a liver laceration?
Emergency surgery is required if a patient becomes hemodynamically unstable, develops uncontained abdominal hemorrhage, shows signs of peritonitis, or fails conservative nonoperative observation despite blood transfusions and interventional angioembolization.
Comprehensive Post-Accident Recovery and Next Steps
Recovering from a major abdominal injury requires coordinated medical attention that extends far beyond your initial emergency room stay. At CrashMD, we guide accident victims through every stage of their post-injury journey. I’m Dr. Adam Savage, and our specialized medical team helps patients manage post-crash pain, coordinate ongoing specialist treatment, and thoroughly document all injuries for insurance and legal claims.
Serving patients across Arizona, Nevada, Texas, Oklahoma, Southern California, and Northern California, we act as your dedicated medical advocate, making sure your physical health is fully restored before you finalize any accident settlements. Reach out to us today to get expert guidance tailored to your recovery roadmap.