

Right Pulmonary Contusion ICD-10: The Quick Code Answer
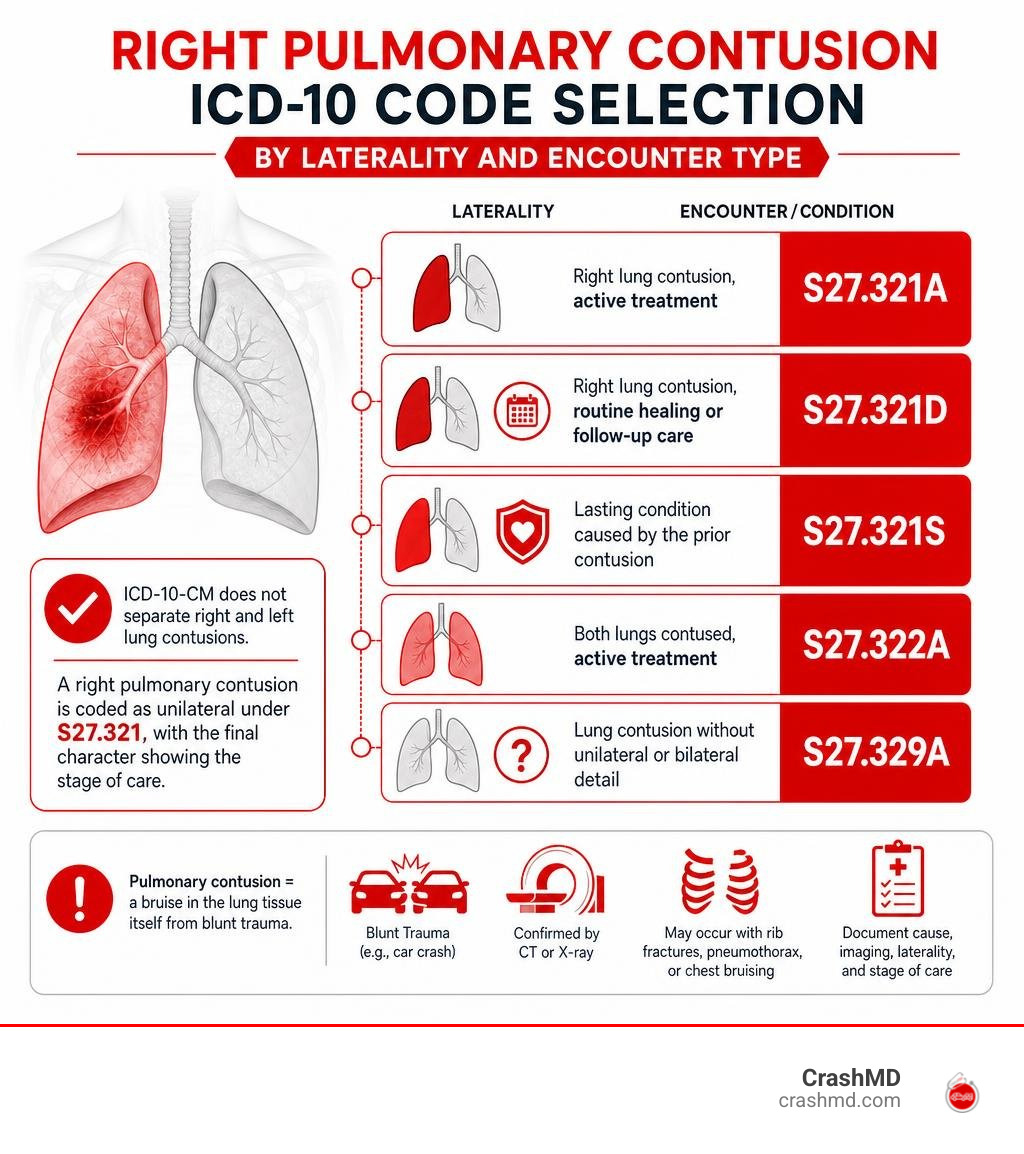
The right pulmonary contusion icd 10 code is S27.321A when the record confirms a unilateral lung contusion and the patient is receiving active treatment.
| Documentation scenario | ICD-10-CM code |
|---|---|
| Right lung contusion, active treatment | S27.321A |
| Right lung contusion, routine healing or follow-up care | S27.321D |
| Lasting condition caused by the prior contusion | S27.321S |
| Both lungs contused, active treatment | S27.322A |
| Lung contusion without unilateral or bilateral detail | S27.329A |
A key detail can prevent confusion: ICD-10-CM does not offer separate right- and left-lung contusion diagnosis codes. A documented right pulmonary contusion is coded as unilateral under S27.321, with the final character showing the stage of care.
This is different from a chest wall bruise or rib injury. A pulmonary contusion is a bruise in the lung tissue itself, often found on chest CT or X-ray after blunt trauma. It can occur after a car crash and may exist alongside rib fractures, pneumothorax, or superficial chest bruising.
Accurate records matter for both care and claims. The medical note should clearly support the traumatic cause, imaging findings, unilateral versus bilateral involvement, and whether the patient is receiving active treatment, follow-up care, or care for a lasting complication.
I’m Dr. Adam Savage, and the sections ahead explain how this code fits into diagnosis, documentation, injury sequencing, and recovery after chest trauma.
Easy right pulmonary contusion icd 10 glossary:
Navigating Right Pulmonary Contusion ICD 10 Guidelines and Specifications
When we review traumatic chest injuries in the ICD-10-CM coding system, lung contusions fall under category S27.32 (Contusion of lung). The system groups these codes based on whether the injury affects one lung (unilateral) or both lungs (bilateral).
Because the classification system does not break out distinct diagnosis codes for the right lung versus the left lung, a right-sided contusion relies on the unilateral category structure. A valid, billable claim requires a 7th character extension to define the encounter phase:
- A (Initial encounter): Assigned while the patient receives active treatment for the acute contusion (e.g., emergency department care, surgical evaluation, or ongoing inpatient stabilization). You can reference official criteria on the 2026 ICD-10-CM Diagnosis Code S27.321A page.
- D (Subsequent encounter): Assigned during routine follow-up care during the healing stage, such as outpatient re-checks or follow-up pulmonary function evaluations.
- S (Sequela): Assigned for late effects or chronic complications directly resulting from the original traumatic contusion.
Assigning S27.321 Codes for Right Pulmonary Contusion ICD 10 Cases
To code a right lung bruise correctly under HIPAA guidelines, we use subcategory S27.321 (Contusion of lung, unilateral). Even though the physical injury is localized specifically to the right parenchymal tissue, the diagnostic taxonomy classifies it as unilateral.
Failing to report the code to its full 7-character specification (such as submitting S27.321 without an encounter suffix) leads to clearinghouse claim rejections. Understanding these requirements helps prevent billing delays while ensuring medical charts clearly explain An Essential Guide To Pulmonary Contusion Risks.
Differences Between Pulmonary Contusion, Bronchus Injury, and Intrathoracic Organ Coding
We must carefully separate parenchymal lung tissue injuries from airway damage. A contusion of the bronchus involves the primary air passages leading into the lungs rather than the alveolar tissue.
For instance, a unilateral bronchial contusion is coded under category S27.4 (such as S27.421S ICD 10 Code – Contusion of bronchus, unilateral, sequela – Billable). Proper anatomical differentiation prevents compliance errors during medical audits:
- Pulmonary contusion (S27.32-): Bruising of the deep lung parenchyma, capillaries, and alveolar structures.
- Bronchus contusion (S27.42-): Direct traumatic bruising of the mainstem or lobar bronchial airways.
- Other intrathoracic organ injuries (S27.8-): Traumatic injury to mediastinal structures, pericardium, or major intrathoracic vascular trunks.
Clinical Diagnostics and Documentation Requirements for Lung Bruising
Pulmonary contusion is the single most common injury resulting from blunt thoracic trauma, occurring in 30% to 75% of blunt chest injury cases. Patients presenting with right lung contusions often exhibit localized chest pain, dyspnea, hemoptysis, reduced chest wall movement, and hypoxemia.
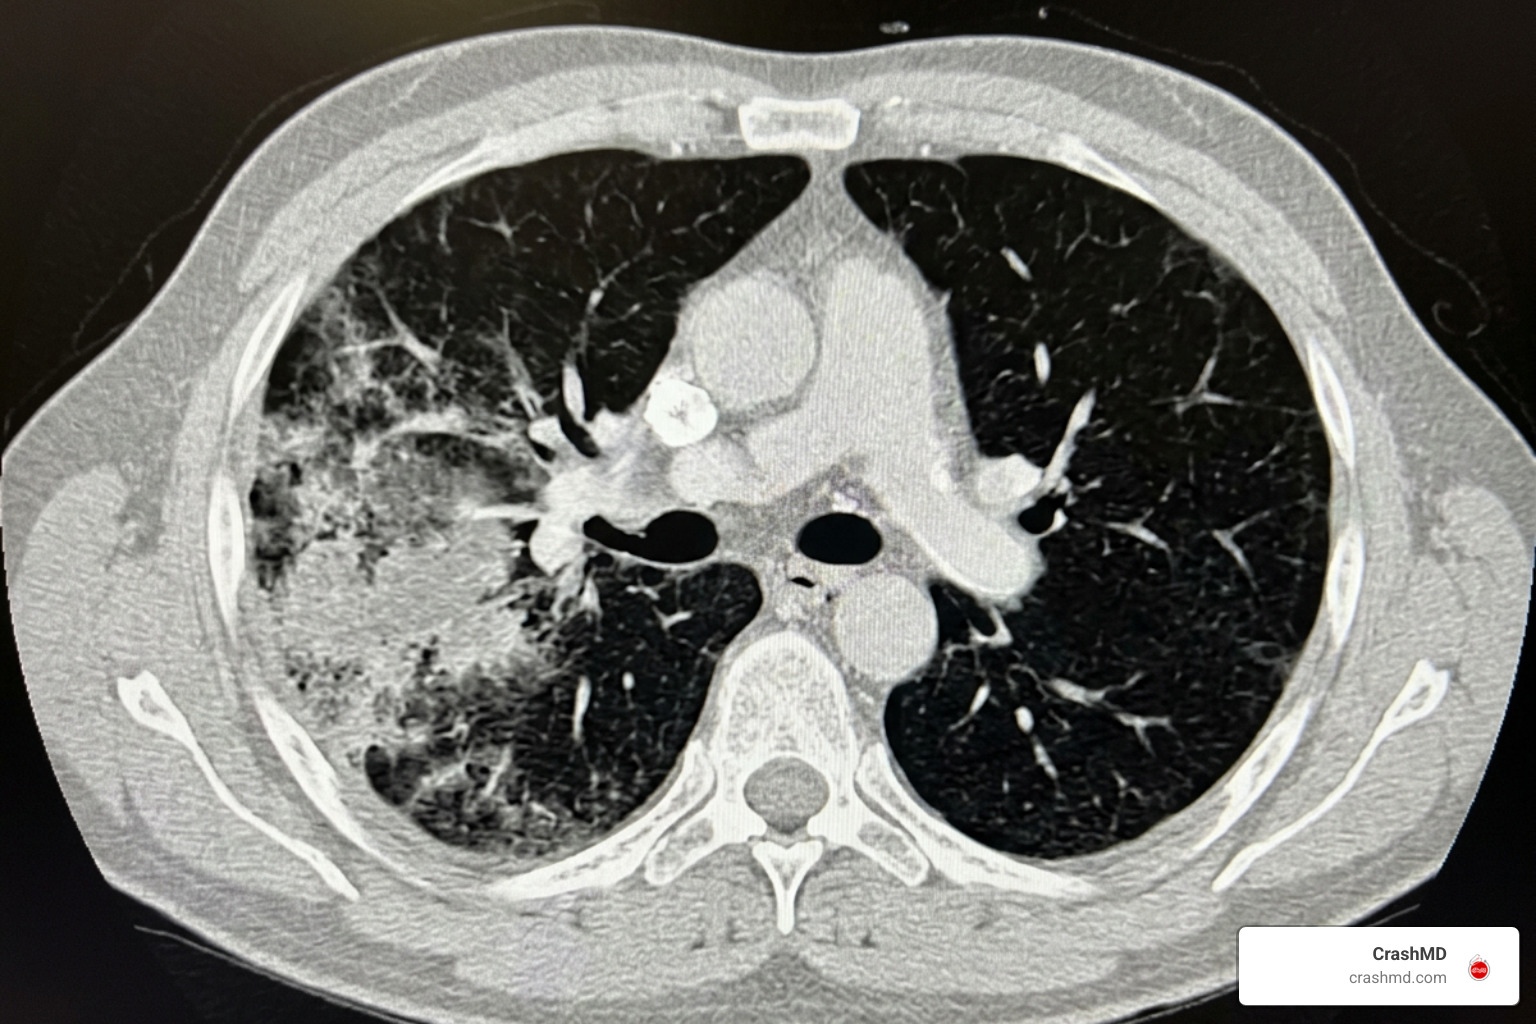
When we evaluate blunt force chest trauma after a motor vehicle collision, clinical documentation must capture physical examination findings along with serial blood gas measurements and continuous pulse oximetry. For more on diagnostic workflows, see our A Practical Guide To Pulmonary Contusion/.
Imaging Findings Supporting a Right Pulmonary Contusion ICD 10 Diagnosis
Diagnostic imaging remains the standard for validating a right pulmonary contusion icd 10 code assignment:
- Standard Chest X-Ray (CXR): Initial radiographs often underrepresent the injury because patchy parenchymal infiltrates may take 6 to 48 hours to fully consolidate on X-ray.
- Chest CT Scan: CT is the gold standard for early detection, revealing ground-glass opacities, air-bronchograms, and focal consolidation immediately following trauma.
Clinical research shows that when CT-based volume measurement indicates contusion involvement of 20 percent or more of total lung volume, the patient faces a significantly higher risk of developing Acute Respiratory Distress Syndrome (ARDS) and severe post-traumatic pneumonia. Coders can review Pulmonary Contusion – AI Documentation guidelines to align chart descriptions with these diagnostic criteria.
Crucial Documentation Elements, Laterality, and Audit Mitigation
To protect against audit risks and claim denials, clinical notes must explicitly record:
- Exact anatomical laterality: Stating “right lung contusion” in the chart narrative even though the diagnosis code groups into the unilateral classification.
- Imaging confirmation: Direct references to CT or CXR findings confirming lung tissue bruising while explicitly noting the presence or absence of concurrent conditions.
- Avoidance of unspecified codes: Defaulting to unspecified code S27.329A when laterality is documented creates immediate compliance flags and increases audit vulnerability.
Detailed charting practices are further described in our Step By Step Guide To Internal Chest Bruising/.
Differentiating Chest Wall Bruising vs Internal Pulmonary Contusion
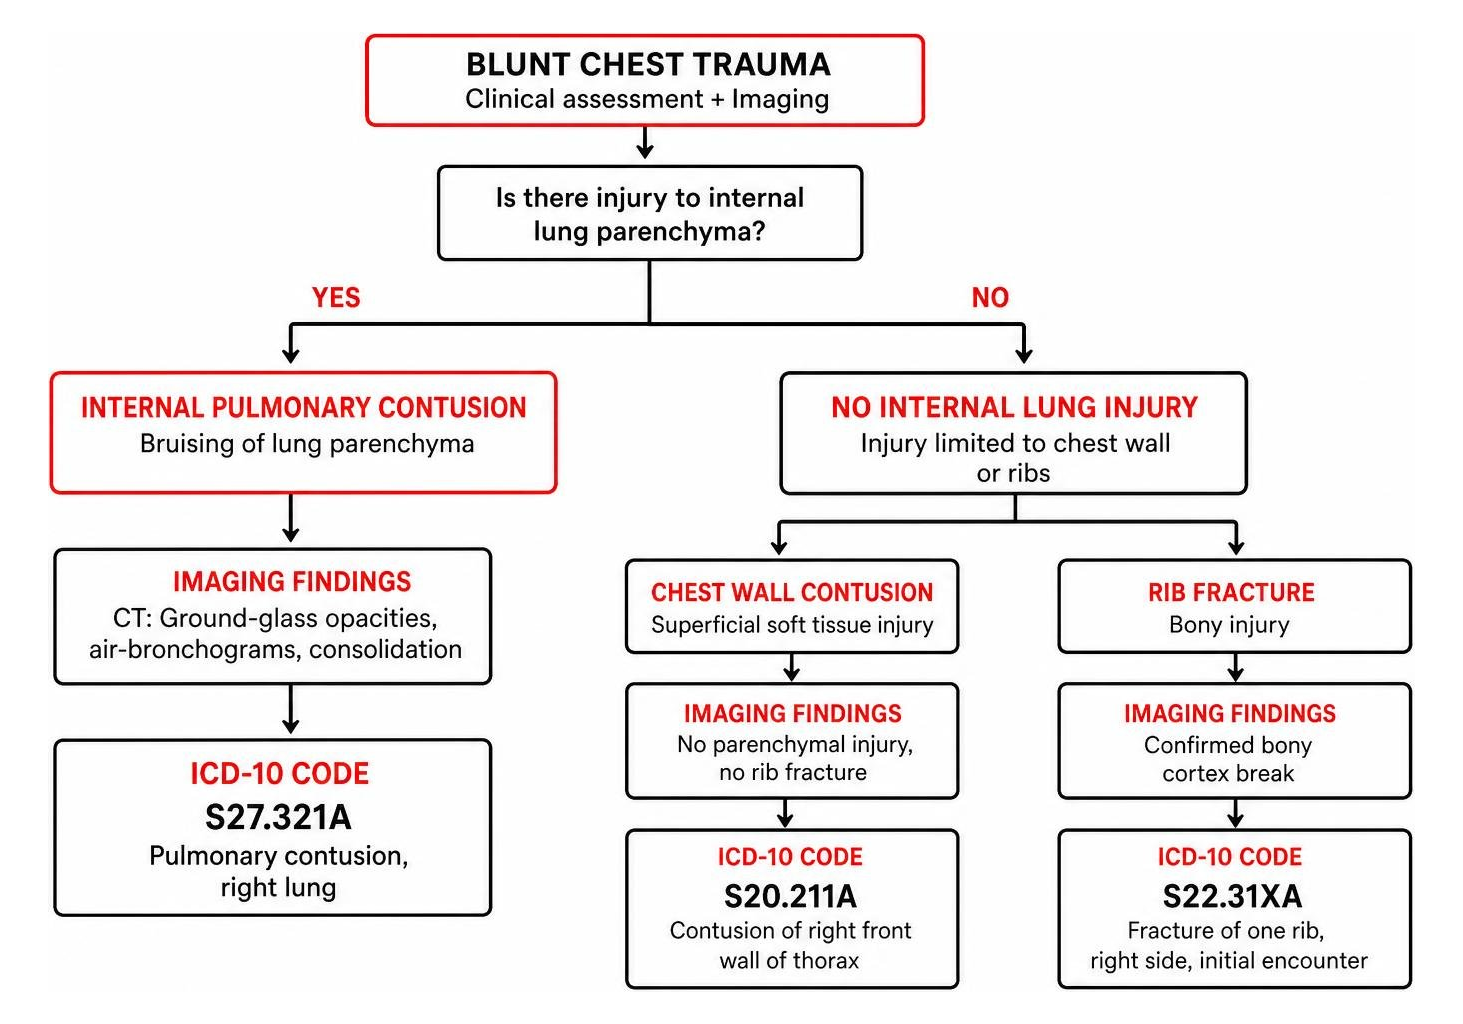
A frequent mistake in post-accident documentation is confusing a superficial chest wall contusion or rib bruise with an internal lung parenchymal contusion.
Superficial wall contusions involve the skin, fascia, and chest muscles outside the thoracic cavity, coded under S20.211A (Contusion of right front wall of thorax). Conversely, a lung contusion involves damage deep inside the thoracic cavity.
| Condition | Primary ICD-10 Code | Anatomical Depth | Imaging Validation |
|---|---|---|---|
| Right Front Chest Wall Contusion | S20.211A | Superficial wall tissue / fascia | Negative for parenchymal or rib injury |
| Right Rib Fracture (Single) | S22.31XA | Thoracic bony skeleton | Confirmed bony cortex break |
| Right Pulmonary Contusion | S27.321A | Internal lung parenchyma | Ground-glass opacities / infiltrates |
When coding superficial injuries, billers often reference the ICD-10 Coding for Right Rib Contusion ( S20.211A ) guide. If rib cartilage damage is present, refer to our Detailed Guide To Rib Cartilage Injury/.
Associated Injury Sequencing, External Cause Codes, and MS-DRG Reimbursement
When patients sustain multiple chest injuries during an accident, official ICD-10 sequencing guidelines dictate that internal intrathoracic organ injuries (category S27) are sequenced primary to superficial injuries or rib fractures (category S22).
External cause codes provide critical legal and clinical context regarding how the injury occurred:
- V00–V99: Transport accidents (e.g., V43.54XA for car occupants injured in collisions).
- W00–W19: Traumatic falls.
Proper diagnostic coding directly impacts inpatient hospital reimbursement through Medicare Severity Diagnosis-Related Groups (MS-DRGs). Inpatient admissions for pulmonary contusions are grouped into key MS-DRG categories depending on severity and comorbidities:
- MS-DRG 205: Other Respiratory System Diagnoses with Major Complications/Comorbidities (MCC) (relative weight ~1.8310).
- MS-DRG 206: Other Respiratory System Diagnoses without MCC (relative weight ~0.9411).
- MS-DRG 963–965: Other Multiple Significant Trauma categories.
For detailed analysis on coding relationships and DRG structures, review Pulmonary Contusion ICD-10: Codes, Sequencing, and DRGs – LegalClarity and our guidance on Injury Assessment What You Need To Know For Your Legal Case/.
Coding Sequelae and Long-Term Complications of Pulmonary Contusions
While many lung contusions resolve within a few weeks, severe blunt trauma can cause lasting parenchymal scarring or chronic pulmonary fibrosis years down the road.

When coding long-term complications (sequelae), ICD-10 guidelines require a two-code sequence:
- First-listed code: The specific residual manifestation (e.g., chronic post-traumatic pulmonary fibrosis).
- Secondary code: The original injury code with the 7th character S indicating sequela (e.g., S27.321S).
Understanding long-term outcomes is essential when evaluating injury timelines, as outlined in The Ultimate Guide To Rib Cartilage Injury Recovery Timeline/.
Frequently Asked Questions About Pulmonary Contusion Coding
What is the specific ICD-10 code for a right pulmonary contusion?
Because ICD-10-CM diagnosis codes do not contain distinct right-versus-left subcategory designations for lung contusions, a right pulmonary contusion is coded under the unilateral category S27.321. You must append a 7th character extension (such as S27.321A for active initial treatment) to create a valid, billable code.
How do you sequence rib fractures with a pulmonary contusion?
Per official ICD-10-CM coding conventions, internal intrathoracic organ injuries (S27.-) take precedence over bony thorax injuries. Therefore, sequence the pulmonary contusion code S27.321A first, followed by associated rib fracture codes (S22.-) as secondary diagnoses.
How does laterality assignment affect MS-DRG reimbursement?
Selecting specific unilateral (S27.321A) or bilateral (S27.322A) codes ensures accurate MS-DRG grouping (such as MS-DRG 205 or 206). Submitting an unspecified code like S27.329A can cause clearinghouse rejections, payer audits, and lower reimbursement due to lack of documented clinical complexity.
Conclusion and Patient Recovery Support
Accurate coding for a right pulmonary contusion icd 10 diagnosis relies on clear documentation of parenchymal lung involvement, laterality, and treatment stage.
At CrashMD, we help accident victims navigate recovery after blunt chest trauma. Operating across Arizona, Nevada, Texas, Oklahoma, Southern California, and Northern California, our team delivers specialized medical care and complete injury documentation to support both your health recovery and legal claims.
Explore our Car Accident Pulmonary Contusion Symptoms and Recovery Guide or contact our clinical team today to learn how we can assist in your post-accident healing journey.