

What You Need to Know About Pulmonary Contusion After a Crash
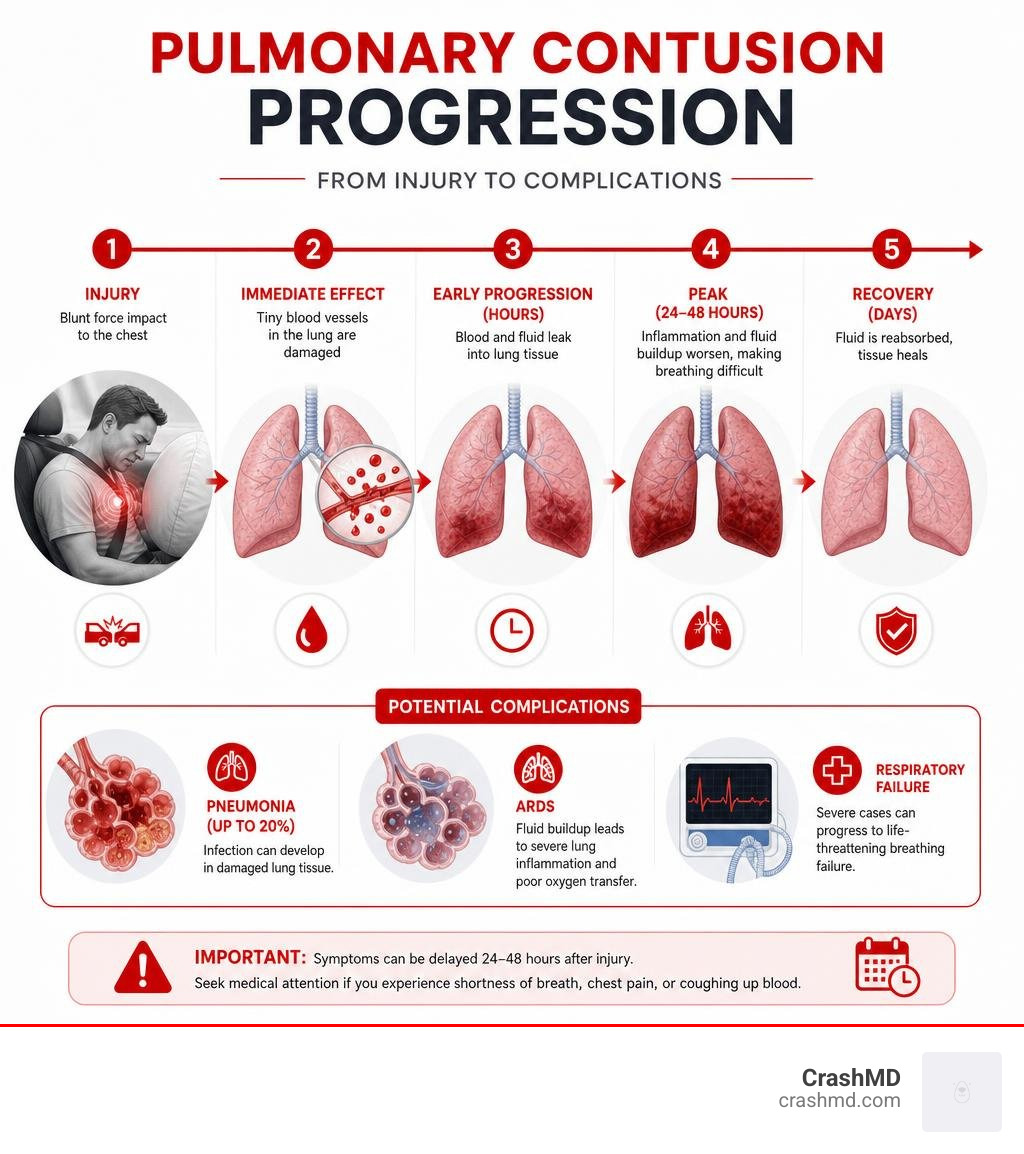
Pulmonary contusion — a bruise of the lung — is one of the most common and serious injuries that follows a car accident or any hard blow to the chest.
Here’s a quick summary:
| Key Fact | Detail |
|---|---|
| What it is | Bleeding and fluid buildup in lung tissue from chest trauma |
| Most common cause | Motor vehicle collisions (about 70% of cases) |
| How common | Affects 30–75% of blunt chest trauma patients |
| Main symptoms | Shortness of breath, chest pain, coughing up blood |
| Warning | Symptoms can be delayed 24–48 hours after injury |
| Healing time | Most cases resolve in 5–7 days with proper care |
| Mortality rate | Estimated between 14% and 40% depending on severity |
| Serious complications | Pneumonia (up to 20%), ARDS, respiratory failure |
If you were recently in a car accident and took a hard hit to the chest — even if you feel okay right now — this matters to you.
A pulmonary contusion is not always obvious at first. Your chest might feel sore, your breathing might seem slightly off, and you might assume it will pass on its own. But the injury can quietly worsen over the next day or two, sometimes leading to life-threatening complications.
This guide breaks down exactly what a pulmonary contusion is, how it’s diagnosed, how it’s treated, and what your recovery could look like — in plain language, without the medical jargon.
What is a Pulmonary Contusion and How Does It Occur?
In simple terms, a pulmonary contusion is a bruise on your lung. Just like a bruise on your arm or leg, it is caused by a blunt force that damages tiny blood vessels, causing blood and fluid to leak into the surrounding tissue.
However, because this happens inside your lungs, it is far more dangerous than a standard skin bruise. To understand why, we have to look at the lung parenchyma (the functional tissue of the lung).
Your lungs are made up of millions of microscopic air sacs called alveoli. These sacs are surrounded by tiny capillaries. In a healthy lung, oxygen passes from the alveoli into your blood, while carbon dioxide passes out. When you experience a chest injury, this delicate alveolar-capillary membrane is torn. Instead of filling with air, your alveoli fill with blood and inflammatory fluids.
According to the Pulmonary contusion overview on Wikipedia, a contusion differs fundamentally from other lung injuries:
- Pulmonary Laceration: A tear or cut in the lung tissue, often caused by a penetrating object (like a broken rib or a knife).
- Pulmonary Hematoma: A localized collection of blood that forms a distinct pool inside the lung tissue.
- Pulmonary Contusion: Widespread bleeding and fluid accumulation throughout the lung tissue without structural tears.
One surprising fact is that children are particularly vulnerable to severe pulmonary contusions. Because a child’s ribs are highly flexible and compliant, their chest wall can compress significantly during an impact without breaking any bones. This means a child can have life-threatening lung bruising with absolutely no broken ribs or external signs of chest trauma.
Common Causes of Pulmonary Contusion
A pulmonary contusion is the most common lung injury identified in blunt chest trauma, showing up in 30% to 75% of these cases. While we see this injury across a wide range of accidents, the primary causes include:
- Motor Vehicle Collisions: Car crashes account for roughly 70% of all pulmonary contusions. The rapid deceleration forces your chest against the steering wheel, dashboard, or seatbelt.
- Falls from Heights: Common in workplace accidents or among older adults.
- Sports Injuries: High-impact collisions in contact sports like football, rugby, or equestrian activities.
- Blast Injuries: The physical pressure wave from an explosion can bruise the lungs even without any external cuts or wounds.
Certain bone injuries are highly linked to lung bruises. For instance, a pulmonary contusion is the second leading injury associated with sternal (breastbone) fractures, occurring in a third of those cases. Furthermore, while scapular (shoulder blade) fractures are relatively rare, more than 90% of them are associated with severe internal chest injuries, including pulmonary contusion.
Age also plays a major role. In older adults, the chest wall is stiffer and more fragile. Data shows that 18.6% of older adult blunt trauma patients had clear evidence of a pulmonary contusion even after relatively low-energy incidents, such as a slip and fall at home.
The Three Physical Mechanisms of Alveolar Injury
When a blunt force hits the chest, the damage to the air sacs is caused by three distinct physical phenomena:
- The Spalling Effect: This happens where two materials of different densities meet. When the energy wave of a crash travels through the dense chest wall and hits the low-density, air-filled alveoli, it causes the tissue at the boundary to burst.
- The Inertial Effect: Different tissues inside your chest have different weights and densities. During a sudden stop, lighter alveolar tissue is stripped away from the heavier, denser bronchial tubes and blood vessels because they decelerate at different speeds.
- The Implosion Effect: The shockwave of the impact compresses the gas inside your alveoli. As the wave passes, this highly compressed gas rapidly expands (implodes), tearing the delicate alveolar walls.
Additionally, a contrecoup injury can occur. Just like a concussion can bruise the opposite side of the brain, the kinetic energy of a chest blow can bounce off the spine and bruise the lung on the opposite side of the initial impact.
Pathophysiology and Clinical Evolution of Lung Bruises
Once the initial impact occurs, a complex biological chain reaction begins. The physical tearing of the alveolar-capillary membrane triggers localized bleeding. Within hours, the body responds with a massive inflammatory reaction.
This inflammation leads to interstitial edema (fluid buildup in the spaces between cells), which causes the lung tissue to lose its elasticity and collapse. This creates a severe ventilation-perfusion (V/Q) mismatch. Simply put, blood is flowing past fluid-logged, collapsed air sacs that cannot provide oxygen. The blood returns to the heart without being oxygenated, resulting in progressive hypoxemia (low blood oxygen levels).
| Contusion Severity | Percent of Lung Volume Affected | Typical Clinical Picture |
|---|---|---|
| Mild | <10% | Mild shortness of breath; usually resolves quickly with basic oxygen support and rest. |
| Moderate | 10% to 20% | Obvious respiratory distress; requires close monitoring and supplemental oxygen. |
| Severe | >20% | High risk of respiratory failure; often requires intensive care and mechanical ventilation. |
Clinical Symptoms and Delayed Presentation
A patient with a lung bruise may experience:
- Dyspnea: Severe shortness of breath or difficulty breathing.
- Chest Pain: Often localized and made worse by breathing in or coughing.
- Hemoptysis: Coughing up blood or blood-tinged mucus.
- Tachypnea: Rapid, shallow breathing.
- Cyanosis: A bluish tint to the lips, skin, or fingernails, signaling a lack of oxygen.
The most dangerous aspect of a pulmonary contusion is its delayed presentation. Immediately after a car crash, you might feel completely fine other than some minor chest soreness. However, because fluid accumulation and the inflammatory response take time to build, symptoms often start subtly and peak between 24 to 48 hours post-injury.
Potential Complications: Pneumonia, ARDS, and Respiratory Failure
If a lung bruise is left unmonitored or unmanaged, it can easily spiral into life-threatening complications:
- Pneumonia: Because the lung is filled with pooled blood and fluid, and the patient is often breathing shallowly due to pain, it becomes a perfect breeding ground for bacteria. Up to 20% of all people with a pulmonary contusion develop pneumonia. In severe, hospitalized cohorts, this number can jump as high as 38.4%.
- Acute Respiratory Distress Syndrome (ARDS): This is a catastrophic inflammatory condition where fluid floods both lungs, making breathing nearly impossible. Studies indicate that while only 6.8% of general contusion patients develop ARDS, that number skyrockets to 82% if more than 20% of the lung volume is bruised.
- Respiratory Failure: The leading causes of death within the first month of sustaining a lung bruise are ARDS (44.1%) and secondary respiratory infections (26.5%).
To understand how doctors analyze these risks, you can read the Scientific research on predicting respiratory complications. Over the long term, severe contusions can also lead to permanent lung fibrosis (scarring) and reduced lung compliance.
Diagnosis, Management, and Advanced Therapies

Managing a lung bruise requires a careful balance. Because there is no “magic pill” to cure a bruised lung, medical care focuses on keeping your oxygen levels up, controlling pain, and preventing secondary infections while your body heals itself. You can explore the medical evolution of these treatments in the Contemporary management of pulmonary contusions.
How a Pulmonary Contusion is Diagnosed
Diagnosing a lung bruise quickly is critical, but it isn’t always straightforward:
- Chest X-rays: While commonly used in emergency rooms, X-rays are notoriously unreliable early on. A lung bruise may not show up on an X-ray for an average of 6 hours post-injury, frequently underestimating the true size of the damage.
- Computed Tomography (CT) Scans: This is the gold standard. A CT scan can detect a contusion immediately after trauma and precisely map its size and volume. For a deeper look at how doctors categorize these scans, see the Research on CT-based classification methods.
- Thoracic Ultrasound / E-FAST: Emergency doctors often use ultrasound at the bedside for rapid detection of fluid or lung collapse when a CT scanner is not immediately accessible.
Quantifying the bruised volume is highly predictive of how a patient will do. As highlighted in the Study on quantifying pulmonary contusion volume, if the contusion volume exceeds 20% of the total lung volume, the patient is at a significantly higher risk for prolonged mechanical ventilation and severe complications.
Acute Management and Ventilatory Strategies
Once diagnosed, treatment is tailored to the severity of the bruise:
- Oxygen Therapy: Mild cases are managed with supplemental oxygen via nasal cannula or high-flow nasal oxygen.
- Noninvasive Ventilation (CPAP/BiPAP): For patients who are struggling but still awake, noninvasive positive pressure ventilation helps keep the air sacs open.
- Lung-Protective Mechanical Ventilation: If a patient develops respiratory failure and must be intubated, doctors follow strict lung-protective guidelines. This involves using low tidal volumes (6 mL/kg of body weight) and keeping airway pressures low to avoid further tearing of the fragile lung tissue.
- Fluid Management: Doctors must maintain a delicate balance (euvolemia). Giving too much IV fluid will leak straight into the bruised lung, worsening the edema.
- Multimodal Pain Control: This is perhaps the most critical supportive step. If a patient is in severe pain from broken ribs, they will “splint” (take shallow breaths and avoid coughing). This causes the lungs to collapse and leads to pneumonia. Using epidural catheters, nerve blocks, and non-opioid pain medications allows the patient to breathe deeply and perform necessary “pulmonary toilet” (coughing up mucus).
These clinical standards are outlined in detail within the EAST Practice Management Guidelines.
Surgical Intervention and Advanced Therapies
While the lung bruise itself cannot be operated on, certain structural complications require surgical or advanced medical intervention:
- Surgical Stabilization of Rib Fractures (SSRF): If a patient has a “flail chest” (where a segment of the rib cage breaks and detaches from the rest of the chest wall), surgeons can use titanium plates and screws to rebuild the chest wall. Doing this within 24 to 72 hours of the injury dramatically reduces the time a patient has to spend on a ventilator.
- Venovenous Extracorporeal Membrane Oxygenation (VV-ECMO): In extreme cases where the lungs are too damaged to transfer oxygen even with a ventilator, VV-ECMO is used. This machine temporarily bypasses the lungs, drawing blood out of the body, oxygenating it, and pumping it back in, giving the lungs a chance to rest and heal.
Frequently Asked Questions About Lung Injuries
How long does it take for a bruised lung to heal?
For mild to moderate cases, a pulmonary contusion typically resolves within 5 to 7 days with good supportive care. However, severe contusions affecting more than 20% of the lung volume can require weeks of hospitalization, intensive respiratory therapy, and a much longer recovery timeline.
What are the long-term effects of a bruised lung?
While many patients recover completely, severe contusions can leave lasting marks. Long-term studies show that up to 58% of patients with severe contusions show signs of lung fibrosis (scarring) on CT scans years later. This can result in:
- Reduced lung compliance (stiffer lungs).
- Persistent dyspnea (shortness of breath during exercise).
- Chronic chest wall pain.
If you have recovered from a severe chest injury, follow-up spirometry (lung function testing) is highly recommended to monitor your breathing capacity.
When should you seek emergency medical attention after a chest injury?
You should go to the nearest emergency room immediately if you experience any of the following warning signs after a blow to the chest:
- Severe or worsening shortness of breath.
- Sharp chest pain, especially when breathing deeply or coughing.
- Coughing up blood.
- A bluish tint to your lips, gums, or fingertips.
- Dizziness, confusion, or feeling like you might pass out.
If you’ve been in an accident and need help navigating your medical recovery, diagnosing hidden injuries, and documenting your care, you can Schedule a recovery consultation with our team.
Conclusion
A pulmonary contusion is a serious, potentially life-threatening injury that demands immediate medical evaluation and careful monitoring. Because its symptoms are notoriously delayed, assuming you are fine right after a car crash can be a dangerous mistake.
I’m Dr. Adam Savage, and at CrashMD, we specialize in helping accident victims navigate the complex road to recovery. We serve patients across Arizona, Nevada, Texas, Oklahoma, and both Southern and Northern California. Our focus is on providing expert pain management, designing tailored recovery plans, and ensuring that all of your physical injuries are thoroughly documented for your medical and legal peace of mind.
Don’t let a hidden chest injury compromise your health or your future. To take control of your healing process, Learn more about accident recovery services today.