

Understanding Gastrointestinal Perforation and Its Causes
A gastrointestinal (GI) perforation is a full-thickness defect or rupture in the wall of the hollow organs in your digestive tract, including the stomach, small intestine, or colon. I’m Dr. Adam Savage, and understanding hollow viscus disruption is essential for recognizing when a sudden abdominal emergency demands immediate medical evaluation. Under normal physiological conditions, your digestive wall acts as an airtight, closed containment system, holding back harsh digestive acids, breakdown enzymes, and heavy bacterial burdens that reside within the gut lumen.
Recognizing the symptoms of perforated bowel is critical for timely intervention and can prevent serious complications.
Common symptoms of perforated bowel include severe abdominal pain, fever, and nausea, which should never be ignored.
When a full-thickness break occurs, those caustic contents leak directly into the sterile peritoneal cavity, causing severe bacterial contamination and rapid inflammatory damage. According to StatPearls research on bowel perforation etiology, underlying medical conditions like peptic ulcer disease account for a significant share of upper GI tears (with roughly 60% occurring in the duodenum and 40% in the stomach). In the lower GI tract, acute diverticulitis, inflammatory bowel disease (IBD) such as Crohn’s disease or ulcerative colitis, severe ischemic colitis, and advanced colorectal cancer are leading clinical culprits. In fact, diverticulosis affects roughly 10% of Americans over age 40 and 50% over age 60, with 10% to 25% of those individuals developing acute diverticulitis that can ultimately lead to intestinal rupture.
Iatrogenic procedural injuries also occur during invasive diagnostic or therapeutic medical procedures. For instance, screening or therapeutic colonoscopy procedures carry a small perforation risk (roughly 0.01% to 2%). To explore non-traumatic medical triggers and urgent risk factors in detail, read our Detailed Guide to Causes of Perforated Bowel Urgency.
Blunt Trauma and Motor Vehicle Accidents
At CrashMD, we frequently see intestinal perforations resulting from blunt physical trauma. During a high-impact motor vehicle accident, sudden decelerating forces press seat belts or the steering wheel forcefully against the vulnerable abdominal wall.
This violent impact creates a rapid, dramatic spike in intraluminal pressure inside a fluid- or air-filled segment of intestine, effectively popping a segment of the bowel wall like an overinflated balloon. Alternatively, the physical impact force can crush the flexible gut directly against the rigid lumbar spine or tear the delicate blood vessels in the mesentery. Mesenteric blood supply disruption starves the bowel tissue of oxygenated blood, leading to localized tissue necrosis, wall weakness, and delayed rupture days after the initial collision. A visible “seat belt sign”—bruising, redness, or linear abrasions across the lower torso—is a major clinical warning sign of underlying hollow viscus injury. If you have recently been in a collision, review our comprehensive guide on Beyond the Bump What to Expect for Car Crash Injury Recovery.
7 Key Symptoms of Perforated Bowel You Cannot Ignore

Recognizing the hallmark symptoms of perforated bowel quickly can save your life. The location of your pain often points directly to the site of the anatomical break: upper belly pain signals stomach or duodenal tears, while lower belly pain points to colon or small intestine damage.
- Sudden, Sharp Abdominal Pain: Often described as an explosive, tearing, or severe burning sensation that reaches maximum intensity almost instantly and worsens rapidly.
- Rigid, “Board-Like” Abdomen: Involuntary abdominal wall muscle spasms make the abdomen feel hard, flat, and completely unyielding to touch as the body attempts to splint the inflamed internal organs.
- Fever and Chills: Systemic inflammatory responses indicating that enteric bacteria and digestive toxins have entered the sterile peritoneal space.
- Persistent Nausea and Vomiting: Triggered by severe peritoneal irritation, reflex nervous system stimulation, and paralytic gut standstill.
- Abdominal Distension: Prominent swelling and bloating caused by built-up extraluminal gas, inflammatory fluids, and intestinal stagnation.
- Absence of Bowel Sounds: The intestines completely shut down their wave-like contractions (paralytic ileus), making the abdomen unnaturally silent during clinical auscultation.
- Systemic Sepsis Indicators: Marked tachycardia (rapid heartbeat), tachypnea (rapid breathing), cold sweats, dizziness, and dropping blood pressure.
| Symptom Feature | Ordinary Stomach Ache | Perforated Bowel |
|---|---|---|
| Pain Onset | Gradual, dull, or crampy | Sudden, explosive, sharp |
| Abdominal Wall | Soft, pressable | Rigid, hard, “board-like” |
| Movement Impact | Changing positions may help | Any movement or vibration causes agony |
| Systemic Sign | Rare fever or normal vitals | High fever, rapid heart rate, low blood pressure |
| Bowel Sounds | Active or hyperactive | Completely silent or absent |
Classic Early Symptoms of Perforated Bowel vs Normal Stomach Pain
Differentiating ordinary stomach pain from a true perforation comes down to intensity, quality, and progression. Normal stomach aches feel like dull cramps that wax and wane. In contrast, the symptoms of perforated bowel arrive abruptly with intense, relentless, and localized pain that escalates without relief.
A tricky clinical phenomenon is the temporary pain-free interval. Immediately after a perforation occurs, high pressure inside an inflamed bowel segment drops as contents spill out, providing temporary pain relief. However, as caustic digestive juices, bile, and intestinal bacteria spread across the sensitive peritoneal lining, intense pain returns along with continuous involuntary muscle guarding and extreme tenderness. Learn more about measuring pain severity in The Scale of Pain Decoding Injury Severity Assessment Methods.
Advanced Symptoms of Perforated Bowel: Peritonitis and Sepsis
As leaked gastrointestinal contents spread throughout the abdominal cavity, localized inflammation rapidly turns into generalized peritonitis. Free air and caustic chemical fluid accumulating under the diaphragm irritate subdiaphragmatic phrenic nerve endings (originating from C3-C5 spinal roots), which frequently causes referred pain in the tip of the shoulder.
Without immediate surgical and medical treatment, peritonitis leads to sepsis—a life-threatening full-body immune response that damages vital organ systems. Patients rapidly develop high fevers, shallow breathing, severe hypotension (low blood pressure), altered mental state, and septic shock. Review Sepsis Alliance insights on perforated bowel complications to understand how rapidly this infection progresses and why immediate emergency department evaluation is imperative.
Critical Mistakes to Avoid When Experiencing Bowel Perforation

When dealing with a potential bowel rupture, subtle mistakes in decision-making can lead to severe, life-threatening complications. Here is what you should never do if you suspect a gastrointestinal perforation:
- Waiting for the Pain to Pass: Assuming severe abdominal pain will fade on its own allows bacteria and digestive enzymes to spread further through your abdominal cavity and bloodstream, dramatically raising infection risks.
- Taking NSAIDs or Painkillers: Anti-inflammatory drugs like ibuprofen, naproxen, or aspirin mask early peritonitis signs, worsen digestive tract ulcers, impair platelet aggregation, and increase internal bleeding risks.
- Ignoring Seat Belt Bruising: Dismissing torso bruising or abdominal tenderness after a car crash can delay the diagnosis of a tearing gut or ischemic bowel injury, converting a repairable tear into an extensive infection.
- Self-Medicating with Laxatives or Antacids: Pushing laxatives through an obstructed or torn gut forces even more bacteria and fecal material into your sterile peritoneal cavity, while antacids alter stomach acid defenses.
- Delaying Emergency Care: Delaying surgical evaluation past the critical 24-hour mark significantly increases mortality rates, postoperative complications, and the likelihood of needing an emergency ostomy.
How Gastrointestinal Perforation Is Diagnosed and Treated
When you arrive at the emergency room, doctors use rapid clinical protocols and diagnostic tests to check for free extraluminal air and fluid accumulation within the abdomen:
- Upright Chest Radiographs: An upright X-ray reveals free intraperitoneal air beneath the diaphragm (pneumoperitoneum) in approximately 50% to 70% of acute perforation cases.
- CT Scan with IV Contrast: Considered the gold standard diagnostic tool, high-resolution computed tomography (CT) imaging accurately identifies minute amounts of extraluminal air, localized fluid collections, and pinpoint perforation locations.
- Blood Work: Laboratory evaluation checks for high white blood cell counts (leukocytosis with a left shift) and elevated serum lactate levels, which indicate severe tissue stress, ischemia, and systemic infection.
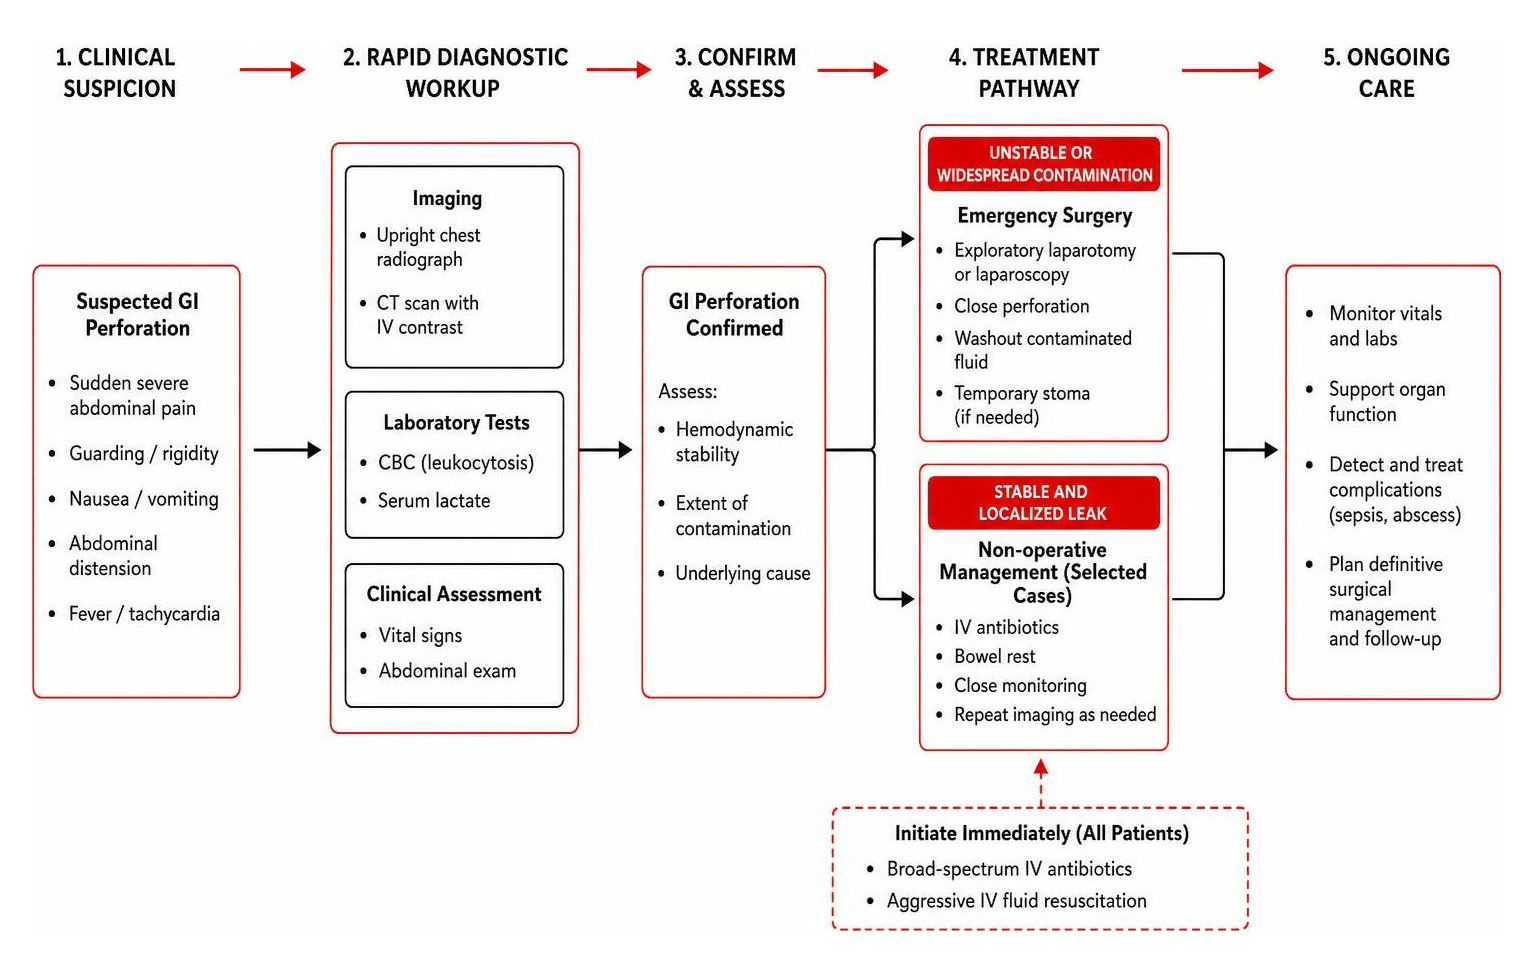
Treatment strategies depend on the size of the break and how widespread the contamination is. Free, uncontained perforations require emergency exploratory laparotomy or minimally invasive laparoscopic surgery to repair the tear, perform extensive peritoneal lavage to flush out contaminated fluids, and prevent overwhelming sepsis. In cases of extensive tissue damage or heavy contamination, surgeons may create a temporary stoma (colostomy or ileostomy) to divert stool and allow the underlying bowel time to heal safely.
Broad-spectrum intravenous (IV) antibiotics and aggressive IV fluid resuscitation start immediately upon arrival at the hospital. For a clinical review on modern treatment protocols, read the Cleveland Clinic clinical overview of gastrointestinal perforation.
Frequently Asked Questions about Perforated Bowel
Can a perforated bowel heal on its own without surgery?
In limited and carefully selected cases, small or “contained” micro-perforations can heal without open surgery. If CT imaging shows that surrounding structures like the omentum have successfully walled off the leak, stable patients without signs of peritonitis may be treated conservatively with IV broad-spectrum antibiotics, strict bowel rest (NPO status), intravenous fluids, and close hospital monitoring. Interventional radiologists may also perform CT-guided percutaneous drainage to clear localized fluid collections or abscesses larger than 3 cm.
How quickly do symptoms of a perforated bowel develop?
Symptoms usually appear abruptly within minutes to hours of a full-thickness rupture. However, after blunt abdominal trauma like a car crash or steering wheel impact, symptoms can develop gradually over 24 to 72 hours if intestinal tissue ischemic death occurs slowly before the bowel wall finally opens.
What is the recovery time and outlook after bowel perforation surgery?
Hospital stays typically range from one to two weeks, depending on infection severity, whether emergency open surgery was performed, and whether a temporary stoma was created. Transitioning back to solid foods occurs slowly under medical supervision. Full physical recovery and return to normal activity take anywhere from six weeks to several months.
Conclusion
A perforated bowel is a critical medical emergency requiring immediate diagnostic evaluation and surgical intervention. Recognizing the early symptoms of perforated bowel—and avoiding dangerous delays in emergency care—is essential for preserving health and ensuring a safe recovery.
At CrashMD, we specialize in guiding accident victims through complex post-accident medical care, connecting patients with specialized medical providers, and ensuring all physical injuries are meticulously documented for legal claims. If you are recovering from a motor vehicle collision or traumatic injury, explore our Car accident intestinal perforation recovery guide and learn How to Get Medical Records for Your Injury Claim Fast. Contact CrashMD today so we can support your complete medical and financial recovery.