

What Is the ICD-10 Code for Pulmonary Contusion?
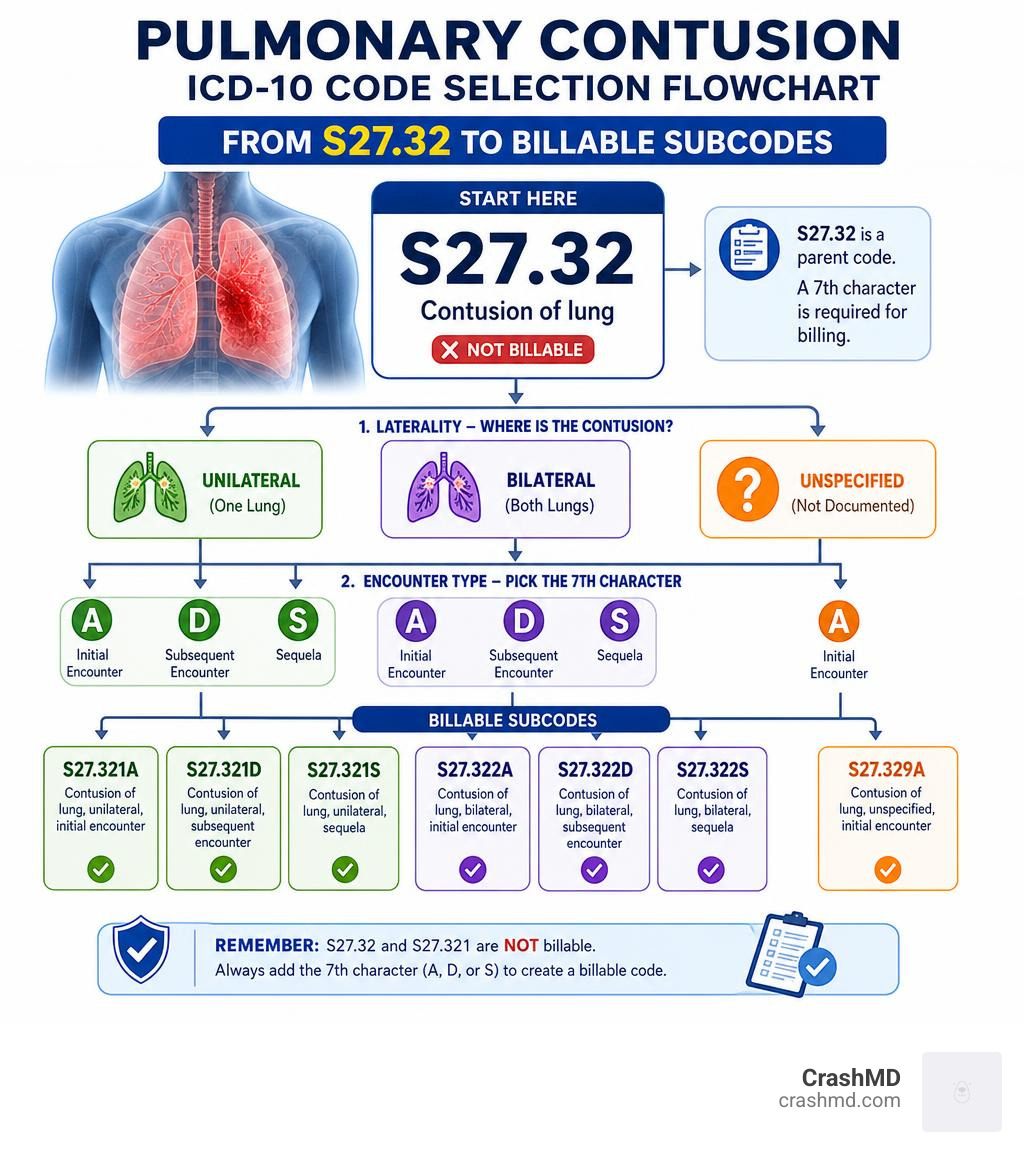
The ICD-10 code for pulmonary contusion falls under the S27.32 category. Here’s a quick reference to the most commonly used billable codes:
| Code | Description | Billable? |
|---|---|---|
| S27.321A | Contusion of lung, unilateral, initial encounter | Yes |
| S27.321D | Contusion of lung, unilateral, subsequent encounter | Yes |
| S27.321S | Contusion of lung, unilateral, sequela | Yes |
| S27.322A | Contusion of lung, bilateral, initial encounter | Yes |
| S27.322D | Contusion of lung, bilateral, subsequent encounter | Yes |
| S27.322S | Contusion of lung, bilateral, sequela | Yes |
| S27.329A | Contusion of lung, unspecified, initial encounter | Yes |
Note: S27.32 and S27.321 on their own are not billable. You must add a 7th character (A, D, or S) to generate a reimbursable claim.
If you were in a car accident or suffered blunt chest trauma, your medical records may include one of these codes. Getting it right matters — not just for your medical care, but for your insurance claim and any legal case that follows.
Pulmonary contusion is a bruise of the lung tissue caused by blunt force trauma. It’s one of the most common serious chest injuries seen after car accidents, falls, and high-impact collisions. Because it doesn’t always show up on an X-ray right away, it can be underdiagnosed and undercoded — which can hurt your claim.
Choosing the wrong code, or leaving the documentation vague, creates real risks: denied claims, audit flags, and gaps in your medical record that insurers and defense attorneys can exploit.
This guide breaks down every code in the S27.32 family, explains what documentation is required to support each one, and helps you understand what your medical team should be capturing from day one.
Understanding the ICD-10 Code for Pulmonary Contusion
When a patient experiences significant trauma to the chest wall, the underlying lung tissue can absorb the impact, leading to bleeding and fluid accumulation. In medical coding, we look to the World Health Organization’s ICD-10-CM classification system to translate this injury into a standardized format.
Under the ICD-10 system, the category ICD-10 Code for Contusion of lung- S27.32- Codify by AAPC is the starting point for all pulmonary contusion diagnoses. However, S27.32 is a parent code and cannot be used directly on a billing claim. To submit a valid medical claim in 2026, coders must specify the lateral location of the bruise and the type of clinical encounter.

Unilateral vs. Bilateral: Selecting the Right ICD-10 Code for Pulmonary Contusion
The ICD-10 system places a heavy emphasis on laterality. If a patient has a bruise on only one lung, the medical team must use the unilateral code family. If both lungs are bruised, the bilateral codes are required.
- Unilateral Pulmonary Contusion (S27.321): This code is utilized when clinical imaging, such as a CT scan or chest X-ray, confirms that the injury is restricted to either the left or the right lung. To explore the full hierarchical breakdown of this category, you can refer to 2026 ICD-10-CM Diagnosis Code S27.32: Contusion of lung.
- Bilateral Pulmonary Contusion (S27.322): When high-velocity impacts (like steering wheel injuries in motor vehicle accidents) cause bruising to both lungs, the bilateral code is appropriate. For example, ICD-10 code S27.322A for Contusion of lung, bilateral, initial … – AAPC represents a bilateral lung contusion documented during the patient’s initial phase of acute trauma care.
Using the bilateral code when both lungs are injured is critical. It reflects a much higher clinical severity, which directly influences medical decision-making, hospital resource allocation, and reimbursement rates.
Coding Unspecified Cases with the ICD-10 Code for Pulmonary Contusion
Sometimes, emergency department records are finalized before a detailed imaging report is fully integrated, or the provider simply documents “pulmonary contusion” without noting which side is affected. In these scenarios, the unspecified code S27.329 (such as S27.329A for the initial encounter) is the only option.
However, relying on unspecified codes carries substantial billing and audit risks. Insurance providers frequently flag or deny claims with unspecified laterality, arguing that the medical record lacks the clinical specificity required to justify the necessity of inpatient stays or intensive respiratory therapies. For a clean billing process, clinicians must document the specific side of the injury as soon as imaging results are available.
Clinical Validation and Documentation Requirements for Lung Contusions
To withstand insurance audits and support legal claims after an accident, a diagnosis of pulmonary contusion must be backed by strong clinical evidence. Simply writing “lung contusion” in the progress notes is not enough.
According to ICD-10 Coding for Pulmonary Contusion ( S27.32XA, S27.322A ), the primary clinical validation requirements include:
- Mechanism of Injury: The clinical notes must detail the trauma event (e.g., motor vehicle collision, airbag deployment, or a fall from a height) to establish a traumatic origin.
- Diagnostic Imaging: While a chest X-ray can sometimes show “patchy infiltrates,” a CT scan is the gold standard for confirming a pulmonary contusion and establishing laterality.
- Physiological Indicators: Documentation should include oxygen saturation levels, arterial blood gas (ABG) results (such as a low $PaO_2$), and clinical signs like shortness of breath, chest wall bruising, or hemoptysis.
| Documentation Element | Unilateral Contusion (S27.321) | Bilateral Contusion (S27.322) |
|---|---|---|
| Imaging Proof | CT/X-ray showing localized infiltrates in one lung | CT/X-ray showing bilateral infiltrates |
| Trauma Documentation | Required (e.g., localized seatbelt sign) | Required (e.g., steering wheel impact) |
| Clinical Severity | Typically managed with close monitoring | Often requires intensive care, ABG monitoring, or mechanical ventilation |
Coding Subsequent Encounters, Sequela, and Related Thoracic Injuries
The final digit of the icd-10 code for pulmonary contusion is the 7th character, which tells the story of where the patient is in their recovery journey.
- A – Initial Encounter: Used while the patient is receiving active, acute treatment for the contusion (e.g., emergency department evaluation, acute hospital stay).
- D – Subsequent Encounter: Used for visits after the active phase of treatment has ended, during routine recovery and healing (e.g., follow-up outpatient imaging or pulmonary rehab).
- S – Sequela: Used for complications or chronic conditions that arise as a direct result of the original injury. For instance, if a patient develops chronic pleural scarring or restricted lung capacity months after the accident, the unilateral code is written as 2026 ICD-10-CM Diagnosis Code S27.321S: Contusion of lung, unilateral, sequela.

Differential Diagnoses and Associated Thoracic Codes
When coding for thoracic trauma, it is rare for a pulmonary contusion to exist in isolation. Providers and coders must distinguish between a lung bruise and other nearby injuries to avoid double-billing or mischaracterizing the trauma.
- Contusion of the Thorax (S20.2): This code refers to a superficial bruise of the chest wall, ribs, or breastbone, without damage to the internal organs. If the patient has both a bruised chest wall and a bruised lung, both ICD-10-CM Diagnosis Code S20.2 – Contusion of thorax and the S27.32 code should be documented.
- Contusion of the Bronchus (S27.422A): A bruise affecting the main bronchial airways. If the bronchi are injured alongside the lung tissue, you may see codes like 2026 ICD-10-CM Diagnosis Code S27.422A: Contusion of bronchus, bilateral, initial encounter added to the claim.
- Acute Respiratory Distress Syndrome (ARDS) (J80): A common, severe complication of bilateral lung contusions. When ARDS develops, J80 is coded as a secondary diagnosis, which significantly impacts the patient’s MS-DRG weight.
- Postprocedural Pneumothorax (J95.811): If a patient requires a chest tube or mechanical ventilation and develops a collapsed lung as an iatrogenic complication, this code is added to document the event.
Frequently Asked Questions About Pulmonary Contusion Coding
Is S27.321 a billable ICD-10 code?
No, S27.321 is not a billable code on its own. It is a subcategory code that requires a 7th character to indicate the encounter type. To submit a valid claim for a unilateral lung contusion, you must use a complete code such as S27.321A (initial encounter), S27.321D (subsequent encounter), or S27.321S (sequela).
What is the difference between a myocardial contusion and a pulmonary contusion code?
While both are serious chest injuries resulting from blunt trauma, they represent entirely different organ systems. A pulmonary contusion (S27.32) involves bruising of the lung tissue. A myocardial contusion involves bruising of the heart muscle and is coded under the cardiovascular trauma categories (such as S26.0 for injury of the heart with hemopericardium).
How does ARDS affect pulmonary contusion coding?
If a patient with a severe lung contusion develops Acute Respiratory Distress Syndrome (ARDS), the coder must assign code J80 as an additional diagnosis. According to the ICD-10-CM/PCS MS-DRG v34.0 Definitions Manual, adding J80 can classify the inpatient stay into a higher-tier MS-DRG (such as MS-DRG 205 for respiratory diagnoses with a Major Complication or Comorbidity), reflecting the intensive care and resources needed to manage the patient.
Conclusion
Accurate medical coding is about more than just paperwork—it is a vital part of your physical and financial recovery after an accident. Missing details, vague documentation, or incorrect codes can lead to denied claims and weak legal cases.
At CrashMD, we guide accident victims through every step of their recovery journey across Arizona, Nevada, Texas, Oklahoma, and California. We specialize in post-accident medical care, expert pain management, and thorough clinical documentation. Our team ensures that every injury, from a bruised rib to a complex bilateral pulmonary contusion, is clearly documented to protect both your health and your legal rights.
I’m Dr. Adam Savage, and our team ensures your injuries are fully documented for your recovery and legal protection.
If you or a loved one has recently experienced a chest injury or been in an accident, do not leave your recovery to chance. Schedule an appointment with CrashMD today, or Learn more about CrashMD and how we advocate for your complete physical and financial healing.