

Why a Headache Following Concussion Needs Prompt Attention
A headache following concussion is common, but it should not be ignored – especially after a car accident. It may be a post-traumatic headache (PTH), which often starts right away or within the first few days after a head injury. Most improve over several weeks, but some last longer and need focused care.
Get urgent medical help now if the headache is worsening or severe, or if it comes with repeated vomiting, weakness, numbness, confusion, fainting, seizure, trouble speaking, or vision changes.
Headaches after a concussion can feel like migraine, with throbbing pain, nausea, and sensitivity to light or sound. They can also feel like pressure or tightness, often linked to neck strain or whiplash. Screens, bright lights, poor sleep, stress, and mental effort can make symptoms worse.
Headache is one of the most common concussion symptoms. Research suggests that nearly all people with concussion experience one, and many have migraine-like features. The good news: identifying the pattern, treating neck and sleep issues, pacing activity, and avoiding overuse of pain medicine can help support recovery.
I’m Dr. Adam Savage, and this guide will explain what may be causing your headache and what practical next steps can help.

Headache following concussion word guide:
Understanding Headache Following Concussion: Definitions and Clinical Phenotypes
Globally, roughly 69 million people sustain a traumatic brain injury (TBI) each year, with mild TBI (mTBI) or concussion representing the vast majority of cases. Up to 95% of individuals experience head pain acutely after injury.
Clinically, this condition is designated as Post-Traumatic Headache (PTH). Under the ICHD-3 diagnostic criteria, PTH is classified as a secondary headache disorder that develops within 7 days of the head trauma, regaining consciousness, or recovering the ability to report symptoms.
PTH is divided by symptom duration:
- Acute Post-Traumatic Headache: Resolves within 3 months of onset.
- Persistent (Chronic) Post-Traumatic Headache: Continues beyond the 3-month chronicity threshold.
Between 49% and 58% of patients continue experiencing headaches 12 months post-injury, and roughly 35% report persistent symptoms five years later. Post-concussion headaches do not fit a single rigid profile; instead, they present as distinct clinical phenotypes.
| Headache Phenotype | Dominant Pain Characteristics | Common Accompanying Symptoms | Primary Clinical Triggers |
|---|---|---|---|
| Migraine-Like | Throbbing, pulsating, unilateral or bilateral, moderate-to-severe | Nausea, vomiting, photophobia, phonophobia, visual aura | Bright lights, screen use, cognitive strain, stress |
| Tension-Type | Dull ache, band-like pressure, squeezing across forehead/temples | Muscle tightness in shoulders, mild fatigue, scalp tenderness | Mental fatigue, sustained posture, physical exhaustion |
| Cervicogenic | Unilateral dull or aching pain radiating from neck/base of skull | Reduced cervical range of motion, upper neck tenderness | Neck movements, poor ergonomics, prolonged sitting |
| Occipital Neuralgia | Sharp, shooting, jabbing, or burning pain in occipital nerve path | Scalp hypersensitivity, tenderness over greater occipital nerve | Palpation of suboccipital region, head rotation |
Identifying Migraine-Like Headache Following Concussion
Migraine-like features dominate post-concussion clinical presentations. Phenotype research on post-traumatic headache indicates that approximately 88% of patients with moderate-to-severe acute-to-subacute PTH exhibit a migraine-like or probable migraine-like profile.
Patients describe pulsating or throbbing pain aggravated by routine physical activity. It frequently occurs alongside photophobia (light sensitivity), phonophobia (sound sensitivity), nausea, light-headedness, and occasionally visual aura. When managing persistent symptoms, learning everything you need to know about headache post-trauma helps distinguish migraine-like episodes from other post-concussive symptoms.
Tension-Type, Cervicogenic, and Neuralgic Headaches
Tension-type headaches present as constant, tight, band-like pressure around the temples or forehead. While they can occur independently, they frequently stem from musculoskeletal trauma sustained during the original impact.
Biomechanically, a concussion is rarely isolated to the brain; the force required to concuss neural tissue often causes whiplash and cervical spine strain. This activates the trigeminocervical complex, where sensory nerve fibers from the upper cervical roots (C1–C3) converge with trigeminal sensory pathways in the brainstem. As a result, structural neck injury refers pain directly into the head. Understanding beyond the impact: what headaches after a car crash tell you allows clinicians to pinpoint whether head pain is driven by intracerebral metabolic distress, cervical dysfunction, or occipital neuralgia.
Underlying Pathophysiology and Key Risk Factors
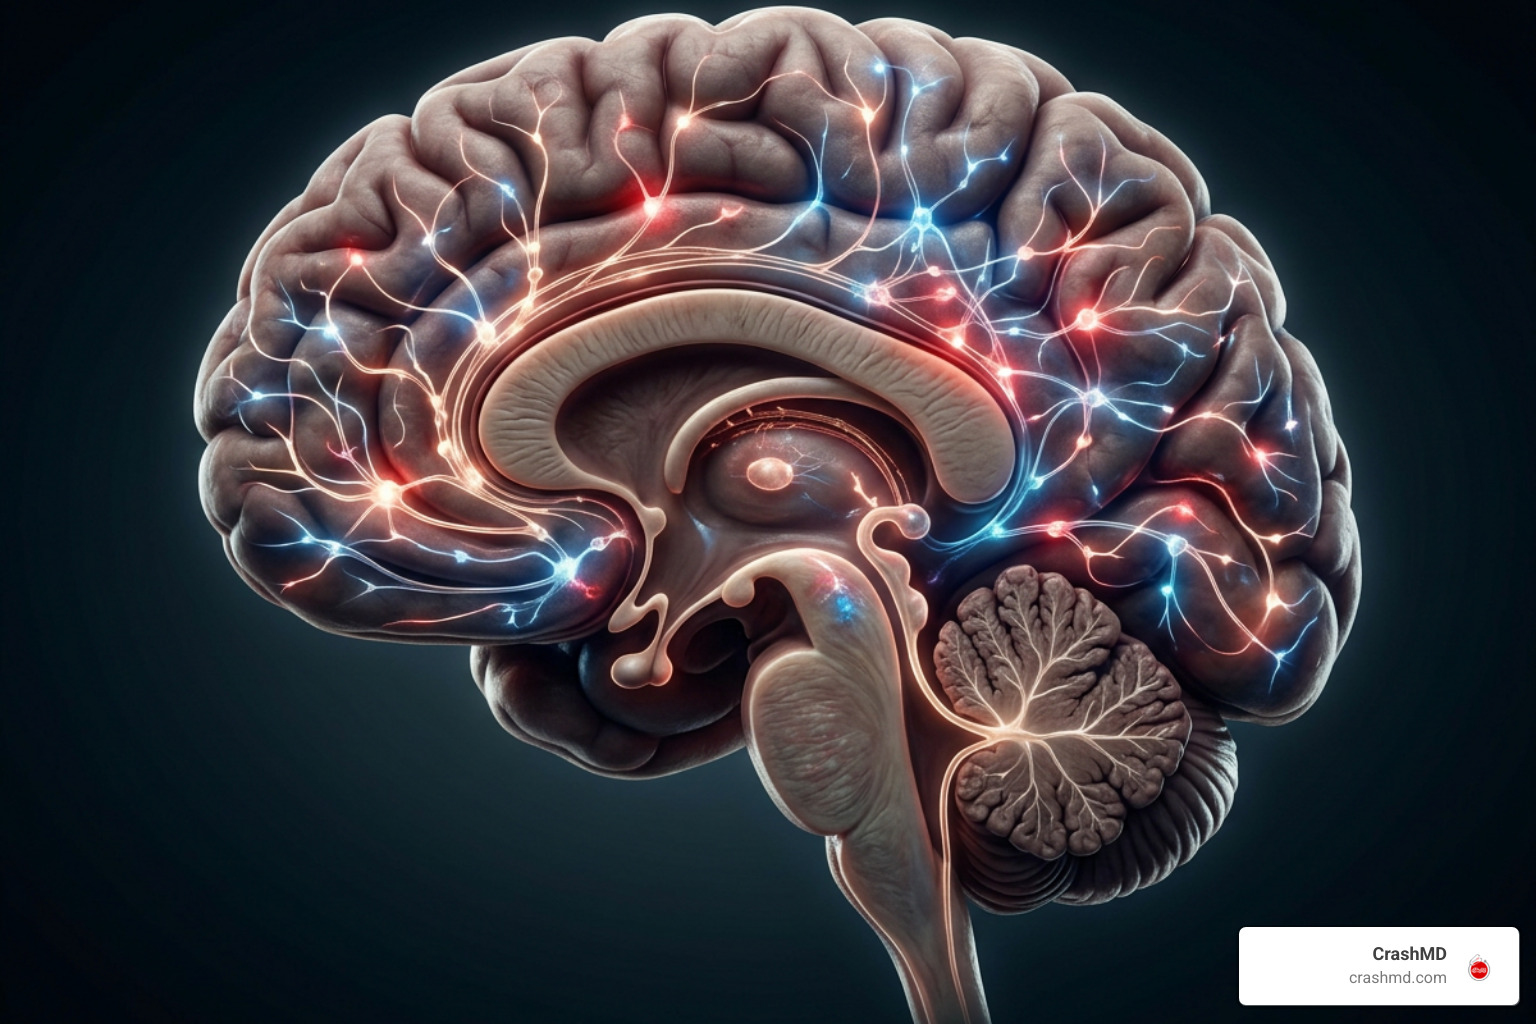
A concussion triggers a complex neurometabolic cascade. Mechanical trauma stretches and shears axonal membranes, provoking an indiscriminate release of excitatory neurotransmitters (such as glutamate), massive cellular potassium efflux, and an influx of calcium. This induces a state of cellular hypermetabolism followed by metabolic energy crisis, localized neuroinflammation, and impaired cerebral blood flow regulation.

Cortical spreading depression—a wave of sustained neuronal depolarization across the cerebral cortex—activates the trigeminovascular system. This process triggers the release of vasoactive neuropeptides, particularly Calcitonin Gene-Related Peptide (CGRP). According to a clinical review on post-traumatic headache pathophysiology, patients with persistent post-traumatic headache demonstrate heightened sensitivity to CGRP pathways, matching the neuroinflammatory mechanisms observed in primary migraine. Examining the ultimate guide to long-term risks of concussions highlights how these metabolic and descending pain pathway disruptions can persist long past the initial accident.
Biological and Demographic Risk Factors for Prolonged Recovery
Certain clinical and demographic variables increase the likelihood of developing persistent PTH:
- Sex: Women are diagnosed with persistent post-concussive headaches more frequently than men, influenced by hormonal modulations and differential healthcare utilization.
- Prior Headache History: A personal or family history of migraines elevates vulnerability to prolonged headache chronification.
- Age Profile: Adolescents and young adults (ages 15–30) experience higher rates of prolonged recovery compared to younger children.
- Initial Symptom Burden: Severe acute pain, immediate post-injury nausea, or elevated initial concussion assessment scores strongly correlate with extended recovery timelines.
- Psychological Factors: Pre-existing or comorbid post-traumatic stress disorder (PTSD), anxiety, and depression can amplify pain perception and slow neurometabolic normalization.
- Mechanism of Trauma: Blast-related trauma and high-impact motor vehicle collisions produce elevated rates of chronic, refractory headaches compared to low-velocity impacts.
Diagnostic Evaluation, Neuroimaging, and Red Flags
Evaluating post-traumatic headache requires a comprehensive clinical assessment. Standardized tools like the Sport Concussion Assessment Tool (SCAT) symptom inventory evaluate symptom burden, sleep disruption, and cognitive function.
A prospective investigation in the Toronto Concussion Study on acute headache onset revealed that 94% of patients develop acute headache within 24 to 48 hours of trauma, with 57% reporting immediate onset. Crucially, researchers found no correlation between the physical impact location on the skull and the anatomical location of the headache pain. Reviewing the first look: how doctors assess traumatic brain injuries illustrates why relying solely on impact site examination is insufficient for diagnosing functional intracranial and cervical strain.
Recognizing Clinical Red Flags and Structural Complications
Routine neuroimaging (standard non-contrast CT or structural brain MRI) is generally normal in uncomplicated concussion. However, clinicians must maintain vigilance for red-flag symptoms requiring emergency neuroimaging:

- Progressively Worsening Headache: A headache escalating steadily in intensity over hours or days, which may indicate an expanding subdural or epidural hematoma.
- Focal Neurological Deficits: Unilateral weakness, numbness, facial droop, unequal pupil sizes, or ataxia.
- Positional Headaches: Pain that worsens dramatically when upright and resolves when lying flat, suggesting a traumatic cerebrospinal fluid (CSF) leak and intracranial hypotension.
- Systemic or Cognitive Deterioration: Repeated projectile vomiting, acute confusion, slurred speech, lethargy, or new-onset seizures.
Comprehensive Treatment and Management Strategies
Managing post-traumatic headaches effectively involves matching therapies to the patient’s specific headache phenotype. While acute pain relief is necessary, relying on non-targeted over-the-counter pills can lead to long-term issues.
As outlined in the StatPearls guide to posttraumatic headache management, pharmacotherapy is divided into abortive (acute) and preventive strategies:
- Acute/Abortive Interventions: For migraine-like presentations, triptans (such as sumatriptan or rizatriptan) or oral CGRP receptor antagonists (gepants) should be introduced early rather than relying entirely on simple analgesics. Short, scheduled 48-to-72-hour courses of NSAIDs combined with acetaminophen can be used during the immediate post-injury window.
- Preventive Medications: Indicated when headaches occur frequently (e.g., more than 8–10 days per month) or cause severe functional disability. Options include tricyclic antidepressants (amitriptyline, nortriptyline), topiramate, beta-blockers (propranolol), or injectable CGRP monoclonal antibodies.
- Interventional Procedures: Greater occipital nerve blocks, trigger point injections, and ultrasound-guided peripheral nerve blocks provide rapid, targeted relief for cervicogenic and occipital neuralgia phenotypes. Insights from headache after crash: specialists share their advice emphasize the value of deploying interventional options early to prevent chronic pain pathways from stabilizing.
Managing Medication Overuse Headache Risks
A major pitfall in post-concussion care is Medication Overuse Headache (MOH), or rebound headache. Studies show that approximately 27% of adult PTH patients and up to 70% of persistent pediatric cases meet criteria for MOH.
Taking simple analgesics (acetaminophen, NSAIDs) 15 or more days per month, or triptans, opioids, and combination analgesics 10 or more days per month, alters central pain pathways and creates daily rebound headaches. Overcoming MOH requires tapering overused acute medications, establishing a strict limit of using abortive therapies no more than two days per week, and introducing structured preventive treatments.
Non-Pharmacological and Active Rehabilitation Therapies
Current clinical protocols avoid prolonged dark-room rest. Instead, active multidisciplinary rehabilitation yields faster functional recovery:
- Sub-Symptom Aerobic Exercise: Gentle, controlled cardiovascular activity (e.g., stationary cycling) below the symptom-exacerbation threshold improves cerebral autoregulation and speeds recovery.
- Cervical Spine Physical Therapy: Targeted manual therapy, deep neck flexor strengthening, and postural correction address cervicogenic pain generators.
- Vestibular and Oculomotor Therapy: Specialized exercises alleviate headaches triggered by visual tracking, screen use, or motion sensitivity.
- Cognitive Behavioral Therapy (CBT) and Biofeedback: Psychological interventions improve stress resilience, normalize sleep architecture, and modulate descending pain pathways.
Prognosis, Special Populations, and Recovery Timelines
Most individuals recovering from a sports-related or minor concussion see substantial symptom improvement within 2 to 4 weeks under a structured Progressive Return to Activity protocol. However, between 15% and 20% of patients experience persistent symptoms lasting beyond one year. Detailed tracking in our step-by-step guide to how long headaches last after concussion shows that recovery timelines depend heavily on early active rehabilitation, targeted phenotyping, and managing sleep patterns.
Pediatric and Adolescent Headache Following Concussion
In pediatric and adolescent populations, post-traumatic headache prevalence ranges between 43% and 60%, with roughly 8% developing persistent headaches at 3 months. Adolescents are particularly susceptible to prolonged recovery due to ongoing neurodevelopment, academic demands, and social stressors.
According to the American Headache Society white paper on youth PTH, care for young patients should prioritize non-pharmacological pacing, aggressive screening for medication overuse, and formal academic accommodations (such as reduced screen time, built-in rest periods, and staggered testing schedules). Families can consult our guide on concussion care: finding the right program for your healing journey to navigate specialized youth and adult recovery pathways.
Frequently Asked Questions about Post-Concussion Headaches
How long does a headache usually last after a concussion?
Most acute post-concussion headaches resolve within 2 to 3 weeks with adequate pacing and sub-symptom activity. If head pain persists past 3 months, it is clinically classified as persistent post-traumatic headache and warrants formal evaluation by a headache specialist or brain injury physiatrist. Consult our post-concussive symptoms 101: recovery timeline guide for detailed phase-by-phase recovery expectations.
Why does thinking or screen time worsen post-concussion headaches?
Mental effort and screen use place high demands on injured neural networks that are operating through a metabolic energy crisis. High-contrast light, screen flicker, and intense concentration trigger photophobia and strain visual-vestibular pathways, rapidly provoking headache flares. Structured cognitive pacing (taking a 5-minute break every 20 minutes) helps manage this strain.
When does a post-concussion headache require emergency care?
Seek emergency medical evaluation if you develop sudden and escalating headache severity, repeated vomiting, unequal pupil sizes, clear fluid draining from the nose or ears, confusion, slurred speech, balance loss, or limb numbness. These warning signs may indicate structural complications such as intracranial hemorrhage or CSF leaks.
Conclusion
Recovering from a post-traumatic headache requires an accurate diagnosis, identifying your specific headache phenotype, and following an active rehabilitation plan. Relying solely on passive rest and daily over-the-counter pain relievers can slow recovery and lead to rebound headaches.
At CrashMD, we guide accident victims through recovery across Arizona, Nevada, Texas, Oklahoma, and California. We provide expert medical care, specialized pain management, and thorough clinical documentation of your injuries to support you through medical rehabilitation and any related legal claims. If head pain is interfering with your daily life, explore our specialized treatment for post-traumatic headache to start your path toward lasting relief.