

Why Post-Trauma Headache Is One of the Most Overlooked Injuries After a Crash
Post-trauma headache is the most common physical complaint following a traumatic brain injury (TBI) — affecting anywhere from 30% to 90% of patients after a head or neck injury.
If you’re trying to understand what’s happening after your accident, here’s the short answer:
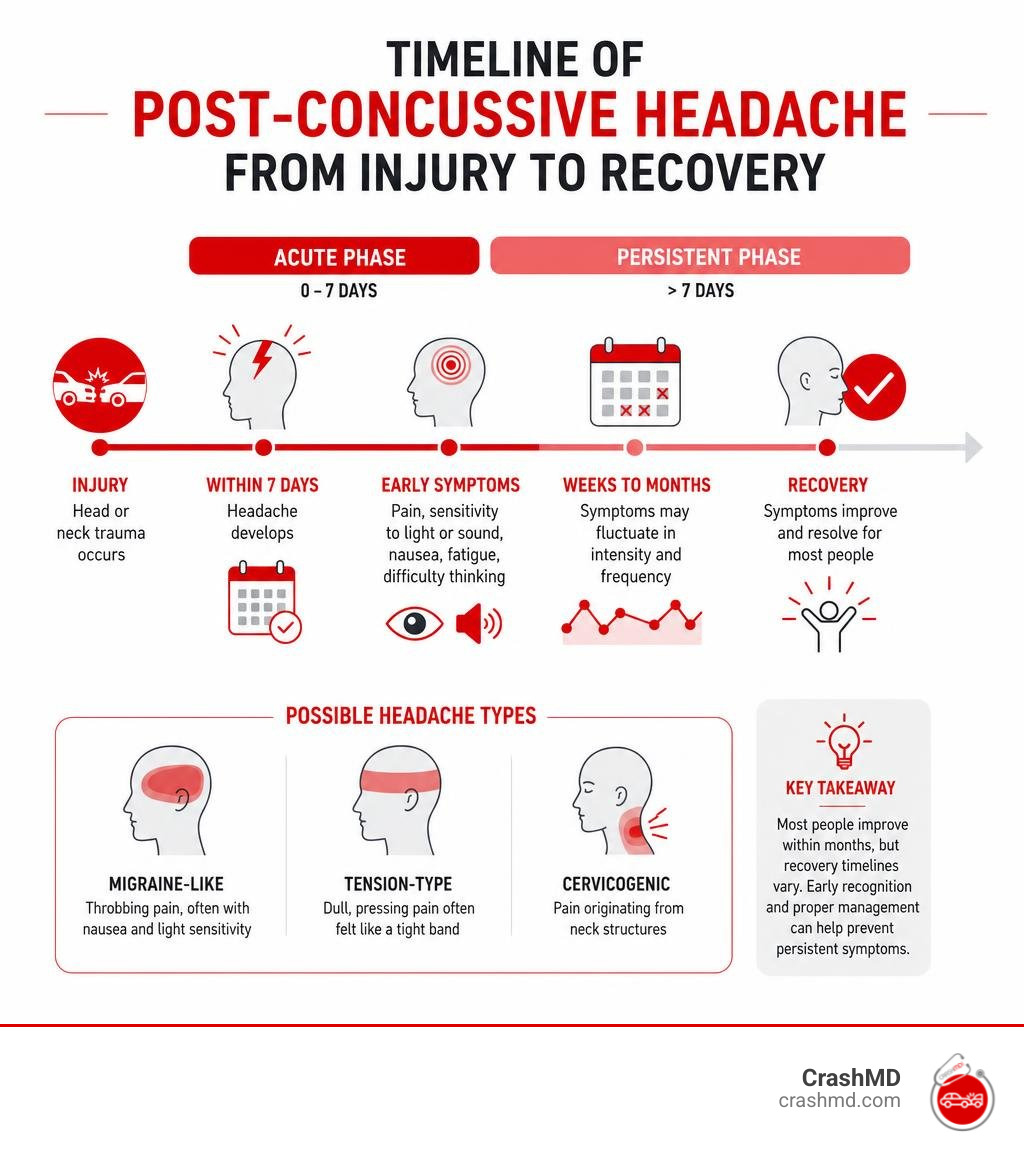
- What it is: A headache that develops within 7 days of a head or neck injury
- How common: Up to 90% of concussion patients experience it
- How long it lasts: Resolves within 3 months for most people, but 18–22% still have it after 1 year
- Main types: Migraine-like, tension-type, or cervicogenic (neck-related)
- Key risk factors: Female sex, prior headache history, and psychiatric conditions like anxiety or PTSD
- Treatment: Tailored to your specific headache type — there is no one-size-fits-all fix
Headaches after a crash can feel invisible to others but completely derail your life. They can stop you from working, sleeping, and thinking clearly. And yet they’re frequently undertreated or misunderstood.
What makes this condition especially tricky is that it doesn’t look the same in every patient. One person’s post-trauma headache feels like a tight band around the skull. Another person’s feels like a full migraine with light sensitivity and nausea. The same injury, very different experiences.
I’m Dr. Adam Savage, and I’ve seen this pattern repeatedly in patients recovering from car accidents. The headache often isn’t taken seriously until it becomes persistent — and by then, it’s much harder to treat.
The good news: when it’s identified early and managed correctly, most patients do improve. This guide will walk you through everything you need to know — from diagnosis and causes to treatments that actually work.
Understanding Post-Trauma Headache: Definition and ICHD-3 Criteria
To get the right treatment, we first have to speak the same language as the medical community. The International Classification of Headache Disorders (ICHD-3) provides the gold standard for classifying these injuries.
According to the ICHD-3 classification and diagnostic criteria, a post-trauma headache (or post-traumatic headache) is classified as a secondary headache. This means the pain is not its own independent condition; instead, it is a direct symptom of another event—specifically, trauma or injury to the head and/or neck.
To meet the official diagnostic criteria, the headache must follow the 7-day onset rule. This means the pain must develop within 7 days of:
- The initial head or neck trauma,
- Regaining consciousness, or
- Recovering the ability to sense and report pain.
The medical community also uses a 3-month persistence threshold to categorize the severity and timeline of your recovery:
- Acute Post-Trauma Headache: Resolves completely within 3 months of the injury.
- Persistent Post-Trauma Headache: Continues for more than 3 months.
While the 7-day rule is standard for formal diagnosis, we know from clinical experience that some patients report delayed symptoms that seem to surface weeks later. If you are navigating these timelines after a collision, reading our Detailed Guide to Head Pain After Car Accident can help you understand how delayed symptoms are evaluated.
Phenotypes and Clinical Subtypes of Injury-Induced Head Pain
One of the most fascinating (and frustrating) aspects of a post-trauma headache is that it lacks a single, unique physical signature. It is a master of disguise. Instead of presenting as a brand-new type of pain, it mimics primary headache disorders.
Because of this, we treat these headaches based on their “phenotype”—meaning we look at the specific symptoms they mimic to guide our treatment. Many patients suffer from a clinical overlap, experiencing more than one type of headache at the same time. Furthermore, overusing quick-fix pain relievers can lead to medication-overuse headaches, adding another layer of complexity.
| Feature | Migraine-Like | Tension-Type | Cervicogenic |
|---|---|---|---|
| Pain Character | Pulsating, throbbing, moderate-to-severe | Dull, aching, constant, mild-to-moderate | Dull ache, can be sharp with neck movement |
| Location | Typically one-sided (unilateral) | Both sides, “band-like” around the head | Starts in the neck/occipital region, radiates forward |
| Associated Symptoms | Nausea, vomiting, light/sound sensitivity | Scalp tenderness, muscle tightness | Reduced neck range of motion, shoulder pain |
| Triggers | Bright lights, loud sounds, physical exertion | Stress, poor posture, fatigue | Sudden neck movements, prolonged sitting |
Migraine-Like Post-Trauma Headache
Almost half of all patients with post-traumatic head pain experience a migraine-like phenotype. These headaches are characterized by throbbing, moderate-to-severe pain that often worsens with routine physical activity.
They bring along exhausting sensory sensitivities, such as photophobia (sensitivity to light) and phonophobia (sensitivity to sound), sometimes accompanied by nausea or vomiting. Research published in the Posttraumatic Headache – StatPearls review shows that patients with a past personal or family history of migraines are 45% more likely to develop this highly disabling phenotype after a TBI. You can learn more about managing these severe symptoms in our breakdown of Headaches After Car Crash.
Tension-Type and Cervicogenic Post-Trauma Headache
Tension-type headaches are incredibly common after a crash, affecting 20% to 40% of patients. They feel like a tight, vice-like band squeezing both sides of the head.
Cervicogenic headaches, on the other hand, are rooted in structural neck injuries like whiplash. Because of a neurological phenomenon called “trigeminocervical convergence,” pain signals from damaged muscles, ligaments, or facet joints in your upper neck travel along the same pathways as sensory nerves in your head. Your brain gets confused and registers the neck damage as a headache. If you’ve been in a minor collision and are feeling this radiating pain, our guide to Fender Bender Headaches explains how neck strain translates directly into head pain.
Pathophysiology and Risk Factors for Persistent Symptoms
Why does a physical blow to the body cause months of head pain? The underlying science involves several overlapping physiological disruptions:
- Autonomic Dysfunction: The autonomic nervous system controls involuntary functions like heart rate and blood vessel constriction. After an injury, this system can lose its balance, leading to a feeling of intense pressure—as if your head is “blowing up like a balloon.”
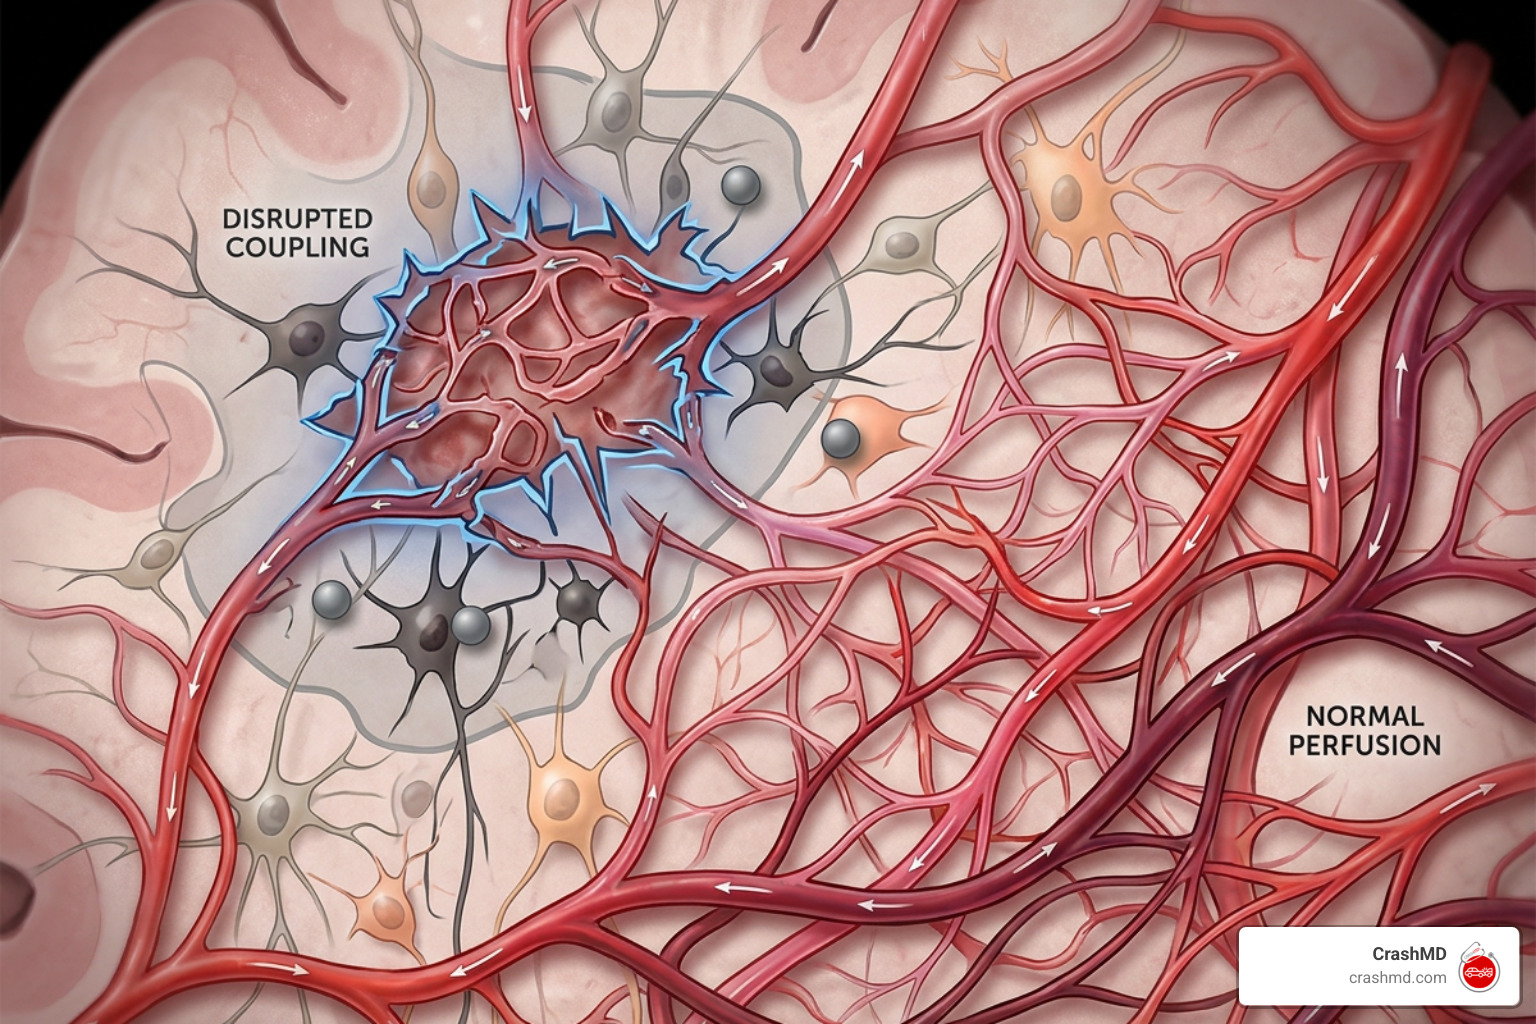
- Neurovascular Coupling Dysfunction: Normally, your brain coordinates local blood flow to match metabolic demand. When you think or focus, blood rushes to those active brain areas. Post-injury, this coupling breaks down. When you try to perform cognitive tasks, the blood flow doesn’t coordinate properly, triggering a headache.
- Trigeminal Activation & Neuroinflammation: The trauma triggers a cascade of inflammatory chemicals that irritate the trigeminal nerve, the primary sensory pathway for the face and head.
- Glymphatic Dysfunction: The glymphatic system is the brain’s waste-clearance pathway, operating primarily while we sleep. Trauma can disrupt this system, allowing cellular waste to build up and contribute to chronic pain.
While anyone can develop a persistent post-trauma headache, certain risk factors make it much more likely:
- Female Sex: Women are twice as likely as men to develop persistent symptoms (a 2 to 1 ratio).
- Prior Headache History: A pre-existing history of migraines or tension headaches significantly increases vulnerability.
- Psychiatric Comorbidity: Co-existing anxiety, depression, or PTSD—especially common in military veterans and car accident survivors—strongly correlates with persistent pain.
- Injury Severity: Interestingly, post-trauma headaches are actually more frequent in patients recovering from mild TBIs (concussions) than those who sustain moderate-to-severe brain injuries.
To explore how these biological changes can cause delayed pain, read our resource on Delayed Symptoms After Car Accident. You can also dive deeper into the neurological mechanisms by reading about the Pathophysiology of Posttraumatic Headache.
Evidence-Based Treatment and Management Strategies
Because there is no single FDA-approved drug specifically created for post-traumatic headaches, we use a comprehensive, phenotype-guided approach to find relief.

Pharmacologic Management
Medication should always be tailored to the specific headache phenotype:
- Acute Relief: For episodic, tension-type headaches, simple NSAIDs (like ibuprofen or naproxen) are first-line. For migraine-like headaches, triptans or newer CGRP inhibitors are used.
- Preventive Care: If headaches occur frequently, off-label preventives like tricyclic antidepressants (amitriptyline) or beta-blockers may be introduced to calm the nervous system.
Non-Pharmacologic and Interventional Therapies
Relying solely on medication is rarely enough. A comprehensive recovery plan includes:
- Physical Therapy: Vital for cervicogenic headaches. Targeted cervical spine physical therapy, manual manipulation, and posture training address the root physical triggers in the neck.
- Behavioral Therapy: Cognitive Behavioral Therapy (CBT) and biofeedback help regulate autonomic nervous system hyperarousal, reducing stress-induced headache triggers.
- Interventional Blocks: Sphenopalatine ganglion (SPG) blocks—including innovative home-use lidocaine nasal sprays—can rapidly halt severe migraine-like episodes. Occipital nerve blocks are highly effective for relieving localized, radiating neck-to-head pain.
- Surgical Options: For rare, severe cases where a specific nerve is physically compressed by surrounding scar tissue, nerve decompression surgery may be considered.
To build a complete picture of your recovery options, you can read the clinical review Posttraumatic Headache: A Comprehensive Approach or check out our dedicated patient guide to Post-Traumatic Headache.
Frequently Asked Questions about Post-Traumatic Headaches
How long do post-traumatic headaches typically last?
For many patients, a post-trauma headache is acute, resolving within the first 3 months. However, approximately 18% to 22% of patients experience persistent headaches that last beyond 1 year. In patients recovering from mild traumatic brain injuries, studies show that roughly 22.6% still suffer from persistent headaches at the 6-month mark. This ongoing pain has a massive real-world impact—up to 35% of persistent headache patients are unable to return to work after 3 months.
When should I seek emergency care for a headache after an accident?
While most post-trauma headaches are not life-threatening, certain “red flag” symptoms require immediate emergency evaluation to rule out brain bleeds, structural neck fractures, or severe neurological injuries. Seek emergency care immediately if you experience:
- A sudden, explosive headache (often called a “thunderclap” headache)
- Repeated vomiting or severe, worsening nausea
- Slurred speech, confusion, or severe drowsiness
- Numbness, weakness, or tingling on one side of your face or body
- Vision changes or difficulty walking
To help you monitor your recovery safely, we have compiled a list of critical warning signs in our guide to Headache After Car Accident Red Flags.
Can medication overuse make post-traumatic headaches worse?
Yes, absolutely. This is a common trap called Medication-Overuse Headache (MOH), or “rebound headaches.” If you take acute pain relief medications—such as NSAIDs, triptans, combination pain relievers, or prescription opioids—more than 10 to 15 days per month for over 3 months, your brain can become sensitized. The medicine that once brought relief begins to cause daily, dull headaches as it wears off. Managing chronic headaches requires careful coordination to taper off overused medications while introducing effective daily preventive strategies.
Conclusion
Recovering from a post-trauma headache requires more than just waiting for the pain to go away. Because these headaches involve a complex mix of neck strain, neurological inflammation, and nervous system dysfunction, the most successful recoveries rely on a coordinated, interprofessional team of physicians, physical therapists, and specialists.
At CrashMD, we specialize in helping accident victims navigate this challenging journey across Arizona, Nevada, Texas, Oklahoma, and California. We don’t just advocate for your physical recovery by connecting you to tailored medical care; we also ensure your injuries are meticulously documented for your legal case. This comprehensive approach protects both your health and your legal rights, allowing you to focus entirely on healing.
If you or a loved one is dealing with persistent head pain after a crash, don’t wait for the symptoms to worsen. Explore our resource on The Aches and Pains After Your Accident What to Know About Headaches and More to take your first step toward a pain-free recovery.