

Understanding How Does a Pancreas Injury Affect the Body
To understand how does a pancreas injury affect the body, we first have to look at how this delicate organ normally operates. Tucked in the retroperitoneal space behind the stomach, the pancreas fulfills two vital roles: exocrine (producing powerful digestive enzymes like lipase, amylase, and trypsin) and endocrine (producing hormones like insulin and glucagon to regulate blood sugar).
When direct physical impact damages pancreatic tissue, it disrupts both systems simultaneously. The most dangerous immediate consequence of a blunt or penetrating force is premature enzyme activation. Normally, digestive enzymes travel through the main pancreatic duct in an inactive state, only waking up once they hit the small intestine. But when trauma crushes or lacerates the pancreas, these enzymes activate right inside the organ.
This triggers a cascade of self-digestion, where the body’s own juices erode pancreatic tissue and surrounding blood vessels. Over time, loss of exocrine function causes exocrine pancreatic insufficiency (EPI), while damage to the endocrine islet cells can lead to secondary diabetes mellitus. Left unchecked, this local cascade sparks systemic inflammatory response syndrome (SIRS), causing widespread vascular leakage and swelling throughout the entire body. You can learn more about assessing abdominal trauma by checking out our Pancreas Injury Survival Guide: Severity, Symptoms.
Digestion and Hormone Disruption: How Does a Pancreas Injury Affect the Body?
When looking at how does a pancreas injury affect the body from a metabolic perspective, digestion and hormone production take an immediate hit. The gland produces about 1.5 liters of enzyme-rich fluid daily. When trypsin activates prematurely within acinar cells, it starts breaking down the gland itself, destroying cells that release lipase (which breaks down fats) and amylase (which processes carbohydrates).
Without these functional enzymes reaching the digestive tract, your body loses its ability to absorb essential nutrients. Fat-soluble vitamins (A, D, E, and K) pass through unabsorbed, leading to severe malabsorption, rapid weight loss, and chronic malnourishment. Simultaneously, physical damage to the islet of Langerhans cells in the tail and body of the pancreas shuts down insulin production and distorts glucagon regulation. This sudden loss of blood sugar control can trigger acute hyperglycemia, requiring immediate medical management.
Systemic Complications and Organ Failure
The destruction doesn’t stop in the abdomen. As activated digestive juices destroy local blood vessels and tissue, inflammatory cytokines escape into the bloodstream. This systemic release of enzymes and cytokines drives systemic inflammatory response syndrome (SIRS), which affects distant, healthy organs:
- Lungs: Activated phospholipase A2 leaks into circulation and specifically breaks down alveolar surfactant in the lungs. This causes alveolar membrane damage, fluid accumulation, low blood oxygen, and acute respiratory distress syndrome (ARDS).
- Kidneys: Severe chemical inflammation and systemic capillary leaks cause massive drops in blood volume and pressure, depriving the kidneys of blood flow and triggering acute kidney injury.
- Cardiovascular System: Widespread vascular relaxation and fluid shifts lead to septic shock or hypovolemic shock, requiring intensive resuscitation.
Following established medical protocols, such as those outlined in the Diagnosis and management of pancreatic trauma guidelines, is crucial for preventing multi-organ failure.
Pancreatic Injury Severity, Ductal Integrity, and Diagnostics
The outcome of a pancreatic injury depends heavily on two critical factors: its severity grade and whether the main pancreatic duct remains intact. The American Association for the Surgery of Trauma (AAST) categorizes pancreatic trauma into five distinct grades:
- Grade I: Minor contusion or superficial laceration without duct injury.
- Grade II: Major contusion or laceration without duct injury or tissue loss.
- Grade III: Distal transection or parenchymal injury with main pancreatic duct disruption.
- Grade IV: Proximal transection (to the right of the superior mesenteric vein) involving the pancreatic head.
- Grade V: Massive disruption of the pancreatic head and duodenal complex.
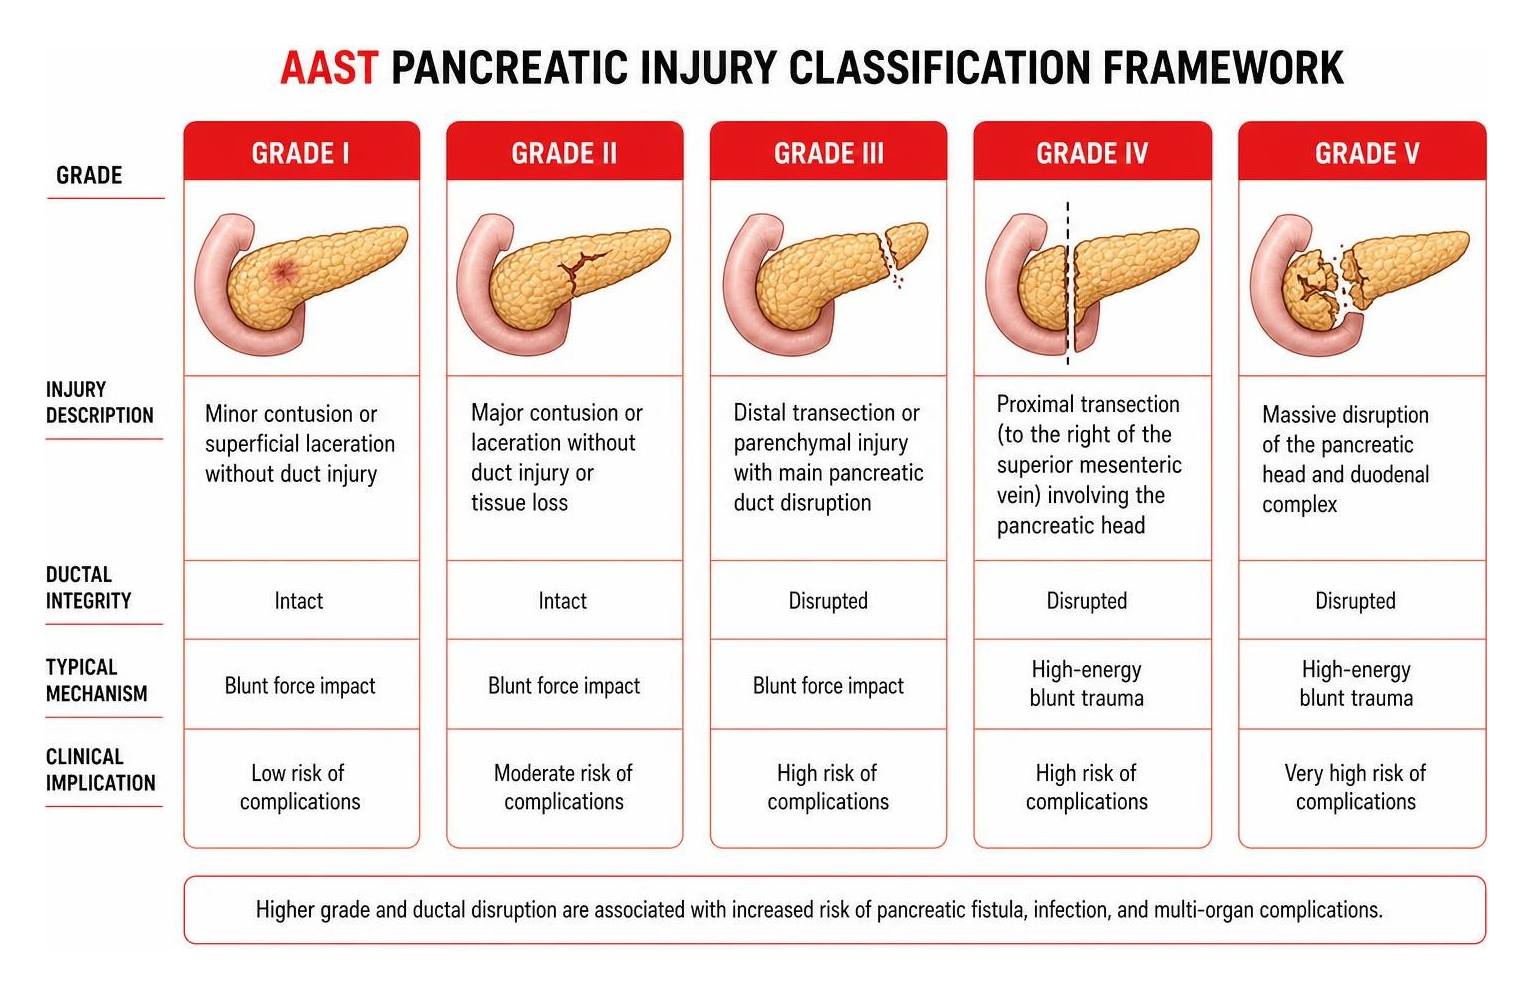
Because the pancreas lies deep in the retroperitoneal space, surrounded by the stomach, duodenum, and spine, early physical exams can be deceivingly normal.
Pancreatic Pancreatic Duct Disruption and Diagnostic Tools
Identifying main pancreatic duct disruption is the single most crucial step in managing pancreatic trauma. If the duct is torn or completely transected, high-pressure pancreatic fluids leak freely into the retroperitoneum, leading to rapid tissue erosion and deep abdominal infection.
To catch these injuries early, physicians rely on specialized diagnostic tools:
- Contrast-Enhanced CT Scans: While standard abdominal CT is the initial imaging modality of choice, it can miss up to 20% to 40% of ductal injuries within the first 12 hours.
- Secretin-Stimulated MRCP: Magnetic resonance cholangiopancreatography enhanced with secretin stimulates fluid flow, highlighting subtle tears in the main pancreatic duct.
- Endoscopic Retrograde Cholangiopancreatography (ERCP): Considered the gold standard for direct duct visualization, ERCP allows specialists to place protective stents across injured duct sections.
- Intraoperative Ultrasound (IOUS): During surgery, a high-frequency ultrasound probe placed directly on the organ provides near-perfect sensitivity for identifying main duct transections.
For further clinical context on timing surgical interventions, review the Indications for surgical management of pancreatic trauma.
Diagnostic Pitfalls and Delayed Recognition
Diagnosing pancreatic trauma is notoriously challenging. Thanks to its deep retroperitoneal positioning, the organ is cushioned from direct contact with the anterior abdominal wall. Consequently, initial physical exams after an accident may show little to no tenderness. Furthermore, diagnostic blood tests like serum amylase and lipase remain completely normal in up to 35% of patients with total pancreatic transection during the first few hours.
To avoid dangerous diagnostic delays, trauma specialists calculate scoring metrics like the Pancreatic Injury Mortality Score (PIMS), which factors in patient age, shock status, vascular damage, and associated injuries. If you’ve recently been in a crash, scheduling Your First Check-Up: What Happens After a Car Accident ensures hidden injuries don’t slip through the cracks.
Traumatic Pancreas Injury vs. Acute Pancreatitis
It is easy to confuse a traumatic pancreas injury with acute pancreatitis, as both involve painful inflammation and premature enzyme activation. However, their root causes and biological behaviors differ significantly.
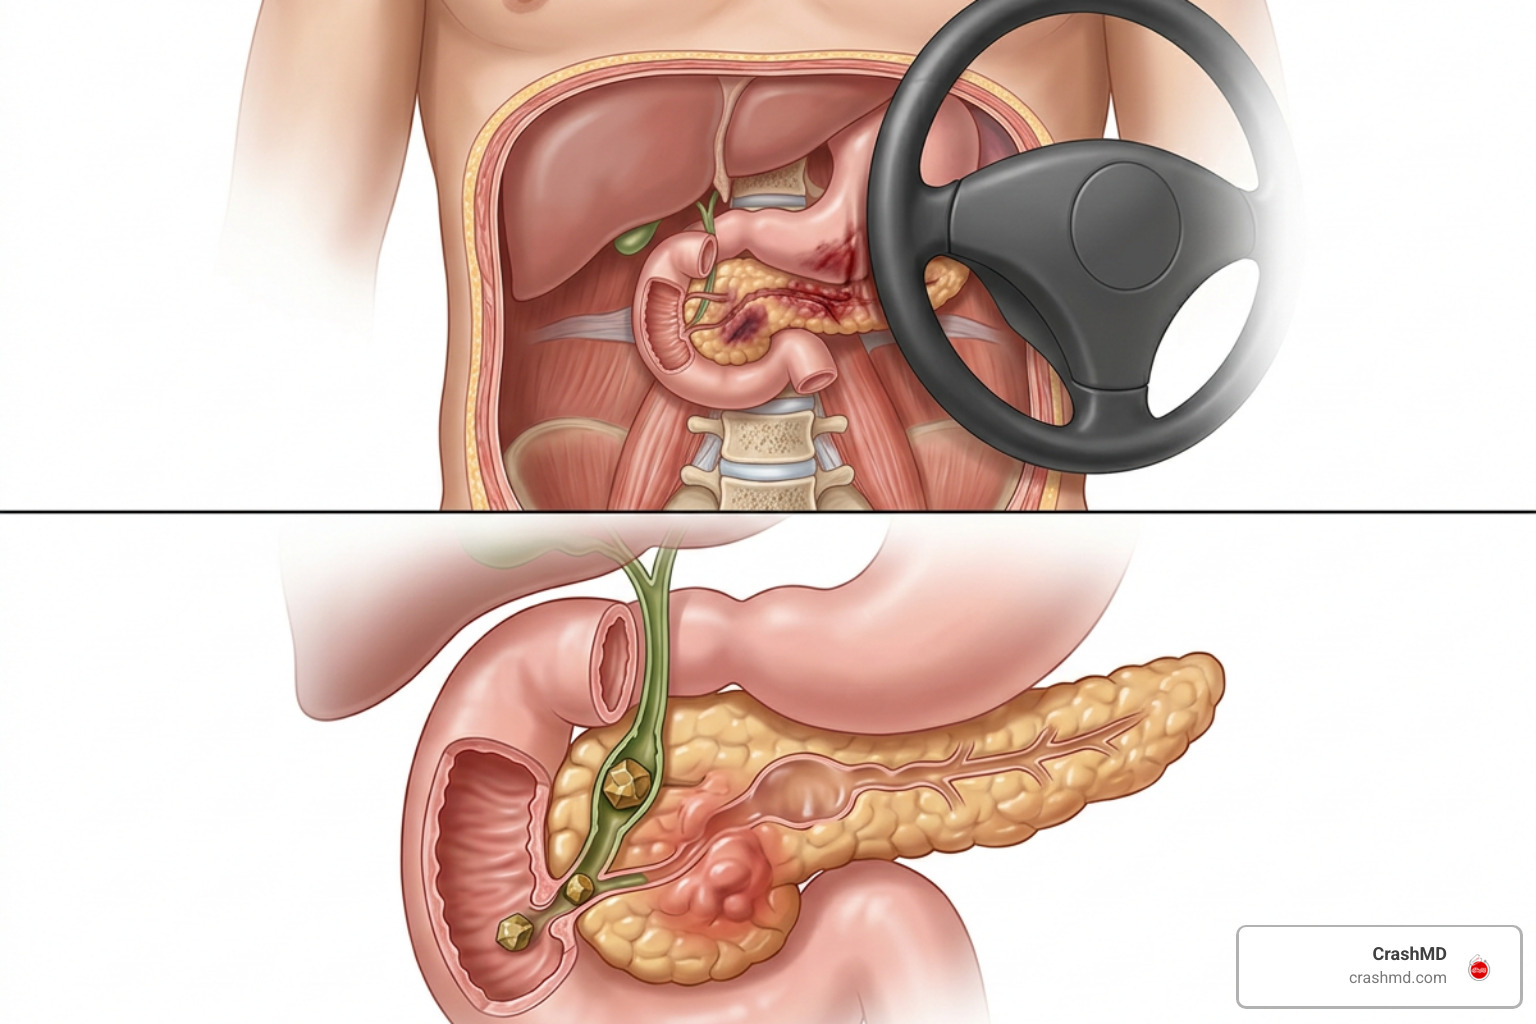
Traumatic injuries stem from external kinetic force—such as direct steering wheel impact, seatbelt compression, or bicycle handlebar collisions—which physically lacerates or crushes the tissue against the spine. Acute pancreatitis, on the other hand, is usually an internal medical condition triggered by gallstones blocking the biliary duct or heavy alcohol use. You can explore medical details via the Pancreatitis symptoms and causes guide.
Pediatric vs. Adult Vulnerability: How Does a Pancreas Injury Affect the Body?
When evaluating how does a pancreas injury affect the body across different age groups, age plays a key role in injury mechanics. Children are far more susceptible to traumatic pancreatic damage than adults:
- Thinner Abdominal Walls: Pediatric patients have less abdominal fat and thinner, less developed abdominal muscles, offering minimal natural cushioning against blunt force.
- Proximity to the Spine: In children, the pancreas sits closer to the anterior abdominal surface, making it easily compressed against the L1-L2 vertebral column during bicycle handlebar accidents or vehicle crashes.
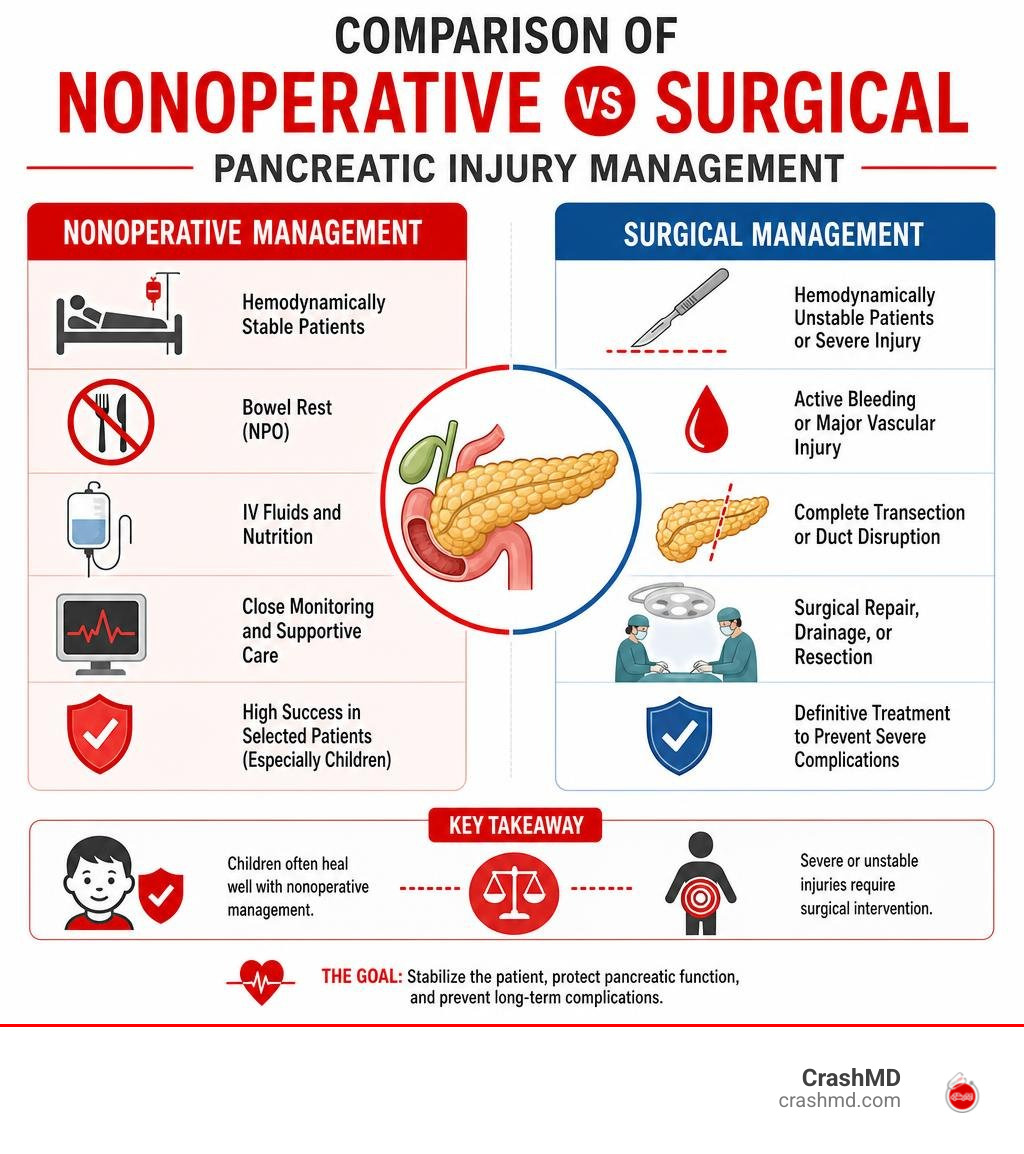
- Conservative Management Success: Despite high vulnerability, pediatric pancreatic injuries often heal remarkably well with nonoperative management, bowel rest, and IV nutrition, as detailed in the UCSF Benioff Children’s Hospital pancreatic injury guide.
Differences in Pathology and Acute Care
Isolated pancreatic injuries are rare; over 90% of traumatic cases involve damage to adjacent abdominal organs, with combined duodenal-pancreatic injuries being the most frequent. Blunt force typically causes clean transections where the organ crosses the spine, whereas penetrating wounds (gunshot or stab injuries) cause extensive tissue tearing and major vascular hemorrhages.
Penetrating injuries carry double the complication rate of blunt trauma (39% vs. 20%) and often require immediate surgical resection rather than simple drainage. Understanding these acute care pathways is essential when selecting emergency treatment, as outlined in our guide on Immediate Care After an Accident: Your Guide to Urgent Care and ER Options.
Long-Term Consequences, Risk Factors, and Medical Treatment
Surviving the acute phase of a pancreatic injury is only half the battle. Delayed complications from unaddressed duct leaks or extensive tissue damage can arise weeks or months later:
- Pancreatic Pseudocysts: Fluid collections rich in pancreatic enzymes accumulate outside the duct, causing chronic abdominal pain, infection, or rupture.
- Walled-Off Necrosis: Patches of dead pancreatic tissue turn into infection-prone pockets that may require endoscopic or surgical clearing.
- Pancreatic Fistulas: Abnormal sinus tracts form between the damaged duct and the skin or adjacent abdominal organs, leaking digestive fluid.
- Chronic Pain and EPI: Ongoing tissue scarring damages nerve pathways and destroys enzyme-producing acinar cells, causing persistent pain and chronic malnutrition.
- Pancreatic Cancer Risk: Prolonged tissue destruction and inflammation elevate the long-term risk of developing pancreatic adenocarcinoma by 1% to 2%.
Exacerbating Factors and Lifestyle Triggers
Pre-existing conditions and lifestyle choices can exacerbate pancreatic recovery. Consuming alcohol or smoking cigarettes while recovering from a pancreatic injury creates a dangerous synergistic effect:
Heavy alcohol intake accelerates pancreatic acinar cell death, while cigarette smoking triples the risk of developing recurrent pancreatitis. Similarly, underlying gallstones or high triglyceride levels (hypertriglyceridemia) add extra stress to an already compromised organ. For a complete clinical review of metabolic triggers, refer to Acute Pancreatitis in Merck Manuals.
Treatment Approaches and Digestive Rehabilitation
Addressing long-term pancreatic damage requires a combination of surgical and medical interventions:
- Pancreatic Enzyme Replacement Therapy (PERT): Prescription enzyme pills taken with every meal supply essential lipase, amylase, and protease, restoring nutrient absorption.
- Distal Pancreatectomy: Surgical removal of the tail and body of the pancreas, usually performed for Grade III main duct injuries.
- Pancreaticoduodenectomy (Whipple Procedure): A complex surgical procedure reserved for severe Grade V injuries involving extensive destruction of the pancreatic head and duodenum.
- Islet Auto-Transplantation: In severe cases where the entire organ must be removed, surgeons extract insulin-producing islet cells and inject them into the liver, where they continue releasing insulin into the bloodstream.
Navigating this recovery journey requires structured medical oversight, as described in our detailed guide on Post-Accident Protocol: Navigating Your Medical Journey.
Frequently Asked Questions About Pancreatic Injury
Can a pancreas injury heal without surgery?
Yes. Mild pancreatic injuries classified as AAST Grade I or II (superficial bruises or minor cuts without duct damage) are routinely managed nonoperatively. Treatment involves temporary bowel rest (fasting), IV fluid hydration, pain management, and close inpatient monitoring to ensure no delayed complications arise.
How quickly do symptoms appear after a traumatic pancreas injury?
Symptom onset is often delayed. Because the pancreas sits behind the peritoneal cavity, initial physical signs may be mild. Patients often experience gradually worsening upper abdominal pain, persistent nausea, vomiting, and back pain that intensifies 12 to 48 hours after the initial accident.
What are the main signs that a pancreatic injury has affected blood sugar?
When trauma damages the insulin-producing beta cells in the islet tissue, patients may develop secondary diabetes mellitus. Key warning signs include persistent high blood sugar (hyperglycemia), excessive thirst (polydipsia), frequent urination (polyuria), unexplained fatigue, and sudden weight loss.
Comprehensive Trauma Care and Legal Documentation
At CrashMD, we guide accident victims through every stage of their recovery across our care locations in Arizona, Nevada, Texas, Oklahoma, Southern California, and Northern California.
I’m Dr. Adam Savage, and our specialized medical team understands the unique challenges of retroperitoneal organ injuries. A traumatic pancreas injury can be subtle at first, yet lead to catastrophic long-term digestive and metabolic complications if missed during initial emergency room evaluations.
Our practice focuses on advocating for patients, offering expert pain management, and building tailored treatment plans for post-accident medical care. Crucially, we meticulously document every physical injury, diagnostic scan, and long-term care need to ensure your medical history is fully supported before you take legal action.
If you or a loved one are experiencing abdominal pain or digestive troubles following a car accident, don’t wait for complications to escalate. Explore our complete Car Accident Pancreas Injury Recovery Guide or reach out to our team today to ensure your health and recovery are fully protected.