

When a Treatment Causes the Pain: Understanding Headache from Nerve Block Crash
A headache from nerve block crash is one of the most frustrating experiences a car accident survivor can face — you finally get a procedure meant to help your pain, and then your head starts pounding harder than before.
Quick answer: What is a nerve block crash headache?
- A nerve block temporarily numbs pain signals using local anesthetic (and sometimes a steroid)
- When the anesthetic wears off, pain can return — sometimes worse than before
- This flare-up is called a “nerve block crash” or post-block pain rebound
- It can feel like a throbbing migraine, burning occipital pain, or a tight cervicogenic headache
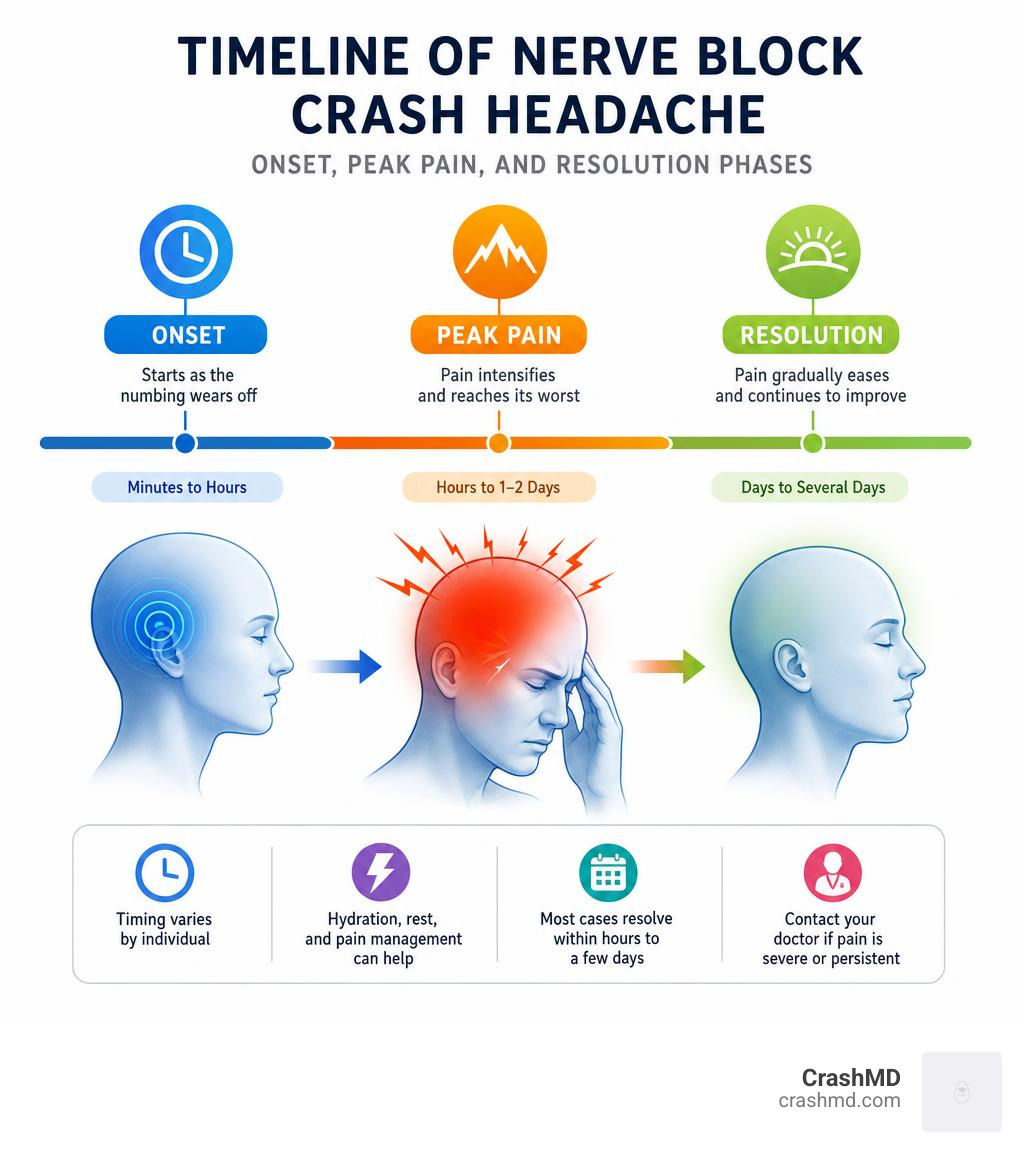
- Most cases resolve within hours to a few days, but some persist longer
- Certain patients — especially those with prior migraines, whiplash, or concussion — are at higher risk
This is not a rare or imagined experience. It is a recognized phenomenon in pain medicine, and it can be especially disorienting if you are already navigating recovery from a car accident.
If you have recently had an occipital nerve block, trigeminal nerve block, or another head and neck injection, and you are now dealing with a new or worsened headache, you are not alone — and there are clear reasons why this happens.
This guide breaks down exactly what causes these post-procedure pain flare-ups, how to tell a normal crash from a serious complication, and what to do next.
What is a Headache from Nerve Block Crash?

“I’m Dr. Adam Savage,” and I frequently see patients in our clinics across Arizona, Texas, and California who are utterly blindsided by a sudden spike in pain after a procedure. When you undergo a peripheral nerve block (such as an occipital or trigeminal nerve block), the goal is simple: interrupt the pain signals traveling from irritated nerves to your brain.
However, as the local anesthetic wears off, a phenomenon known as “rebound pain” or a “nerve block crash” can occur. This is a temporary, acute increase in pain intensity that surpasses your baseline pain level before the injection.
But why does this happen? The primary culprit is local anesthetic wear-off. When the numbing agent (like lidocaine or bupivacaine) metabolizes and leaves the nerve receptors, the sudden return of sensory input can shock your nervous system. This sudden transition can cause hyperalgesia—a state where your nervous system becomes temporarily hypersensitive, making normal nerve signals feel incredibly painful.
For many car accident victims already dealing with sensitized nervous systems, this crash can trigger a severe, localized headache. If you are trying to understand how this ties into your overall accident recovery, you can read More info about post-accident headaches and explore the physiological mechanics of post-block flares at Why Is My Pain Worse After A Nerve Block?.
Why Does a Nerve Block Trigger or Worsen a Headache?

To understand why a headache from nerve block crash happens, we have to look closely at how our nerves react to being poked, prodded, and chemically silenced.
When a nerve is blocked, the sudden lack of electrical activity triggers a cellular response. The nerve cells attempt to compensate by increasing the sensitivity and number of their pain receptors—a process called receptor upregulation. Once the anesthetic fades, these upregulated receptors are exposed to normal bodily stimuli, resulting in nociceptive sensitization. The nerve essentially overreacts to its environment, firing rapid pain signals to the brain.
Additionally, the physical act of performing the injection causes localized trauma. The needle must pass through skin, fascia, and muscle layers, which can cause:
- Local inflammation: The tissue reacts to the physical needle tract and the foreign substances injected.
- Tissue distension: Injecting a volume of fluid into a tight, enclosed anatomical space stretches the surrounding tissue, irritating nearby nerve fibers.
These localized tissue changes and anatomical complications are well-documented in clinical literature, such as the Complications of Occipital Nerve Block – Anesthesia Key, which details how tissue trauma and localized pressure can trigger secondary pain cascades.
Pharmacological Triggers of Headache from Nerve Block Crash
The specific medications used in your block play a massive role in how your body reacts post-procedure. Most nerve blocks contain a mixture of a local anesthetic and a corticosteroid:
- Local Anesthetics (Lidocaine & Bupivacaine): Lidocaine provides rapid, short-acting relief, while bupivacaine is long-acting. However, bupivacaine has been shown to exhibit localized myotoxicity (muscle toxicity) when combined with certain steroids, causing temporary muscle irritation and spasm in the neck or scalp, which directly triggers tension-style headaches.
- Corticosteroids (Triamcinolone, Methylprednisolone, Dexamethasone): Steroids are added to reduce long-term inflammation, but they can cause a “steroid flare” in the first 24 to 72 hours before their anti-inflammatory properties kick in.
Furthermore, serial or high-dose corticosteroid blocks can have systemic side effects. Research has linked repeated cranial nerve blocks using triamcinolone to systemic issues like adrenal suppression. You can read more about this risk in Adrenal suppression associated with greater occipital nerve and multiple cranial nerve blocks using triamcinolone. In rare, extreme cases, excessive steroid exposure from repeated blocks can even lead to iatrogenic Cushing syndrome, as outlined in Cushing Syndrome Induced by Serial Occipital Nerve Blocks Containing Corticosteroids.
Risk Factors for Developing a Headache from Nerve Block Crash
Not everyone who gets a nerve block will experience a crash. However, certain pre-existing conditions and trauma histories make your nervous system far more vulnerable:
- Migraine History: Patients with a history of chronic migraines have highly sensitive brains. A nerve block can easily trigger a full-blown migraine attack as the anesthetic wears off.
- Medication Overuse: If you are frequently taking pain relievers, your brain’s pain-processing pathways are already unstable, increasing the risk of a rebound headache.
- Whiplash Trauma: Whiplash damages the delicate joints and ligaments of the neck. In fact, nearly 80 percent of people who experience whiplash develop a chronic, neck-related (cervicogenic) headache, and nearly 4 out of 10 still suffer a year after the accident. You can learn more about managing these injuries by reading about Understanding whiplash-related headaches.
- Concussion: Post-traumatic headaches develop in 91% of patients who have a concussion. This traumatic brain injury leaves the central nervous system in a state of high alert, making a post-block crash highly likely. Read more about these connections in Concussion and post-traumatic headaches.
Types of Post-Block Headaches and Diagnostic Red Flags
When a headache strikes after a nerve block, it is vital to identify what type of headache it is and rule out any serious procedural complications.
Common Post-Block Headache Types
- Rebound Headache: A generalized, throbbing ache that peaks within 24 to 48 hours as the local anesthetic completely clears your system.
- Migraine-like Headache: Characterized by throbbing on one side of the head, nausea, and sensitivity to light or sound.
- Occipital Neuralgia: A sharp, shooting, or electric shock-like pain radiating from the base of the skull up to the scalp, often triggered by direct needle irritation of the greater or lesser occipital nerves.
- Cervicogenic Headache: A dull, aching pain originating from the neck and radiating to the forehead or temple, often caused by muscle spasms or facet joint irritation from the injection.
| Headache Type | Primary Symptoms | Typical Onset |
|---|---|---|
| Rebound Headache | Dull, generalized throbbing; mild to moderate intensity | 12 to 24 hours post-block |
| Occipital Neuralgia | Shooting, electric-shock, burning pain from skull base to scalp | Immediate to 48 hours |
| Cervicogenic Headache | Dull ache originating in the neck, limited range of motion | 24 to 72 hours |
For patients with severe, chronic occipital neuralgia that fails to respond to conservative care or blocks, advanced surgical options might be considered. You can explore the outcomes of these procedures in Tracking patients with chronic occipital headache after occipital nerve decompression surgery. If your neck pain started after a minor collision, read about Fender bender headaches and cervicogenic pain.
Serious Complications & Red Flags
While a headache from nerve block crash is usually harmless, clinicians must watch for rare but serious complications:
- Hematoma or Vascular Injury: Accidental puncture of the occipital or vertebral arteries can cause localized bleeding, airway obstruction, or even a posterior circulation stroke.
- Infection: Although rare (infection requiring intervention after an indwelling catheter is reported up to 0.8%), localized abscesses or meningitis are medical emergencies.
- Local Anesthetic Systemic Toxicity (LAST): Clinically significant LAST occurs between 7.5 and 20 times per 10,000 regional anesthetics. Symptoms include a metallic taste, ringing in the ears, perioral numbness, seizures, or cardiovascular collapse.
- Dural Puncture & CSF Leak: If a needle goes too deep during a high neck injection, it can puncture the dura, causing a postdural puncture headache (PDPH) that worsens when standing.
You can read a detailed clinical breakdown of these procedural risks in Complications Associated with Head and Neck Blocks – Anesthesia Key. For those dealing with spinal-fluid-related headaches, peripheral nerve blocks are actually being utilized as an innovative treatment, as discussed in Peripheral Nerve Blocks for Postdural Puncture Headache.
Prevention and Management Strategies for Post-Block Pain
At CrashMD, we believe the best way to manage a post-block crash is to prevent it from happening in the first place. Modern pain management techniques have significantly reduced the incidence of these flare-ups:
- Ultrasound and Imaging Guidance: Using ultrasound or fluoroscopy ensures precise needle placement, minimizing direct trauma to the nerve and surrounding tissues.
- Optimizing Injectate Volume: Using the smallest effective volume of local anesthetic prevents excessive tissue distension and pressure-related nerve irritation.
- Patient Preparation: Educating patients on what to expect, staying hydrated, and avoiding strenuous activity immediately after the procedure.
Acute and Preventive Management
If a crash does occur, we recommend a multi-faceted approach to get you through the flare-up:
- Cold and Heat Therapy: Apply ice packs to the injection site for 15-minute intervals to reduce acute inflammation, followed by moist heat to relax tense neck muscles.
- Medication Management: Short-term use of anti-inflammatories (NSAIDs) or muscle relaxants can help calm the rebound pain.
- Gentle Physical Therapy: Soft tissue mobilization and gentle stretching can prevent the muscle guarding that often worsens cervicogenic headaches.
If you are dealing with concurrent symptoms like balance issues or severe post-crash head pain, explore our guide on Managing post-accident dizziness and headaches or learn how to take control of your recovery in Don’t let a car crash headache drive you crazy.
Frequently Asked Questions About Post-Block Headaches
What is the typical timeline for a headache from nerve block crash?
A post-block crash typically begins within 12 to 24 hours after the procedure, directly coinciding with the half-life and wear-off of the local anesthetic. The peak pain usually lasts between 24 to 48 hours. Most patients see a complete resolution of the flare-up and begin experiencing the therapeutic benefits of the block within 3 to 5 days.
How can I tell if my headache is a normal nerve block crash or a serious complication?
A normal nerve block crash presents as a dull, aching, or throbbing pain that gradually improves over a few days.
Red flags that require immediate medical attention include:
- A fever or chills (signs of infection)
- Rapidly worsening swelling, redness, or warmth at the injection site
- Sudden neurological deficits, such as double vision, difficulty speaking, or numbness in your face or arm
- A “thunderclap” headache that reaches maximum intensity within seconds
- A headache that completely disappears when lying flat but becomes excruciating when standing up (indicative of a CSF leak)
When should I seek specialist care for a headache from nerve block crash?
If your post-block headache persists beyond 5 to 7 days without improvement, or if the pain is completely refractory to basic rescue medications, it is time to seek specialist care. A multidisciplinary pain specialist can re-evaluate your diagnosis, adjust your treatment plan, or explore alternative interventional pain management options.
Conclusion
Experiencing a headache from nerve block crash can feel like a major setback on your road to recovery, but understanding why it happens is the first step toward overcoming it.
At CrashMD, we specialize in helping car accident survivors navigate these complex recovery hurdles. We don’t just treat your symptoms—we provide comprehensive patient advocacy. Our team ensures your injuries are thoroughly documented for legal and insurance purposes, protecting your rights while you focus on healing. From coordinating expert medical care to providing robust medical-legal support, we are with you every step of the way.
Don’t let a temporary setback derail your recovery. Schedule an appointment with CrashMD today or Visit CrashMD homepage to learn more about how we can support your journey back to a pain-free life.